Lying dumbbell shoulder flexion
Lying dumbbell shoulder flexion strengthens the front of your shoulder (anterior deltoid) through the first half of lifting the arm forward. You lie on your back with a light weight in one hand at your side, lift the straight arm, thumb leading, until it points at the ceiling, pause, and lower it back down. The bed supports your back and neck, and the weight feels heaviest as it leaves your side and lightest once the arm is upright.
How to do the lying dumbbell shoulder flexion
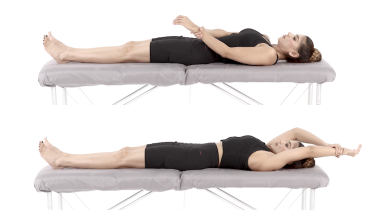
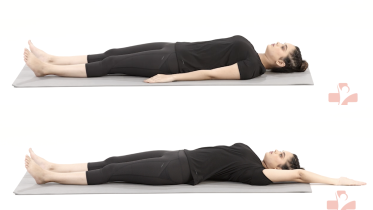
- Lie on your back on a firm bed or a mat on the floor, both arms resting beside you. The video shows straight legs; bend your knees if that feels easier on your lower back.
- Take a light dumbbell in your working hand, palm turned in toward your thigh so the thumb points up.
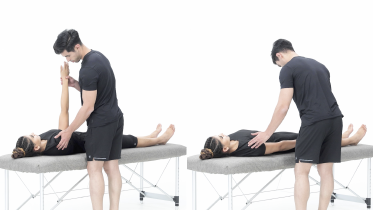
- Keep the elbow straight and lift the arm forward and up, thumb leading, until it points straight up at the ceiling.
- Hold it there for a moment, keeping your back and neck relaxed against the bed.
- Take the arm back down to your side slowly, then go again. Swap to the other arm afterward if your program asks for both.
What you should feel
Mostly the front of the shoulder, and most of all just after the weight leaves your side. Your neck and lower back stay loose throughout.
Common mistakes
- Arching the lower back off the bed as the arm lifts.
- Bending the elbow to shorten the lever.
- Lifting your head or tensing your neck.
- Letting the arm fall back down to the bed.
How often
Many programs use 2 to 3 sets of 10 to 15 slow repetitions with a light weight, 2 to 3 times a week. Your physio will adjust this.
Stop and check with your physio if
- A sharp pain or a catch in the shoulder on the way up, or pins and needles, numbness or pain running from the shoulder down toward the hand.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- A sudden pop or tearing feeling in the shoulder that brings sharp pain, new weakness or trouble lifting the arm. Stop and contact your surgical team the same day, or get medical advice the same day if you have not had surgery.
- The shoulder feels as if it has slipped out of place, looks a different shape or suddenly locks so you cannot move the arm, or your hand turns cold, pale or blue. Go to an emergency department straight away, without driving yourself, and do not try to put the shoulder back in yourself.
From the clinic
There is no need to go past upright. Once the arm points at the ceiling, the weight sits over the joint and the muscle has little left to do. If sharp or catching pain has ended a set, keep the lift under that point for now and raise it at your next physio visit. If you have high blood pressure, breathe steadily through every repetition and never hold your breath. If you are pregnant and past the first three months, check with your physio before exercising flat on your back.
At the top, the weight presses the ball of the shoulder joint backward. If your shoulder has ever slipped out backward, check with your physio before you start.
After shoulder surgery, including a rotator cuff repair, or after a shoulder fracture or dislocation, follow your surgeon's or physio's plan, and do only the movements and range they have cleared. Many plans allow only passive movement at first, where the arm is moved for you and its muscles stay relaxed. Holding a weight in the hand is normally one of the later stages of rehab after a cuff repair. If you cannot yet raise the arm from your side on its own, shoulder flexion with a stick lets your other hand help, and isometric shoulder flexion trains the same muscles while the arm stays still. The standing version is the dumbbell front raise.
Written and checked by the PocketPhysio editorial team. Last updated 2026-09-28.
This page is general education, not a diagnosis or a personal treatment plan. If you have pain, an injury or a health condition, see a physiotherapist or doctor before starting new exercises.