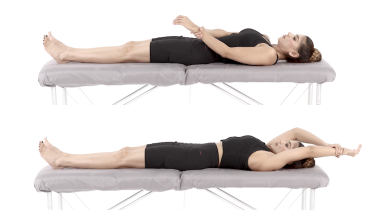
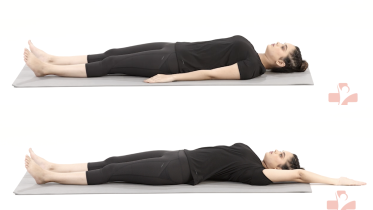
Lying shoulder flexion with a stick
Lie on your back, grip a stick in both hands and raise it over your chest and back toward the floor behind your head, with the easier arm doing most of the lifting (assisted range of motion). The stick holds your hands apart and square, which suits a shoulder too stiff or too sore to reach across and clasp the other hand. Lying flat makes it harder to arch your back or shrug to get higher, so this version often suits a very stiff shoulder that struggles in sitting or standing.
How to do the lying shoulder flexion with a stick
- Lie on your back on a mat or bed with your legs straight. Bending your knees is fine if your back feels better that way.
- Rest the stick across your thighs, palms down, hands roughly shoulder width apart.
- Keep both elbows straight and use the easier arm to lift the stick up over your chest.
- Carry on past the vertical, letting the stick travel back over your head toward the floor as far as is comfortable.
- Bring it back up and over, slowly, until it rests on your thighs again.
What you should feel
A stretch in the shoulder and along the side of the chest and upper back near the top of the movement, usually strongest on the stiffer side.
Common mistakes
- Letting the stiff arm do the lifting. The easier arm leads, and the stiff arm goes along with it.
- Arching the lower back off the mat as the stick goes overhead.
- Letting the stick drop quickly toward the floor behind your head.
How often
Many programs start with about 10 slow lifts, done 1 to 3 times a day, adding a few more as the movement eases. Reaching a little further counts for more than extra repetitions. Your physio will adjust this.
From the clinic
The stick is what makes this version possible. Clasped hands draw the stiff arm in across the body as they rise, while a stick keeps both hands roughly shoulder width apart, so the arm travels up the line it is meant to. The stiff arm still grips, so there is a little work in it, which makes this assisted rather than passive movement.
A stick that tips tells you one arm is pushing harder than the other. Keeping it level is the easiest check you have: let the easier arm lead and let the stiff one come along for the ride.
Once the stick passes the point straight above your chest, the weight of your arms starts to pull it down, so slow down there rather than letting it fall. A folded towel under your head can make the start more comfortable. Once this gets easy, most people move on to shoulder flexion with a stick in sitting or standing, and shoulder abduction with a stick works on lifting the arm out to the side.
Before you start
- After shoulder surgery, including a rotator cuff repair, or after a shoulder fracture or dislocation, follow your surgeon's or physio's plan, and do only the movements and range they have cleared. Many plans allow only passive movement at first, where the arm is moved for you and its muscles stay relaxed.
- After a repair of the biceps tendon at the elbow, or another repair, break or operation at the elbow or forearm, leave this one out until your surgeon or physio has cleared the elbow to straighten fully, and cleared you to hold it straight with the palm turned down and a stick in your hand. There is no smaller version of it. Both elbows stay straight and both palms turn down, and the easier arm supplies the push, so the repaired side is held straight and palm down by a stick it is also gripping. Lying down takes some of the weight out of the lift but none of that position out of it, and the stick carries on past the vertical toward the floor behind your head, which adds a stretch at the end. The biceps turns the palm up as well as bending the elbow, so a straight elbow with the palm turned down is the position that pulls hardest on a tendon repaired there, and the force holding the arm in it comes from your other arm through the stick. Early plans after this repair usually allow gentle bending and straightening, and turning the palm up and down with the elbow bent in at your side, and they keep those two movements apart from each other and from anything held in the hand, which is what this exercise puts together. If your team has set a limit on how far the elbow may straighten or how far the forearm may turn, or you are wearing a sling, brace, cast or splint after an operation or a break at the elbow or forearm, this exercise is not yet for you, and taking the arm out of it, or changing a brace setting, is not the way round that limit. Teams differ on when these movements can be put together, so the go-ahead comes from yours.
- After a repair, ask whether it is on your plan yet, and whether that arm should stay fully relaxed while the other one lifts.
- If you are pregnant and past the first three months, check with your physio before exercising flat on your back.
- A broom handle, a walking stick or a length of dowel all work as the stick.
When to stop and get help
- Sharp pain or a pinching catch as the stick goes overhead, or pain or pins and needles running down the arm.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- A sudden pop or tearing feeling in the shoulder that brings sharp pain, new weakness or trouble lifting the arm. Stop and contact your surgical team the same day, or get medical advice the same day if you have not had surgery.
- The shoulder feels as if it has slipped out of place, looks a different shape or suddenly locks so you cannot move the arm, or your hand turns cold, pale or blue. Go to an emergency department straight away, without driving yourself, and do not try to put the shoulder back in yourself.
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-30.
This page is general education, not a diagnosis or a personal treatment plan. If you have pain, an injury or a health condition, see a physiotherapist or doctor before starting new exercises.