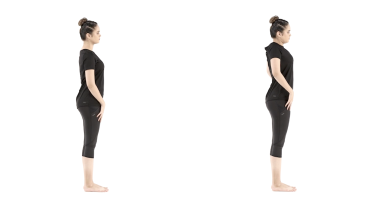
Standing shoulder rotation
Standing shoulder rotation turns the upper arm in its socket, with no weight or band. You stand tall with the elbow bent to a right angle and resting loosely at your side, then swing the forearm out to the side and back in across your stomach, like a door swinging on its hinge. The shoulder moves through its outward turn (external rotation) and its inward turn (internal rotation), and physios often use it early on to get a stiff or sore shoulder moving again.
How to do the standing shoulder rotation
- Stand up straight with your feet about hip width apart and your arms by your sides.
- Bend the elbow of the arm you are working to a right angle, so the forearm points straight ahead with the hand relaxed. Let the elbow rest lightly against your side.
- Set your shoulder blades gently back and down, without squeezing hard, and keep them there.
- Keeping the elbow at your side, swing the forearm slowly outward, away from your stomach, as far as is comfortable.
- Bring the forearm back past the start and in across the front of your stomach, then return to the middle. Control the movement both ways and repeat.
What you should feel
Light work deep in the shoulder and at the back of it as the arm turns out, and perhaps a mild stretch at the front of the shoulder at the end of the outward turn.
Common mistakes
- Letting the elbow drift forward or away from your side as the hand moves.
- Turning your whole body with the arm instead of turning at the shoulder.
- Lifting the shoulder toward your ear as the arm turns.
- Swinging fast so the forearm flings out and back.
How often
Many programs use 1 to 3 sets of 10 to 15 slow turns each way, once or twice a day. Your physio will adjust this.
Stop and check with your physio if
- A sharp pain or catching at the front or top of the shoulder as the arm turns, or a feeling that the shoulder could slip out.
- Pain, pins and needles or numbness spreading down your arm or into your hand.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- A sudden pop or tearing feeling in the shoulder that brings sharp pain, new weakness or trouble lifting the arm. Stop and contact your surgical team the same day, or get medical advice the same day if you have not had surgery.
- The shoulder feels as if it has slipped out of place, looks a different shape or suddenly locks so you cannot move the arm, or your hand turns cold, pale or blue. Go to an emergency department straight away, without driving yourself, and do not try to put the shoulder back in yourself.
From the clinic
The turn happens at the shoulder, so the elbow stays parked at your side the whole time. A small rolled towel held between the elbow and your ribs tells you straight away when it wanders, because the towel drops. The voice guide talks only about turning the arm outward. The video turns it both ways, bringing the hand in across the stomach as well, and this page follows the video.
Doing it sitting, as in seated shoulder external rotation, works just as well if standing is tiring. Once the turn is smooth and easy, a band adds resistance in each direction: shoulder external rotation with a band for the outward turn and shoulder internal rotation with a band for the inward one.
After shoulder surgery, including a rotator cuff repair, or after a shoulder fracture or dislocation, follow your surgeon's or physio's plan, and do only the movements and range they have cleared. Many plans allow only passive movement at first, where the arm is moved for you and its muscles stay relaxed.
The outward turn in particular is often held back for the first weeks after an operation to stop the shoulder slipping out at the front, a repair of the tendon at the front of the shoulder (subscapularis) or most shoulder replacements, so check how far out your plan lets you go. That same front tendon is what turns the arm in. So after a subscapularis repair or most replacements, turning the arm in under its own power is often off limits for the first weeks as well. If your operation was for a shoulder that slipped out at the back, it is the other way round: the inward turn across the stomach is the one that is often limited.
Written and checked by the PocketPhysio editorial team. Last updated 2026-09-28.
This page is general education, not a diagnosis or a personal treatment plan. If you have pain, an injury or a health condition, see a physiotherapist or doctor before starting new exercises.