
Part of Frozen shoulder
Frozen shoulder exercises by stage, and the ones to avoid
Warning signs, and when to get help
What exercises help in the freezing stage?
Exercise is the mainstay of treatment throughout. OrthoInfo puts physical therapy aimed at shoulder flexibility first among the treatments, and says heat beforehand can make the stretching and movement work easier. That is why a warm shower before a session earns its five minutes for a lot of people. Do not use heat on skin that has lost feeling or cannot feel heat properly, because it can scald or burn without you noticing.
While pain is the thing stopping the arm, the job is to keep the joint moving without stirring it up. Pendulum swings are the first choice because they need nothing: lean forward, let the arm hang, and move it from the body rather than from the shoulder. They are easy to repeat several times a day, which matters more than any single session.
Then add a stick, which can be a broom handle or a walking stick. In shoulder flexion with a stick and shoulder external rotation with a stick the good arm does the lifting and the sore shoulder goes along for the ride. Move back and forth inside the range that feels comfortable instead of treating it as a stretch, and keep any holds short.
One cue saves people a lot of wasted effort on the external rotation. Squeeze a small rolled towel between your elbow and your ribs. If the towel drops, the elbow has left your side and the arm is lifting rather than turning, which is the commonest way this exercise gets done without working.
What about the frozen stage, when stiffness is the problem?
Once night pain has eased and the real trouble is how far the arm will go, the same movements get taken further. Keep the stick work going, hold the stretches longer, and take them to a firmer pull that you can still breathe through.
Wall slides come in here for overhead range. Keep the shoulder down and level, let the hand stop wherever it stops, and when you want more height, move your feet in toward the wall instead of hitching the shoulder blade up toward your ear. The cross-body shoulder stretch works the back of the shoulder, and isometric shoulder external rotation starts waking up the muscles that turn the arm outward without asking the joint to travel.
This is the stage people find most discouraging, because the pain has improved and the arm has not. The three stages explains why those two things move on separate schedules.
What to add in the thawing stage
As range returns, strength becomes the gap. Months of avoiding the arm leave the shoulder muscles underused, and reaching a shelf needs more than range of movement. Start light: a band for shoulder external rotation and internal rotation, and a resistance band row for the muscles between the shoulder blades.
Keep stretching alongside the strength work rather than swapping one for the other. The sleeper stretch belongs at this stage because you lie on the sore shoulder to do it, so leave it out while lying on that side still hurts.
The frozen shoulder program groups all ten exercises into the three stages with videos, and how long frozen shoulder lasts sets out how slow this part usually is.
How hard should a frozen shoulder stretch feel?
Firm enough to feel a pull, gentle enough that your breathing does not change. The JOSPT clinical practice guideline recommends stretching with the intensity matched to how irritable the shoulder is, and warns that going beyond painful limits may lead to worse results (Kelley and colleagues, 2013).
There is evidence behind the gentler approach. Diercks and Stevens followed 77 people in a Dutch study and compared intensive physiotherapy, meaning passive stretching and manual mobilization, against supportive care with exercises kept inside pain limits. At two years the gentler group had the better results. It was not a randomized trial, so it is supporting evidence rather than proof.
Mild aching that settles within an hour or two is normal. A shoulder that is sorer the next morning, or night pain that has returned, means you overdid it, so step back for a few days. A Cochrane review of manual therapy and exercise concluded that it may not work as well as a steroid injection in the short term and called for better trials, which is a fair summary of how strong the exercise evidence actually is (Page and colleagues, 2014).
When should you not use this program?
Two situations need a different plan. If you have had a manipulation under anesthesia or a capsular release, the weeks afterward follow the protocol your surgeon and physio give you, not this page. The same goes for a shoulder that stiffened after a fracture or an operation, where the stage of bone or tendon healing sets the limits.
If you have high blood pressure, breathe steadily through every hold and never hold your breath. If the shoulder was painful rather than stiff to begin with, check you are on the right page: a painful tendon that still moves freely is covered by the rotator cuff tendinopathy program, and shoulder pain when lifting your arm explains how the two differ.
Exercises that can help
Six of the ten in the program, spread across the three stages. Pick the stage your shoulder is in this week rather than the one you would like to be in, and keep the earlier work going as you add the later. Each exercise page carries its own numbers, and your physio will adjust them to your shoulder.
 Pendulum exercise for the shoulder
 Shoulder flexion with a stick
 Shoulder external rotation with a stick
 Wall slides with a towel
 Cross body shoulder stretch
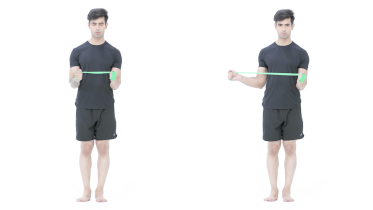 Shoulder external rotation with band
When to see a physio or doctor
See a physio (physical therapist) before you settle into a program if you have not had the shoulder examined, if the stiffness came on after an injury, or if you are not sure the diagnosis is right. The stretch intensity and the point at which you move between stages are set much better after an assessment than from a web page.
Go back if two or three months of consistent work change nothing, if night pain is still ruining your sleep, or if the shoulder starts getting stiffer again. Warning signs and how fast to act on each are listed below.
Related exercise programs
Warning signs
Get emergency help now
- Chest pain or tightness, which may spread to your arm, neck or jaw, or shoulder or arm pain that comes with shortness of breath, sweating or feeling sick. This can be a heart attack. Call emergency services straight away.
- The shoulder feels as if it has slipped out of place, looks a different shape or suddenly locks so you cannot move the arm, or the pain is severe after a fall or an injury. Go to an emergency department straight away, without driving yourself, and do not try to put the shoulder back in yourself.
- Your arm, hand or fingers turn cold, pale, blue or gray compared with the other side. Call emergency services or go to an emergency department straight away, and do not drive yourself. The blood supply to the arm may be blocked.
- You have a fever or feel unwell, or the shoulder is hot, red and swollen. This can be a joint infection. Go to an emergency department straight away.
Get help today
- Sudden, very bad shoulder pain, or you suddenly cannot lift or move your arm at all. Get medical help the same day.
- The pain started after a fall, a pull or another injury, especially if the arm has been weak since, for example you cannot lift it out to the side or hold it up. This can be a broken bone or a torn tendon. Get medical advice the same day, and say how it happened and that the arm has been weak since, because UK shoulder surgeons advise urgent referral for a rotator cuff tear caused by an injury.
- Severe pain in both shoulders that has come on recently. Get medical advice the same day.
- You are over 50 and have aching and stiffness in both shoulders, often in the neck or hips too, that is worst in the morning and lasts more than 45 minutes after you get up. This can be an inflammatory condition (polymyalgia rheumatica) rather than frozen shoulder. If you also get a new headache, pain or tenderness at your temples or on your scalp, or jaw pain when you eat or talk, get medical advice the same day, and if your vision changes, call emergency services. Even without those extra signs, see your doctor within a few days about the aching and stiffness.
- Pins and needles or numbness in the arm that does not go away, no feeling in part of the arm, or weakness that is getting worse. Get medical advice the same day. For pain spreading down the arm from your neck, ask for an urgent appointment with your doctor. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- Pain at night or at rest that is constant, that no rest or change of position eases at all, and that keeps getting worse. If you are being treated for cancer now, contact your cancer team the same day.
Book an appointment
- Pain at night or at rest that is constant, that no rest or change of position eases at all, and that keeps getting worse. If you have had cancer, now or in the past, or are losing weight without trying, see your doctor sooner, within a day or two, and mention it. This applies even if the pain is not getting worse.
- Night pain is common with this condition, but get checked within a few days if the pain is constant, no rest or change of position eases it at all, and it keeps getting worse.
- New shoulder pain and you have had cancer, now or in the past, or you are losing weight without trying. See your doctor within a day or two and mention it.
Common questions
Should I stretch a frozen shoulder through the pain?
No. How hard you stretch should match how irritable the shoulder is, which is what the JOSPT clinical practice guideline recommends, and the same guideline warns that stretching beyond painful limits may lead to poorer results (Kelley and colleagues, 2013). In 77 people, Diercks and Stevens found that keeping movement inside pain limits left the shoulder better off at two years than intensive passive stretching and mobilization did. The groups were not randomized, so that backs the gentler approach without proving it. A useful test: stretch to a pull you can breathe through, not a pain that makes you hold your breath.
How many times a day should I do frozen shoulder exercises?
More often and shorter beats once and hard, particularly while the shoulder is painful. Common practice in the painful stage is a few minutes of pendulum swings, 3 to 5 times a day, with the stick exercises 1 to 3 times a day and short holds or none. Once stiffness is the limit, stretches are often held for 20 to 30 seconds and repeated 3 to 5 times, once or twice a day. There is no research-backed best dose, so treat those as starting points your physio will change.
Can frozen shoulder exercises make it worse?
They can stir it up, which is not the same as damaging it. The signs you went too hard are a shoulder that is sorer the next morning than it was the morning before, or night pain that had settled and has come back. If that happens, drop back a step for a few days rather than stopping altogether, because a shoulder left alone gets stiffer. Pain that is severe, constant and unrelieved by any position belongs on the warning list on this page instead.
Which frozen shoulder exercise should I start with?
Pendulum swings, if the shoulder is painful, because they need no equipment and no setup, so you can fit them into the day several times. Add a stick next, since using both hands lets the good arm do the lifting and the sore shoulder only has to go along. Wall slides and band work come later, once the shoulder tolerates them. If you are not sure which stage you are in, start lower than you think.
References
- Kelley MJ, Shaffer MA, Kuhn JE, et al. Shoulder pain and mobility deficits: adhesive capsulitis. Clinical practice guidelines linked to the International Classification of Functioning, Disability, and Health from the Orthopaedic Section of the American Physical Therapy Association. Journal of Orthopaedic and Sports Physical Therapy. 2013;43(5):A1-A31. https://doi.org/10.2519/jospt.2013.0302
- Page MJ, Green S, Kramer S, et al. Manual therapy and exercise for adhesive capsulitis (frozen shoulder). Cochrane Database of Systematic Reviews. 2014;(8):CD011275. https://doi.org/10.1002/14651858.CD011275
- Diercks RL, Stevens M. Gentle thawing of the frozen shoulder: a prospective study of supervised neglect versus intensive physical therapy in seventy-seven patients with frozen shoulder syndrome followed up for two years. Journal of Shoulder and Elbow Surgery. 2004;13(5):499-502. https://doi.org/10.1016/j.jse.2004.03.002
- American Academy of Orthopaedic Surgeons. Frozen shoulder. OrthoInfo. https://www.orthoinfo.org/en/diseases--conditions/frozen-shoulder/
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-18.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.