
Flat feet exercises and physiotherapy
Warning signs, and when to get help
What are flat feet?
Flat feet, also called fallen arches (pes planus), means the inner arch of your foot sits low or presses flat on the ground when you stand. The NHS describes them as common and usually nothing to worry about. Most children have flat feet when they are young, and the arch usually develops between the ages of 3 and 10. If your flat feet do not hurt, the NHS advice is that you do not need to do anything, and they should not stop you doing any activities, including sports.
Some people do get symptoms. The NHS lists an ache along the inner arch, pain around the ankle or lower leg, and shoes that wear out quickly. A flat foot that still shows an arch when you sit or rise onto tiptoe is called a flexible flat foot, and the review of insoles for adults further down looked at this type.
Painful flat feet and a collapsing arch
The foot that needs more attention is one that was not flat before and is now changing. OrthoInfo, from the American Academy of Orthopaedic Surgeons, calls this progressive collapsing foot deformity, and older names for it are adult acquired flatfoot and posterior tibial tendon dysfunction. It often starts with the tendon of the tibialis posterior, a muscle whose tendon runs behind the bony bump on the inside of your ankle and helps hold up the arch. When that tendon weakens, the arch can slowly sag and put extra strain on the ligaments and joints around it.
It is more common in women and in people over 40, and OrthoInfo lists obesity, diabetes and high blood pressure as risk factors. Typical signs are pain along the inside of the foot and ankle, pain and weakness with activity, and trouble standing for long. As the arch drops, pain can appear on the outside of the ankle too. It may start mild. OrthoInfo notes it can progress to a very painful flat foot that does not work well, so if your foot is newly flattening, get it checked rather than waiting.
A simple sign is whether you can rise onto tiptoe on that leg alone. OrthoInfo explains that this needs a healthy tibialis posterior tendon, which is why doctors and physios use it as a test.
Why does exercise help painful flat feet?
Most of the research is on the tendon problem, not on flat feet in general. In a trial of 36 adults with early tibialis posterior tendon problems, every group wore orthoses and stretched for 12 weeks (Kulig and colleagues, 2009). Those who also did resistance exercise for the tendon improved more than those who only had orthoses and stretching, and the group doing slow lowering (eccentric) exercise improved the most. A later trial found that a moderate home strengthening program added little to orthoses and stretching over 12 weeks, although both groups improved (Houck and colleagues, 2015).
A 2018 systematic review found only 3 trials, with 93 people in total (Ross and colleagues, 2018). It found moderate effects on pain and disability when eccentric strengthening was added to stretching and orthoses. It also concluded that high-quality research is scarce and that the trials reported their exercise doses poorly. So strengthening has some support and is a reasonable thing to try, but the evidence is thin.
For painful flexible flat feet without a tendon problem, there is even less trial evidence. The NHS includes foot stretches and exercises among the treatments that can help with pain or stiffness, and it is clear that they will not change the shape of your feet. The aim of this program is a foot and ankle that are stronger and less sore, not a higher arch.
Insoles, orthoses and shoes: what the evidence says
The evidence for insoles and orthoses is weaker than many people expect. A systematic review of 13 studies in adults with flexible flat feet found no high-level evidence for orthoses (Banwell and colleagues, 2014). It found good to moderate evidence that they improve some measures of function, such as steadiness in standing and the energy it takes to walk, but only low-level evidence that they reduce pain. In the tendon trials above, every group wore orthoses and every group improved, but without a group that had no orthoses, those trials cannot show how much came from the insoles.
For shoes, the NHS suggests wide, comfortable shoes with a low heel. A podiatrist or physio can advise whether ready-made insoles are enough or custom orthoses are worth trying for you.
With a painful tibialis posterior tendon, OrthoInfo lists cutting back on the activities that make it worse, ice on the sorest area, anti-inflammatory painkillers and an ankle brace. If you are pregnant, the NHS advises avoiding anti-inflammatory painkillers such as ibuprofen and naproxen unless a doctor or pharmacist tells you to take them. In some cases a walking boot or short cast is used for 6 to 8 weeks to rest the tendon. Ask a pharmacist if you are not sure a medicine is safe for you. If you are overweight, OrthoInfo advises losing weight, and swapping some walking or standing for cycling or swimming lowers the load while the tendon settles.
What we notice about flat feet in the clinic
Most flat feet we are asked about were brought in by somebody else's opinion. A running shop, a coach, a relative, a photo taken from behind at the beach. Nothing hurts, nothing is getting worse, and the person has come in to find out whether they need fixing. They do not. That conversation takes about two minutes and is one of the more satisfying ones we have, because people walk out with permission to forget about their feet.
The painful ones arrive with a story about load, not shape. A new job on your feet, a week of holiday walking in flat sandals, a house move, a return to running after years away, a change in body weight. The feet did not suddenly become wrong. The amount of work going through them changed, and the arch was the part that complained first.
The tendon kind looks different again, and it creeps. People notice it in a photograph, or because one shoe is wearing down on the inside while the other is not, or because standing at a kitchen counter has become something they shift about during. The ache sits on the inside of the ankle, just behind and below the bony bump, and some people feel it in the arch. When we ask them to rise onto tiptoe on that leg alone, as the section above describes, the answer is often a surprise to them.
Four things go wrong early. Spending real money on insoles before finding out whether a cheap pair changes anything. Stretching the calf hard into the painful end of the range, when stopping short of pain on the inside of the ankle is the whole instruction. Trying single leg heel raises on the first day because they read that it is the test. And going barefoot on hard floors all day at home, which plenty of people with a sore arch feel worse after, and which costs nothing to test over a week of paying attention.
The cue that matters most across this whole program is where the weight sits on your foot as you rise. Keep it over the big toe and the second toe. If the weight drifts to the little toe side and the ankle tips outward, the muscle you came here to strengthen has stopped working and the calf is doing all of it.
How to use this program
If your flat feet do not hurt, you do not need this program. If your pain is mainly under the heel, the plantar fasciitis program may suit you better. If your flat feet ache, pick the stage that matches your foot today. If you are unsure, start at stage 1, and move up when the current stage feels easy and your foot is no worse the next morning.
Stage 1 exercises should be pain free. From stage 2, mild discomfort during the exercises is usually acceptable if it settles soon after and your foot is no worse the next morning. If the arch or inner ankle is clearly worse the next day, the load was too much, so drop back a step rather than stopping altogether.
In the two main tendon trials, people did their strengthening exercises twice a day for 12 weeks, with 2 to 3 sets of 10 to 30 repetitions in one trial and 3 sets of 15 in the other (Ross and colleagues, 2018). Many home programs start lower, at 2 to 3 sets of 10 to 15 once a day, and each exercise page gives a typical starting dose. Calf stretches are usually held for about 30 seconds, 2 to 3 times on each leg. Your physio will adjust this to your foot and to what you need to get back to. Tendon pain settles slowly, and OrthoInfo notes it can last more than 3 months even with early treatment, so judge progress over weeks and months.
If you have high blood pressure, breathe steadily through every hold and never hold your breath.
Keep a hand on a counter or wall for the standing and balance exercises if you feel unsteady. If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, keep a hand on the support throughout, practice only when someone else is at home, ask your physio before the foam pad and single leg balance work, and ask your doctor or physio about a falls check. If you have diabetes or numb feet, check the skin of both feet after each session, and ask your doctor, podiatrist or physio before doing exercises that press or roll on the sole.
The exercise program
The exercises below carry their own stop signs and precautions. Open the line under an exercise and read them before you try it.
Stage 1: Settle a sore arch and start gently
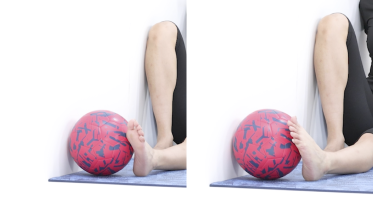
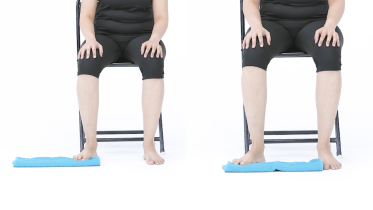
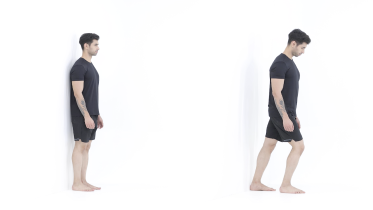
For an arch or inner ankle that aches with everyday walking or standing, and for the first weeks of any program. Keep these exercises pain free. The isometric inversion and the towel sweeps start working the deep muscle that holds up the arch (tibialis posterior) while the foot is supported. Towel scrunches work the small muscles under the foot. Both main trials on this tendon included calf stretches: do one with the back knee straight, then one with it bent. Stop each stretch short of any pain along the inside of the ankle, as a full stretch also squeezes that tendon. Use the strap version if standing stretches are hard to balance in.
 Isometric ankle inversion
Stop signs and precautions for the isometric ankle inversion
Before you start
- If you have been told you have a problem with the tendon on the inside of the ankle, or you are recovering from an ankle fracture or surgery, ask your physio how hard to press before you start.
When to stop and get help
- Sharp pain on the inside of the ankle, just behind or below the bony bump, or pain that builds with each hold.
- New pain or swelling along the inside of the ankle or the arch after the session.
- Your ankle feels unstable or gives way afterward.
 Foot towel sweeps
Stop signs and precautions for the foot towel sweeps
Before you start
- After an ankle fracture or foot surgery, ask your physio when to start.
When to stop and get help
- Sharp pain on the inside or outside of the ankle, or in the arch.
- Pins and needles, burning or numbness in the foot or toes.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
 Towel scrunches
Stop signs and precautions for the towel scrunches
Before you start
- After foot or toe surgery, such as bunion surgery, or a broken bone in the foot or toes, ask your surgeon or physio when to start.
When to stop and get help
- Sharp pain in the arch, the ball of the foot or the big toe joint.
- A cramp in the foot that does not ease when you rest and stretch the toes.
- Burning, pins and needles or numbness in your toes or sole.
 Calf stretch
Stop signs and precautions for the calf stretch
Before you start
- Calf stretching is often limited for the first months after an Achilles tendon repair, so follow your surgeon's and physio's instructions before you try this.
When to stop and get help
- Sharp pain in the Achilles tendon or at the back of the heel.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- Tingling, numbness or burning in the foot or down the leg.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
 Soleus stretch
Stop signs and precautions for the soleus stretch
Before you start
- Calf stretching is often limited for the first months after an Achilles tendon repair, so follow your surgeon's and physio's instructions before you try this. If your Achilles tendon is already painful, keep the stretch gentle and ask your physio whether it suits you. This matters most when the pain sits low, where the tendon joins the heel bone: stretching the ankle up presses on that spot and can make it worse.
When to stop and get help
- Sharp pain in the Achilles tendon or at the back of the heel.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- Tingling, numbness or burning in the foot.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
 Calf stretch with a strap
Stop signs and precautions for the calf stretch with a strap
Before you start
- After a torn Achilles tendon, whether or not it was repaired, calf stretching is usually avoided for the first months, because stretching can lengthen the healing tendon. Follow your surgeon's or physio's plan on when to start. After a recent ankle fracture, check with them first too.
- If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try the calf stretch with a strap. Getting down to the floor and back up bends the hip well past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Until you are cleared, the standing version keeps you off the floor.
When to stop and get help
- Sharp pain at the back of the heel or in the Achilles tendon.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- Tingling, numbness or pain that runs down the back of your leg into your foot. Ease off, and if it comes back each time, ask your physio before you carry on.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
Stage 2: Build strength in the arch muscles and calf
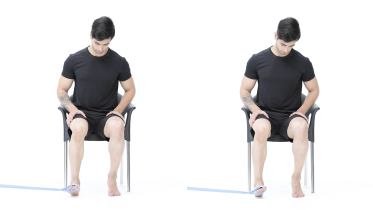
When everyday walking is comfortable and the stage 1 exercises no longer bring on pain. The band exercise loads the tibialis posterior against resistance. Take the slow return seriously: in a small trial, the group doing slow lowering (eccentric) work improved most. Calf raises on both feet come next. Once plain calf raises feel easy, try the version with the toes turned in, which is just a small change of position. The foam pad teaches the foot and ankle the small corrections you need on uneven ground.
 Ankle inversion with band
Stop signs and precautions for the ankle inversion with band
Before you start
- Take care after a recent sprain, because turning the foot inward is the same direction the ankle rolls in a common sprain. Keep the turn small and pain free, and ask your physio when to add the band. The same goes after an ankle fracture or surgery.
When to stop and get help
- Sharp pain on the inside of the ankle or along the arch, or pain that climbs as you work through the set.
- Swelling after the session, or the ankle giving way.
 Calf raises
Stop signs and precautions for the calf raises
Before you start
- After an Achilles tendon repair or ankle surgery, calf raises usually come in at a set stage of your surgeon's protocol, often on both feet before one. Check with your physio before you start.
- After a knee or hip replacement, or other leg surgery, follow your surgeon's or physio's plan, and hold a counter or a sturdy chair back for the whole set. Rising onto your toes puts your weight forward onto a smaller base, which is where the balance goes.
When to stop and get help
- Sharp pain in the Achilles tendon, heel or arch.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
- Achilles or heel pain that is clearly worse the next morning. Ease off and check with your physio.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- Your ankle gives way, or you lose your balance.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Calf raise with toes turned in
Stop signs and precautions for the calf raise with toes turned in
Before you start
- If you have had surgery on the ankle or Achilles tendon, check with your physio before you start.
When to stop and get help
- Sharp pain in the ankle, Achilles tendon, heel or knee.
- The ankle wobbles badly or gives way, or you start to lose your balance.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
 Standing balance on a foam pad
Stop signs and precautions for the standing balance on a foam pad
When to stop and get help
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You start to fall and need the support to stop yourself.
- Sharp pain in an ankle or knee, or an ankle that gives way.
- Your feet feel newly numb or tingly, or your balance has been slipping over recent weeks. Get medical advice within a few days, and leave out eyes-closed work until you have been checked. If the numbness or tingling spreads quickly up your legs or into your hands, get medical advice the same day. If your legs also feel stiff, heavy or weak, walking suddenly becomes hard, you have trouble breathing or swallowing, or you have trouble controlling your bladder or bowels, call emergency services.
Stage 3: Heavier single leg work and balance
When 2 to 3 sets of calf raises on both feet feel easy and your foot is no worse the next morning. Rising onto tiptoe on one leg needs a healthy tibialis posterior tendon, so single leg heel raises are a good goal to work toward, with your fingertips on a counter for balance. The eccentric calf raise is the step in between: up on both feet, down slowly on the sore one. Single leg balance, then balance while passing a ball, prepares the foot for longer walks and uneven ground.
 Eccentric calf raise
Stop signs and precautions for the eccentric calf raise
Before you start
- After an Achilles tendon repair, this exercise only comes in at the stage your surgeon's protocol allows, so check with your physio rather than starting on your own.
When to stop and get help
- A sudden sharp pain in the Achilles tendon or heel. Stop the set.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
- Tendon pain that is clearly worse the next morning and still has not settled a day later.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- You cannot stay balanced on the step, or the ankle gives way.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
 Single leg heel raise
Stop signs and precautions for the single leg heel raise
Before you start
- After an Achilles tendon repair or ankle surgery, calf raises usually come in at a set stage of your surgeon's protocol, often on both feet before one, so a single leg rise comes later still. Rising onto one foot puts more load through that tendon than the same movement on two, so check with your physio before you start.
- After surgery on the big toe joint, or a break or a stress fracture in the bones behind it, ask your surgeon or physio when to start. If that joint was fused it cannot bend upward, so pushing through the big toe side does not apply to you: keep your weight spread across the ball of the foot instead, without rolling onto the outer edge.
- Wait until your surgeon's protocol and your physio both say you are ready.
When to stop and get help
- Sharp pain in the calf, Achilles tendon or ankle, or pain that keeps building through the set.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
- You lose your balance or the ankle gives way.
- The Achilles tendon or calf is clearly more painful or stiff the next morning. Check with your physio before the next session.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
 Single leg stance
Stop signs and precautions for the single leg stance
Before you start
- If you have had a hip or knee replacement, or other hip or knee surgery, get the go-ahead from your surgeon or physio before you try single leg stance. Standing on the operated leg alone comes at a set stage of rehab, and some hip operations limit how high the knee can lift in the first months after surgery.
When to stop and get help
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You lose your balance and cannot steady yourself with your support.
- Sharp pain in the hip, knee or ankle of the standing leg.
 Single leg balance with ball pass
Stop signs and precautions for the single leg balance with ball pass
Before you start
- If you have injured a knee in the past, ask your physio before you add a wobble board: in the trial this training rests on, overuse knee injuries went up among the players who had injured a knee before (Verhagen and colleagues, 2004).
When to stop and get help
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You nearly fall, or have to grab the counter to stay on your feet.
- Sharp pain in the standing ankle or knee, or the ankle gives way.
Doing these exercises well
Isometric ankle inversion is a press, not a movement, and the common fault is turning the whole leg in from the hip so the ankle does nothing. Keep the working knee straight, the toes pointing up, and build the push up gradually instead of shoving the ball into the wall. If you can only feel it in your hip, you are not on the right muscle yet.
Foot towel sweeps need a thin towel on a hard floor. On carpet the towel catches and the exercise quietly becomes nothing. Keep your heel planted and let the toes grip and drag a new section each time, because sliding the foot over the top of the towel leaves the small muscles under the foot out of it. Towel scrunches have the same tell: if your whole leg is moving, the foot has stopped working.
The three stretches are where this program most often goes wrong. In the calf stretch, the soleus stretch with the back knee bent, and the strap version, stop short of any pulling along the inside of the ankle, as stage 1 says, because a full stretch squeezes the very tendon you are trying to settle. More stretch is not better here. It is the one place on this page where going harder reliably makes things worse.
Ankle inversion with a band is judged on the way back, not the way in. Turn the foot in steadily, then take 2 to 3 seconds to let the band pull it out again, and if it snaps back you have either too much band or too little attention. That slow return is the part the trial evidence above favored.
In calf raises and the toes turned in version, lower as slowly as you lift and keep the weight over the big toe. Only a small turn of the feet is needed in the second one, and if your knees start to twist or knock together the turn has gone too far. The eccentric calf raise is the honest bridge to the single leg heel raise: up on both, down slowly on the sore one. Fingertips on a counter are for balance, not for hauling yourself up.
The balance work is not a test of nerve. Standing balance on a foam pad, single leg stance and single leg balance with a ball pass all teach the foot the small corrections it needs on uneven ground, and they teach them just as well with a hand resting on the counter. Read the precautions in the section above before you start the foam pad and the single leg work.
How long this takes, and what to tell a coach
Judge this in months, not weeks. Tendon pain on the inside of the ankle is slow, and the OrthoInfo figure quoted above, of more than 3 months even with early treatment, is a fair expectation, so two weeks of exercises tells you almost nothing. What tells you something is time on your feet: how long you can stand or walk before the ache starts, and whether the evening ache is gone by morning. Write that down once a week rather than rating the pain daily, because the weekly picture moves in one direction and the daily one does not.
The marker to watch over the longer run is the single leg heel raise. How many you can do on the sore side compared with the other one, and whether the heel comes up high rather than barely leaving the floor. That changes slowly and it changes for real reasons.
On a bad day, drop to the stage 1 exercises, keep the supportive shoes on, split your standing into shorter spells and skip the single leg work. Do something rather than nothing. For a coach or a trainer, the message is that strength work stays and the running volume, the hills and the jumping come down for a while, then go back up in small steps. If you stand all day for work, the useful requests are a mat to stand on, a chance to sit for part of the hour, and shoes you can actually fasten properly rather than slip on.
When to see a physio or doctor
The NHS advises seeing a doctor if your feet are painful, stiff, weak or numb, if you often get foot or ankle injuries, or if you have problems with walking or balance. It also advises getting checked if you did not have flat feet before, or if only one foot is affected. A physio or podiatrist can assess the arch and the tendon, set your starting stage and advise on insoles. If you have diabetes, some foot changes need checking the same day, and the warning signs below explain which ones.
OrthoInfo advises considering surgery if the pain does not get better after several months of appropriate treatment, so if your foot is not improving, ask to see a specialist. If you have had surgery on your foot or ankle, follow your surgeon's program rather than this page. This page is for adults. If your child has flat feet that hurt, feel stiff or affect only one foot, get them checked by a doctor or physio.
For physiotherapists
This page gives patients a starting program for painful flexible flat foot and early progressive collapsing foot deformity (PCFD), which OrthoInfo also calls adult acquired flatfoot or posterior tibial tendon dysfunction. Screen with the single limb heel rise and the "too many toes" sign from behind, compare sides, and check whether the deformity corrects when the foot is unloaded. A rigid deformity, or one that keeps progressing, needs an orthopedic opinion rather than a loading program alone.
In people with diabetes or neuropathy, rule out active Charcot neuroarthropathy before loading. NICE NG19 advises suspecting it with redness, warmth, swelling or deformity, even without pain, and referring within 1 working day to the multidisciplinary foot care service, with non-weight-bearing treatment until then. The patient warning signs on this page ask for advice the same day.
The trial evidence is small. Kulig and colleagues (2009) randomized 36 adults with stage I or II PTTD to 12 weeks of orthoses and stretching, with or without concentric or eccentric resisted foot adduction in plantarflexion at a 15 repetition maximum load. The Foot Function Index improved in all groups, most with eccentric work and least with orthoses and stretching alone. Houck and colleagues (2015) gave 39 people with stage II TPTD a prefabricated orthosis and stretching, with or without home strengthening, and found the strengthening minimally effective as an add-on at 12 weeks.
Ross and colleagues (2018) included 3 RCTs (n=93) and found moderate effects (SMD 0.6 to 1.2) for eccentric strengthening added to stretching and orthoses. They found load, tempo and progression poorly reported, so no firm dosing recommendation is possible. They also note that calf stretching into full dorsiflexion compresses the tendon behind the medial malleolus, so keep stretches short of medial ankle pain. For flexible pes planus in general, Banwell and colleagues (2014) found no high-level evidence for orthoses, good to moderate evidence for improved physical function and low-level evidence for pain relief. Base progression on the 24-hour response rather than a fixed sheet, and use the single limb heel rise as a practical marker over time.
Warning signs
Get emergency help now
- Part of your foot or a toe turns cold, pale, blue or black. Call emergency services or go to an emergency department straight away, and do not drive yourself, as the blood supply to the foot may be blocked.
Get help today
- Same day: you have diabetes or numb feet, and one foot becomes hot, swollen or red, or changes color or shape, with or without pain. Take your weight off that foot straight away and get advice the same day from your doctor or your diabetes foot team. This can be Charcot foot, where the bones and joints of the foot are damaged and the foot can collapse. Do not exercise that foot until it has been checked. If you also have a fever or feel very unwell, or redness is spreading up your foot or leg, go to an emergency department.
- The foot is hot, red and swollen, or you have a fever or feel unwell. Get medical help the same day, and go to an emergency department if you feel very unwell. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: you have diabetes or numb feet and find a new blister, cut or sore on your foot, especially one you did not feel, a wound that smells or is leaking, or new pain in your foot that you cannot explain. Get it seen by your doctor or foot team the same day. If you also have a fever or feel very unwell, redness is spreading up your foot or leg, or part of your foot or a toe turns black, go to an emergency department.
- Same day: a burn, a scald or a blister on your foot or lower leg from hot water, a hot floor or pavement, a hot water bottle, an electric blanket, a heat pad, or sitting with your feet near a fire or radiator. Keep your weight off that foot and get it seen by your doctor or foot team the same day, however small the mark looks and even if it does not hurt. A foot that cannot feel heat can be burned deeply before you notice, and a burn on a numb foot can turn into an ulcer. If you also have a fever or feel very unwell, redness is spreading up your foot or leg, or part of your foot or a toe turns black, go to an emergency department.
- Same day: a sore, ulcer or wound on your foot that your team already knows about gets bigger or deeper, starts to smell or to leak more, the skin around it turns red, hot or puffy, or it has not started to heal. Get advice from your doctor or foot team the same day rather than waiting for your next appointment, and keep your weight off that foot. If you also have a fever or feel very unwell, redness is spreading up your foot or leg, or part of your foot or a toe turns black, go to an emergency department.
- The pain started with a fall, a twist or a sudden pop on the inside of the ankle, and there is swelling or bruising, or you cannot put weight on the foot. Stop the exercises, keep your weight off that foot as much as you can and get it checked the same day, even if you can still walk on it.
- A calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- The pain is there at night or at rest as well as when you stand and walk, and it is getting worse. If you are being treated for cancer now, contact your cancer team the same day.
Book an appointment
- The arch on one foot has dropped, suddenly or over weeks or months, or you can no longer rise onto tiptoe standing on that leg alone, especially with pain or swelling along the inside of the ankle. See a doctor within a few days. This can be a sign that the tendon that holds up the arch (tibialis posterior) is failing, and it can keep getting worse without treatment. If you have diabetes or numb feet, a change in the shape of your foot is a same-day sign, as described above.
- The pain is there at night or at rest as well as when you stand and walk, and it is getting worse. If you have had cancer, now or in the past, or are losing weight without trying, see your doctor sooner, within a day or two, and mention it. This applies even if the pain is not getting worse.
- The pain is there at night or at rest as well as when you stand and walk, and it is getting worse. See your doctor within a few days.
- You have new numbness, tingling, burning or loss of feeling in the foot or toes. Book an assessment with a doctor or physio in the next week or two. If it came on over hours or days, started after an injury, is spreading, or comes with weakness in the foot or toes, get medical advice the same day.
Common questions
Can exercise fix flat feet?
Do not expect exercise to give you a permanent new arch. The NHS puts it plainly: shoes, insoles, foot stretches and exercises can ease pain or stiffness, but none of them reshapes the foot. Where exercise does help is with a painful foot, and most of all with a sore tibialis posterior tendon. In a small trial, people who added strengthening to orthoses and stretching improved more than those who had orthoses and stretching alone (Kulig and colleagues, 2009), although a second trial found a home strengthening program added little (Houck and colleagues, 2015). Your physio will adjust the exercises to your foot.
Are flat feet a problem?
Usually not. The NHS describes flat feet as common and usually nothing to worry about, and says they should not stop you doing any activities, including sports. They are worth checking if they hurt, feel stiff, weak or numb, if you did not have flat feet before, or if only one foot is affected.
Do insoles help flat feet?
They can help some people, but the evidence is weaker than many expect. A systematic review in adults with flexible flat feet found good to moderate evidence that orthoses improve some measures of function, such as steadiness in standing and the energy it takes to walk, but only low-level evidence that they reduce pain (Banwell and colleagues, 2014). If your flat feet do not hurt, you do not need them. A podiatrist or physio can tell you whether ready-made insoles are enough or custom orthoses are worth trying.
What shoes are best for flat feet?
The NHS suggests wide, comfortable shoes with a low heel. There is no single best shoe, so go by comfort and by how your feet feel in the evening. If the inside of your foot or ankle aches, ask a podiatrist or physio whether an insole in those shoes is worth adding.
Can I run or play sport with flat feet?
If they do not hurt, yes. The NHS says flat feet are usually nothing to worry about and should not stop you doing any activities, including sports. Nobody needs to fix a foot shape that is not causing a problem. If your arch or the inside of your ankle does hurt with running, that is about load rather than shape, so cut the distance or the hills back to what the foot tolerates, keep the strength work going, and build up again from there. Pain along the inside of the ankle that gets worse week by week, or an arch that is dropping, needs checking before you train through it.
Why do my flat feet ache more in the evening?
Because it adds up. The arch and the muscles and tendons that support it have been working all day, so an ache that builds through the afternoon and settles overnight is the pattern we hear most, and it usually tracks how much standing and walking you did. Use that: two shorter spells on your feet with a sit down between them often feel better than one long one, even when the total is the same. Pain that is there at night or at rest and is getting worse is different, and the warning signs below say what to do about it.
Can adults get flat feet later in life?
Yes. The NHS lists stretching of the tissues in the feet from injury, aging or extra body weight as one of the less common causes. OrthoInfo describes a form that gets worse over time, progressive collapsing foot deformity, which often starts with the tibialis posterior tendon and is more common in women and in people over 40. A foot that was not flat before and is now flattening, especially on one side, should be checked by a doctor.
References
- NHS. Flat feet. Page last reviewed 24 June 2025. https://www.nhs.uk/conditions/flat-feet/
- American Academy of Orthopaedic Surgeons. Progressive Collapsing Foot Deformity (Flatfoot). OrthoInfo. https://www.orthoinfo.org/en/diseases--conditions/posterior-tibial-tendon-dysfunction/
- Kulig K, Reischl SF, Pomrantz AB, Burnfield JM, Mais-Requejo S, Thordarson DB, Smith RW. Nonsurgical management of posterior tibial tendon dysfunction with orthoses and resistive exercise: a randomized controlled trial. Physical Therapy. 2009;89(1):26-37. https://doi.org/10.2522/ptj.20070242
- Houck J, Neville C, Tome J, Flemister A. Randomized controlled trial comparing orthosis augmented by either stretching or stretching and strengthening for stage II tibialis posterior tendon dysfunction. Foot and Ankle International. 2015;36(9):1006-1016. https://doi.org/10.1177/1071100715579906
- Ross MH, Smith MD, Mellor R, Vicenzino B. Exercise for posterior tibial tendon dysfunction: a systematic review of randomised clinical trials and clinical guidelines. BMJ Open Sport and Exercise Medicine. 2018;4(1):e000430. https://doi.org/10.1136/bmjsem-2018-000430
- Banwell HA, Mackintosh S, Thewlis D. Foot orthoses for adults with flexible pes planus: a systematic review. Journal of Foot and Ankle Research. 2014;7:23. https://doi.org/10.1186/1757-1146-7-23
- Diabetes UK. Charcot foot and diabetes. Last reviewed 8 November 2024. https://www.diabetes.org.uk/about-diabetes/looking-after-diabetes/complications/feet/charcot-foot
- Diabetes UK. Serious foot problems and diabetes. Last reviewed 24 December 2024. https://www.diabetes.org.uk/about-diabetes/looking-after-diabetes/complications/feet/serious-foot-problem
- National Institute for Health and Care Excellence. Diabetic foot problems: prevention and management. NICE guideline NG19. Published 26 August 2015, last updated 11 October 2019. https://www.nice.org.uk/guidance/ng19
- NHS. Sepsis. Page last reviewed 14 May 2026. https://www.nhs.uk/conditions/sepsis/
- NHS. Deep vein thrombosis (DVT). Page last reviewed 30 April 2026. https://www.nhs.uk/conditions/deep-vein-thrombosis-dvt/
- NHS. Ibuprofen for adults. Page last reviewed 27 August 2025. https://www.nhs.uk/medicines/ibuprofen-for-adults/
- NHS. Naproxen. Page last reviewed 25 June 2026. https://www.nhs.uk/medicines/naproxen/
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-29.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.