Ankle dorsiflexion in long sitting
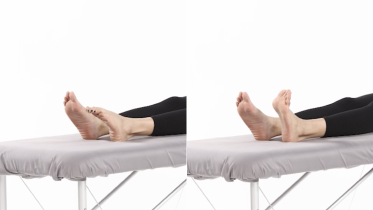
Ankle dorsiflexion in long sitting means sitting with both legs straight out in front of you and pulling one foot up toward your shin, then pointing it away again. Long sitting just means sitting with your legs out straight, on a bed, a couch or the floor. The knee stays flat the whole time, so only the ankle moves and no weight goes through the foot. Physios often give it to get a stiff ankle moving again, for example after a sprain or once a cast or boot comes off.
How to do the ankle dorsiflexion in long sitting
- Sit on a bed, treatment couch or mat with both legs straight out in front of you. Rest your hands on the surface beside your hips, or lean back against pillows or a wall if sitting upright strains your back.
- Let both legs relax, with the backs of your knees resting down on the surface.
- Pull the toes and the front of one foot up toward your shin, as far as it goes without pain. Your heel stays on the surface and your knee stays flat.
- Pause there for a second or two.
- Then point the same foot away from you, toes toward the far end of the bed, and pause again.
- Keep moving that one foot up and down at a slow, even pace while the other leg rests. Change legs if your program includes both.
What you should feel
Work along the front of your shin as the foot comes up, and a stretch in the calf, sometimes reaching behind the knee, because the knee is straight. Pointing the foot brings a light squeeze in the calf.
Common mistakes
- Letting the knee bend or lift off the bed as the foot comes up.
- Curling or clawing the toes instead of moving the whole foot at the ankle.
- Turning the foot in or out rather than moving it straight up and down.
- Going fast, so the foot flicks through the movement without reaching either end.
How often
Many programs use 10 to 20 slow movements with each foot, 2 to 3 times a day, with a brief pause at each end. Your physio will adjust this.
Stop and check with your physio if
- Sharp pain at the front or back of the ankle, or pain that builds with each movement instead of easing as the ankle loosens up.
- Pins and needles, burning or numbness in the foot that is new or getting worse. If it stays after you stop, or keeps getting worse, get medical advice the same day.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- You suddenly become short of breath, get chest pain or pain in your upper back that may be worse when you breathe in, cough up blood, your heart beats very fast, or you faint. Call emergency services straight away, even if your leg looks normal, as this can be a blood clot in the lungs (pulmonary embolism).
- Emergency: while you are in a cast or boot, your toes turn blue, white or pale, or feel cold. Do not wait to see if raising your leg helps. Go to an emergency department straight away, and do not drive yourself. The cast or boot may be cutting off the blood supply, or pressure may be building up inside the leg (compartment syndrome), and both need checking quickly.
- In a cast or boot, the pain gets worse, your toes feel numb, tingle or burn or look more swollen, or the cast or boot feels too tight. Stop, raise your foot above your hip, keep moving your toes and contact your fracture clinic or get medical advice straight away. If you wear a boot, loosen the straps but keep it on. If you cannot move your toes, the pain is severe even after painkillers, or the numbness, tingling, burning or swelling has not settled within 30 minutes of raising your foot, go to your fracture clinic or an emergency department straight away, and do not drive yourself.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
From the clinic
The voice guide keeps it simple: legs straight, toes up toward your head, and the knee flat on the table while the foot moves up and down. In the video only one foot works at a time and the other rests. Don't worry if the foot comes up less than it does with the knee bent. A straight knee puts the calf muscles on stretch before the ankle has moved far, so this is normal.
If sitting with your legs out straight is uncomfortable, ankle pumps done in a chair move the ankle the same way. Once the foot moves freely, ankle dorsiflexion with a band adds resistance, and the ankle alphabet takes the ankle through more directions.
After an ankle fracture or ankle surgery, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. Still wearing a boot? Check with your fracture clinic whether you may take it off to exercise. After a torn Achilles tendon, whether or not it was repaired, pulling the foot up past a right angle stretches the healing tendon, and many plans limit how far the foot may come up for the first months. Your surgeon or physio will tell you how far is safe.
Written and checked by the PocketPhysio editorial team. Last updated 2026-09-28.
This page is general education, not a diagnosis or a personal treatment plan. If you have pain, an injury or a health condition, see a physiotherapist or doctor before starting new exercises.