Active ankle inversion
Active ankle inversion means turning the sole of your foot inward, toward the other foot, using your own muscles. You sit with both legs straight out in front of you and turn one foot in at a time, moving only at the ankle. Programs often use it to bring back movement in an ankle that has stiffened after a fracture, a sprain or weeks in a cast or walking boot.
How to do the active ankle inversion
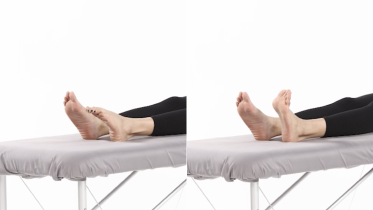
- Sit on a bed, a firm couch or the floor with both legs straight out in front of you. Sit up tall and rest your hands on the surface beside your hips.
- Start with both feet relaxed and your toes pointing up toward the ceiling.
- Slowly turn the sole of one foot in, toward the other foot. The foot may point down a little as it turns, which is normal. Only that foot moves, and your kneecap keeps pointing up.
- Go as far as is comfortable, pause for a moment, then let the foot come back to the middle.
- Repeat at an even pace, then do the same with the other foot if your program includes both sides.
What you should feel
Light work along the inside of the shin, and a gentle stretch over the outside of the ankle as the foot turns in. A stiff ankle may only move a little at first, and that is fine.
Common mistakes
- Rolling the whole leg in from the hip. Watch your kneecap: if it turns, the movement is not coming from the ankle.
- Rushing, or forcing the foot past the point of comfort.
- Slumping or leaning back as you go. Sit tall and use your hands for support.
How often
Many programs use 10 to 15 slow turns with each foot you are working, 2 to 3 times a day, often alongside other ankle movements. Your physio will adjust this.
Stop and check with your physio if
- Sharp pain in the ankle, or pain that builds with each turn and is still there after you stop.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- You suddenly become short of breath, get chest pain or pain in your upper back that may be worse when you breathe in, cough up blood, your heart beats very fast, or you faint. Call emergency services straight away, even if your leg looks normal, as this can be a blood clot in the lungs (pulmonary embolism).
- Swelling around the ankle that is clearly worse after your session and still worse the next morning. Let your physio know before you carry on.
- Emergency: while you are in a cast or boot, your toes turn blue, white or pale, or feel cold. Do not wait to see if raising your leg helps. Go to an emergency department straight away, and do not drive yourself. The cast or boot may be cutting off the blood supply, or pressure may be building up inside the leg (compartment syndrome), and both need checking quickly.
- In a cast or boot, the pain gets worse, your toes feel numb, tingle or burn or look more swollen, or the cast or boot feels too tight. Stop, raise your foot above your hip, keep moving your toes and contact your fracture clinic or get medical advice straight away. If you wear a boot, loosen the straps but keep it on. If you cannot move your toes, the pain is severe even after painkillers, or the numbness, tingling, burning or swelling has not settled within 30 minutes of raising your foot, go to your fracture clinic or an emergency department straight away, and do not drive yourself.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
From the clinic
Turning in is the direction the ankle usually rolls in a common sprain, so keep the movement smooth and never force the end of the range. Once it is comfortable, your physio may add resistance with isometric ankle inversion and then ankle inversion with band. Active ankle eversion turns the feet the other way from the same position, and many programs pair the two.
After an ankle fracture or ankle surgery, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. Early on after a repair of the ligaments on the outside of the ankle, surgeons usually limit turning the foot in, so ask which directions you may move it in at your stage. If you are still in a cast or boot, do only the movements your team has given you.
Written and checked by the PocketPhysio editorial team. Last updated 2026-09-26.
This page is general education, not a diagnosis or a personal treatment plan. If you have pain, an injury or a health condition, see a physiotherapist or doctor before starting new exercises.