Sit to stand with a side reach
Sit to stand with a side reach gives the stand an errand. From a high stool you reach your weaker arm up and out to that side, keep reaching while you rise, and let your weight travel onto the leg underneath the reach. Hardly anyone stands up simply to be standing, and it is the standing up while the hands are busy somewhere else that catches people out at a kitchen cupboard. Physios use it to get a reader leaning into a side that tends to be left out, usually once plain sit to stand is going well.
How to do the sit to stand with a side reach
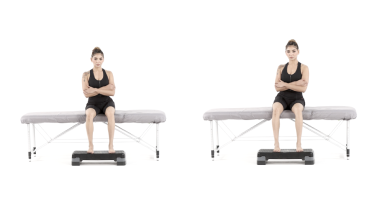
- Sit tall on a steady, high stool with your hips a little higher than your knees.
- Set your feet hip width apart, directly under your knees.
- Lift your weaker arm and reach diagonally up and out to that side, as if toward a high shelf. The other hand can rest against your chest, as in the video, or wherever it is comfortable.
- Keep reaching as you lean forward and stand up, letting your weight travel onto the leg on the reaching side.
- Straighten your hips fully at the top and hold the reach for a moment.
- Bring the arm down, sit back onto the stool slowly and repeat.
What you should feel
Work in the thigh and buttock on the reaching side, with a stretch along that side of your trunk. The weight shift can feel odd if you usually lean on your other leg.
Common mistakes
- Reaching without shifting, so your weight stays on the stronger leg.
- Arching your back or flinging the arm up to gain momentum.
- Reaching so far that you overbalance sideways.
- Finishing with your hips still bent.
How often
Many programs begin with 5 to 10 reaching stands, done for 1 to 3 sets on most days. Your physio will adjust this.
From the clinic
The reach is doing something the other versions cannot. Lifting the arm up and out pulls your weight toward that side while the legs are still halfway through the stand, so the hip and the muscles down that side of the trunk have to hold you over the foot instead of letting you topple back toward the stronger leg. Of the six sit to stand versions in our library, this is the only one where an arm has a job other than pushing or staying out of the way, which is also why it is the one most like reaching into a high cupboard with a kettle in your other hand.
In our stroke rehab program it shares the standing stage with the staggered feet version. The two attack the same problem from opposite ends, and a physio may give you one, the other, or both.
The stool must be firm and still; a bar stool that swivels or rolls is not suitable. Sit back down at once if you start to lose your balance.
The whole exercise can be gone through faithfully and come to nothing if the arm goes up while the weight stays where it was. You end up with an ordinary stand and a raised hand. The test is underfoot: something should change under the foot on the reaching side, and if nothing does, it is the weight shift that needs the attention rather than a higher reach.
A sudden loss of balance is different. Call emergency services straight away for any sign of a stroke, even if it goes away: sudden dizziness with unsteadiness or falling over, a face that droops on one side, an arm you cannot lift or keep up, slurred or muddled speech, weakness or numbness on one side of your body or face, sudden blurred vision, double vision or loss of sight, or a sudden severe headache. If one side is already weak or numb from an earlier stroke, new or suddenly worse weakness or numbness is a sign, and every other sign in this list still counts.
A helper can support the arm under the elbow and forearm, but should never lift or pull it by the hand, and should not take it above shoulder height unless your physio has shown them how.
For another way to get the weaker leg working, try sit to stand with staggered feet.
If chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
Before you start
- If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try sit to stand with a side reach. The forward bend as you come up from the stool can take the hip past a right angle if the seat is not high enough, and many surgeons ask you to avoid that for the first months after some operations. After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- If one side is weaker after a stroke or another brain or nerve condition, ask your physio first whether this exercise suits you. Take care when the reaching arm is the weak one: reach only as high as you can control and never force the arm up with your other hand. If that shoulder hurts, or you have been told it has partly slipped out of its socket (subluxation), ask your physio how far and how high you may reach before you start.
- Put a counter or rail on the side you reach toward, or ask someone to stand there, because that is the way you are most likely to tip. If you have fallen in the past year or feel unsteady, keep practice to times when a helper is there. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet.
When to stop and get help
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services.
- Pain in the shoulder of the reaching arm, or a sharp pain in your hip, knee or back.
- You tip toward the reaching side and cannot stop yourself.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-11.
This page is general education, not a diagnosis or a personal treatment plan. If you have pain, an injury or a health condition, see a physiotherapist or doctor before starting new exercises.