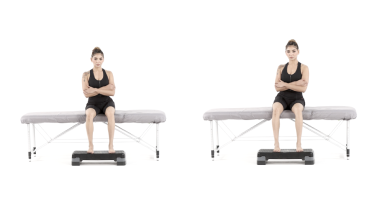
Scooting sideways on the bed
Scooting sideways on the bed travels along the edge while you sit on it, which is how you line up with a chair, a wheelchair or your own pillows. You sit near the front, tuck your feet back, place your stronger hand on the bed a little out to that side, then lean forward and push through that hand and both feet to lift your bottom across. Small moves, repeated, cover whatever distance you need. It differs from the forward and back version in one way that matters: this one needs an arm that can take your weight.
How to do the scooting sideways on the bed
- Sit upright on a firm bed, with the brakes on if it has wheels, with your feet about hip width apart. Shuffle forward until you are near the front edge, then tuck your feet back so they sit under your knees. The man in the video rests his feet on a low bench because the treatment bed is high.
- Place the hand of your stronger arm flat on the bed, a little way out to the side of your thigh, on the side you want to move toward. Rest your other hand in your lap.
- Lean forward over your knees so the weight comes off your bottom, then push down through your hand and both feet to lift your bottom just clear of the bed.
- Swing your hips a short way toward your hand and sit back down gently.
- Move your feet and hand across to line up again, and repeat until you have moved as far as you need. Sit tall before you do anything else.
What you should feel
Effort in the stronger arm, the thighs and the buttocks as you lift, with your trunk working to steady you as you land. Each move only covers a short distance.
Common mistakes
- Sitting too far back, so you cannot lean forward enough to lift.
- Trying to travel a long way in one push.
- Leaving your feet behind, so they end up pointing away from where you face.
- Moving toward the end of the bed without checking how much room is left.
How often
Use it whenever you need to move along the bed or line up for a transfer. As practice, many programs do 3 to 5 moves in one direction and back again, once or twice a day. Your physio will adjust this.
From the clinic
The lift happens in two parts and the first one is the lean. You cannot raise something you are still sitting on, so the weight has to come off your bottom and onto your feet before the arm has anything to lift. When a move fails, the shoulder usually gets the blame and the real cause is sitting too far back to lean far enough forward. Shuffle to the front edge first and the same arm will often manage it easily.
This is the move that comes before a transfer. Once you can travel along the edge under control, you can line your hips up with a chair, which is what both the sliding board transfer and the squat pivot transfer assume you have already done. In our stroke rehab program it sits in the same stage as those two transfers, which is the clearest statement of what it is for.
Check the bed before every move rather than after it. You are traveling sideways while facing forward, so the end of the mattress arrives out of view, and the landing is the moment you are least able to correct anything.
This page explains the general technique, not a stroke rehab program. Your physio or occupational therapist works out with you how to do it, and whether a helper is needed, if one side is weaker after a stroke or another condition. The video shows the version that moves toward the stronger arm. If both arms are strong, you can push with either hand.
A firm mattress matters, because a soft edge can sink as you land, and if the bed has wheels they should be locked. Check how much room is left before each move and stop well short of the end of the bed. Let a weak arm rest in your lap, supported, so it does not hang or get caught, and never let anyone lift you by it. When you can move along the bed with control, the sit to stand using armrests page covers the next step of getting up.
You may feel a little unsteady as you land while you learn. A sudden loss of balance is different. Call emergency services straight away for any sign of a stroke, even if it goes away: sudden dizziness with unsteadiness or falling over, a face that droops on one side, an arm you cannot lift or keep up, slurred or muddled speech, weakness or numbness on one side of your body or face, sudden blurred vision, double vision or loss of sight, or a sudden severe headache. If one side is already weak or numb from an earlier stroke, new or suddenly worse weakness or numbness is a sign, and every other sign in this list still counts.
Before you start
- If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try scooting sideways on the bed. Leaning well forward to lift your bottom bends the hips past a right angle, especially on a low bed, and many surgeons ask you to avoid that for the first months after some operations.
- If the arm you push with has had surgery or a fracture, ask your surgical team or physio before you put weight through it.
- After recent heart or chest surgery, get your surgeon's or surgical team's okay first, because lifting your bottom clear of the bed puts your weight through one arm and pulls across the healing breastbone. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
- Have a helper beside you while you are learning, and if you have fallen in the past year, or feel less steady than usual today, wait until they are there. If a stroke or another condition has weakened one side of your body, ask your physio or occupational therapist first how to do it and whether you need someone with you.
When to stop and get help
- The wrist or shoulder you push with hurts, or the shoulder of a weak arm starts to ache.
- You feel yourself sliding off the bed or about to fall. Stop, sit back and let the person helping you steady you.
- You feel dizzy, lightheaded or faint, or the room seems to spin, as you move in bed or sit on its edge. Stop, lie back down on the bed if you can, and keep still until it passes. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of keeping still, or your vision suddenly blurs or goes double, call emergency services.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- You suddenly become short of breath, get chest pain or pain in your upper back that may be worse when you breathe in, cough up blood, your heart beats very fast, or you faint. Call emergency services straight away, even if your leg looks normal, as this can be a blood clot in the lungs (pulmonary embolism).
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-11.
This page is general education, not a diagnosis or a personal treatment plan. If you have pain, an injury or a health condition, see a physiotherapist or doctor before starting new exercises.