
Part of Hip osteoarthritis
Hip arthritis sleeping position, and what to do about night pain
Warning signs, and when to get help
What is the best sleeping position for hip arthritis?
If you are in the first months after a hip replacement, stop here. Do not try either of the two set-ups below, or any of the other positions, the roll or the way out of bed further down this page, until your own team has told you which of them you may use. Your surgical team decides which positions you may sleep in, which side you may lie on, and how long padding stays between your knees, and those limits depend on how the hip was operated on, so they differ from one team to the next. Where hip precautions are in use they commonly rule out bending the hip past a right angle and sitting with your legs crossed (NHS), and many teams add not turning the operated leg inward or twisting on it. After an operation done from the front of the hip, some surgeons limit taking the leg behind you or turning it outward instead (OrthoInfo). The NHS recovery advice names no sleeping position at all, so ask your own team which positions your precautions cover and for how long, and work from hip replacement rehab rather than this page in the meantime. When you ask, put these four to them by name: lying on the operated side, raising your upper body on a wedge or on pillows, rolling over with your knees together, and the forward lean as you stand up from the bed. The section on turning over and getting out of bed says why each one matters.
Side lying on the unaffected side is where most people start. The sore hip is then on top, carrying nothing, and the job of the padding between your legs is to stop that top leg dropping inward across your body. A stiff hip resists exactly that position, so a pillow that has flattened by midnight is no help: the detail is what decides whether the set-up works. Use something thick enough that the upper knee finishes level with the upper hip, and run it down to the shin so the lower leg has nowhere to sag. A standard pillow folded once is about right for most adults.
Lying on your back is the other one, and it suits a hip that cannot tolerate side lying at all. The adjustment it needs is padding under both knees, a folded towel or a small pillow, so the hip rests a few degrees bent instead of pulled out straight. A joint that has lost range dislikes being held at its end point for seven hours, and that is what a flat bed does to a hip in full extension.
From about 28 weeks of pregnancy the NHS advises going to sleep on your side rather than on your back, because it says sleeping on your back after that point can double the risk of stillbirth. So use the side lying set-up above, on the unaffected side with padding between your legs, and leave lying on your back until after the birth. The NHS also says not to worry if you wake up on your back: settle onto your side again and carry on. Hip and pelvic pain in pregnancy is also managed differently, and your midwife or maternity physio leads that.
There is no trial comparing sleeping positions in hip osteoarthritis, so be clear about the evidence level here. Everything above is clinical practice, which is a reasonable basis for a pillow and a poor basis for certainty. Treat it as an experiment: one set-up, three or four nights, and the thing you are measuring is how the hip feels for the first minute after you stand up, not how it feels as you drop off.
Why does hip arthritis hurt more at night?
Stiffness is half of it. An arthritic joint tolerates being held still much less well than a healthy one, and a night is the longest spell of stillness in your day. The ache builds slowly, and you usually feel the cost of it at the moment you get up, not while you lie there. That is the version a pillow and a short movement routine can help.
The other half is the condition's own pattern. AAOS lists pain that flares up with vigorous activity, and says that over time painful symptoms may occur more often, including during rest or at night. So night pain appearing where there was none is partly a change in the hip and not a change in your bed, and it needs reporting, not just cushioning.
There is a duller explanation too. At 3am nothing else is happening. The same ache that sat below your attention all day has the room to itself.
The two shapes of night pain are worth keeping apart. Pain that depends on the position, which means it comes on when you settle one way and eases when you move, is behaving like a mechanical problem and is what this page addresses. Pain that is there in every position, does not care what you do with pillows, and keeps getting worse week by week is a different pattern, and the last section of this page says what to do about it.
If you are not certain the pain is coming from the hip joint at all, hip pain at night works through the other common causes, and where hip arthritis pain is felt covers the location pattern that fits the joint itself.
Which side, and what to do when neither one works
Most people have already given up on the painful side by the time they look this up. That is reasonable: the hip is then carrying the weight of your upper body against the mattress, in a position it cannot easily escape. You do not need to train yourself back onto it.
The good side is the default, with the padding described above. If you keep waking having drifted onto the sore hip, put a second flat pillow lengthways behind your back. A physical barrier works where intention does not.
Then there are the hips that will not settle either way, which is common once both hips are involved or once a shoulder is in the picture too. Work through these in order:
- Back lying with padding under the knees, as above, with a pillow under the small of the back if that feels better.
- Back lying with the whole upper body raised slightly, which some people find takes the edge off a stiff hip. A wedge does it, or pillows arranged so the support runs from your waist up to your head in one slope. Do not stack them under your head alone, which bends your neck forward and leaves the hip where it was.
- Side lying with more padding than you think you need, enough to lift the top leg a little and not just keep it level.
If you are more than about 28 weeks pregnant, use side lying with padding between your legs rather than either of the back positions above.
If the sore hip is best lying on that side and worst on the other, raise that with your clinician. Pain over the bony point on the outside of the hip, tender to press and clearly worse lying on that side, fits greater trochanteric pain rather than the joint, and that changes the plan. Outer hip pain covers it too.
Mattress, pillows and the bed itself
Nobody has shown that any mattress treats hip osteoarthritis, and we would not spend money on one for that reason. What does make a measurable difference is the height of the bed.
Perch on the edge of your bed and look at your knees. If they sit higher than your hips, the bed is too low for you, and every morning starts with the hardest version of standing up. The fix is cheap: a firmer mattress sits higher than a soft one, bed risers raise the frame, and a folded blanket or a firm mattress topper lifts you a little higher again. The same principle runs through the whole day with chairs, which the hip osteoarthritis program covers.
Pillows, in order of usefulness: the one between your legs, the one behind your back, then the one under your knees if you are on your back. Buying a shaped leg pillow is optional and the ones sold for this do the same job as a folded pillow. Spend the attention on thickness, not on the product.
A soft, deep mattress is the one thing to leave alone. It feels kind for the first minute, then lets the hip settle into the position you were trying to avoid, and makes getting out harder as well. If that is what you are sleeping on and you cannot replace it, a firm topper is the cheaper correction.
Turning over, and getting out of bed at night or in the morning
Turning over is the movement that costs people the most sleep. The move to practice is keeping both knees together as a single block while you roll, with the padding staying put between them, rather than letting the top leg lead and swing across first. It takes a few nights to become automatic, and a sore hip does not forgive that one movement.
Getting up has a sequence that is kinder on a stiff hip than sitting straight up and swinging a leg out.
- Before you move, do 10 slow ankle pumps and bend and straighten each knee a few times. About 30 seconds of movement takes the edge off the first step.
- Roll onto your side facing the edge of the bed, knees together.
- Drop both feet over the edge together while you push up through the lower elbow and the upper hand, so your trunk comes up as the legs go down.
- Sit on the edge for a few seconds before you stand, with your feet flat and a hand on the bed. If you feel light-headed as you come up, sit back down and stay there for a minute before you try again. That is commoner at night, and commoner if you take medicines for blood pressure.
- Slide the sore foot slightly forward, lean your nose over your toes and stand. That is the same movement as sit to stand, which is why it is in the set below.
The same sequence works at 2am, with four things set up before you go to bed, not worked out in the dark. Put a light within reach of the bed and use it, every time. Keep the route to the bathroom clear of rugs, cables and anything you have put down. Have slippers or flat shoes that grip beside the bed, because socks on a hard floor are how people go over, and bare feet on a hip that is not ready to take weight are not much better. And if you use a stick, a frame or crutches, keep it where you can reach it from sitting on the edge of the bed, not across the room: the first few steps at night, on a stiff hip that has not moved for hours, are the ones you are least steady on.
If you are in the first months after a hip replacement, none of this overrides your surgical team. They set which positions and movements are allowed, how long to keep padding between your knees at night, and when that changes. These are the four this page asked you at the top to put to them by name, and this is why each one matters, because each takes the hip toward a position precautions usually cover: lying on the operated side, raising your upper body on a wedge or pillows, which bends the hip more than lying flat does, rolling with the knees together, which brings the operated leg toward the middle of your body, and the forward lean over your toes in step 5, which bends the hip further than sitting does. Follow their plan and hip replacement rehab rather than this page, and new or rapidly worsening pain, a wound that is red, hot or leaking, a fever, or a calf that is newly swollen or getting more swollen, warm or tender all mean contacting that team the same day rather than waiting.
So does a hip that clunks and feels as if it slipped and went back, even if it settles at once. So does a fall or a knock on that hip, even a small one and even if you can still walk afterward: keep your full weight off that leg until it has been checked, because a break in the bone around a new hip is not always obvious at first. Both are in the warning list below in full, along with the signs of a dislocation, which is an emergency.
What helps in the hours before bed
Move the day's biggest walk earlier, because the evening is where a lot of night pain gets decided. A long walk after dinner gives an irritable hip no time to settle before you lie on it, and the same distance in the morning often costs nothing by bedtime. Splitting one long walk into two or three shorter ones is the standard adjustment, and like everything else in this section that is practice rather than trial evidence.
Warmth before bed suits most stiff hips. A warm shower, a bath if you can get in and out safely, or a wrapped heat pack over the front of the hip for 15 to 20 minutes. Do not use heat on skin that has lost feeling or cannot feel heat properly, because it can scald or burn without you noticing. Skip it altogether on a hip that is hot, red or swollen, which needs checking instead.
Do the short movement routine from the exercise set below while you are still up, not once you are in bed.
Painkillers and anything to do with timing them is a conversation for your doctor or a pharmacist, not for this page, and never stop or change a prescribed medicine on your own.
Before you try the exercises
While you exercise, stop straight away if you have any of these: chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause. What to do next is in the warning signs below. If you have high blood pressure, breathe steadily through every repetition and never hold your breath. Check with your doctor before you start if you have a heart or lung condition, or blood pressure that is not under control.
If you are pregnant and past the first three months, check with your physio before exercising flat on your back, as the heel slides are done lying down.
If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, keep a hand on the bed or a sturdy chair for every stand, practice only when someone else is at home, and ask your doctor or physio about a falls check. If you live alone, that rule still stands, so plan around it rather than ignoring it. Do the exercises that ask for someone to be at home at your physio appointments or in a class instead, keep to the lying and seated work when you are on your own, and ask your physio which of the standing exercises you may do alone. Keep your phone in a pocket rather than in another room, so you can reach it from the floor, and ask about an alarm you wear.
If you do fall and cannot get up, or you think you may have hurt your head, neck, back or hip, stay where you are, keep warm and call emergency services, or get someone to call for you. Do not let anyone haul you up first. That line and the rest of the fall routes, including what to do if you got up fine and only hurt later, are in the warning signs below.
If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try these exercises. Some operations limit this kind of work for the first months, so the timing depends on your surgery. If you have had a hip fracture, work from the program your surgical team and physio gave you rather than this list.
Exercises that can help
Two or three minutes of gentle movement before you lie down, and again before you stand up in the morning, is one of the few things that reliably helps a stiff hip at either end of the night. Heel slides and seated hip flexion are both small, unloaded movements, done on each leg in turn. Sit to stand is here because the first trip to the bathroom is where people struggle, and practicing it in daylight makes it safer in the dark. Do it from a chair or a bed that will not slide or tip, with flat shoes on rather than socks, and with a hand on the bed or the chair if you are at all unsteady. Many programs use 10 to 15 slow repetitions of the lying and sitting movements, once or twice a day, and 5 to 10 repetitions of sit to stand. Read the checks just above this list before your first session. Each exercise page gives its own numbers, and your physio will adjust this.
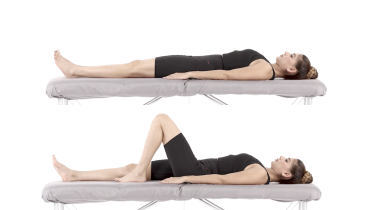 Heel slides
 Seated hip flexion
 Sit to stand
On a bad night, doing nothing is not a crime. These are small movements, and skipping them for a day changes nothing. Hip arthritis flare ups covers what to do with the rest of your program during a bad spell.
When night pain is a reason to get checked rather than managed
Most hip arthritis night pain is a positioning problem with a positioning answer. A few patterns are not, and these are the ones to act on rather than cushion.
Pain that is there in every position, does not ease when you change what you are lying on, and keeps getting worse week by week. That needs a doctor within a few days, sooner if you have had cancer at any point or are losing weight without trying, and the warning list below gives the exact timings.
A hip that is hot and swollen, or hip pain with a fever or feeling hot, cold and shivery. That is a same-day problem, and an emergency department if you feel very unwell.
New hip or groin pain after any fall, even a small one, if you are older, have low bone density or have taken steroid tablets long term. A broken hip is not always obvious, and people walk on them.
If you have had a hip replacement, sudden severe pain with a clunk, a leg that suddenly looks shorter or turned, or an inability to put weight on it is an emergency, and a new hip can become infected years later. Both are on the warning list below in full.
Beyond that, book a routine appointment with a doctor or physio if hip pain is stopping you sleeping, if it keeps coming back, or if it has not improved after 2 weeks of looking after it at home (NHS). Sleep loss is a legitimate reason to ask for help with a hip, not a minor complaint to apologize for, so say plainly at the appointment how many nights a week it is waking you. Treating hip arthritis without surgery covers what else is available.
Related exercise programs
Warning signs
Get emergency help now
- Emergency: if chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
- Emergency: a racing, pounding, fluttering or irregular heartbeat that does not settle when you rest, or that comes with dizziness, feeling faint or fainting, chest pain or shortness of breath. Call emergency services straight away. If it has already stopped, get medical advice the same day.
- Emergency: you have just fallen and cannot get up, or you think you may have hurt your head, neck, back or hip. Stay where you are, keep warm and call emergency services, or get someone to call for you. If you got up and walked without trouble and only notice pain later, use the same-day lines in this list instead.
- Emergency: you fell and cannot remember the fall or how it happened. Go to an emergency department straight away, and do not drive yourself. You may have blacked out or hit your head without knowing it.
- Emergency: you have had a fall or an injury and now have severe hip pain, or you cannot walk or put weight on the leg. Call emergency services or go to an emergency department. This can be a sign of a broken hip (hip fracture).
- Emergency: after a knock to the head, being very drowsy or finding it hard to keep your eyes open, confusion, a fit (seizure), new weakness or numbness anywhere in your body, new trouble understanding, speaking, walking or keeping your balance, new problems seeing or hearing, clear fluid coming from your ears or nose, bleeding from your ears or bruising behind them, a black eye when your eye was not hit, a dent in your head or a wound with something stuck in it, or a change in behavior. Call emergency services straight away. These can be signs of an injury to the brain.
- Emergency: after a knock to the head, you were knocked out, even for a moment, you cannot remember what happened just before or after, you have had a headache ever since, or you are being sick (vomiting). The same applies, even if you feel fine, if you take medicine that thins your blood, other than aspirin on its own, have a bleeding or clotting condition, have had brain surgery in the past, or had been drinking alcohol or taking drugs when it happened. Go to an emergency department straight away, and do not drive yourself.
- Emergency: tingling or loss of feeling in the hip or leg after a fall or injury. Call emergency services or go to an emergency department.
- Emergency: you have had a hip replacement and have sudden severe pain in your hip or groin, sometimes with a clunk or pop, and you cannot move the leg or put weight on it, or the leg suddenly looks shorter or turned in or out. Do not try to walk on it or push it back into place. Keep still and call emergency services or go to an emergency department, and do not drive yourself. Your new hip may have come out of its socket (dislocated), and a medical team needs to put it back.
- Emergency: your operated leg looks shorter than it did, or its foot turns in or out more than before, or the hip moves in an unusual way, even if the pain is not severe. Keep your weight off it and go to an emergency department straight away, and do not drive yourself. If you are in severe pain or cannot move the leg, call emergency services.
- Emergency: since your operation, you suddenly become short of breath, you get chest pain or pain in your upper back that may be worse when you breathe in, you cough up blood, your heart is beating very fast, or you faint. Call emergency services straight away, even if your leg looks normal. These can be signs of a blood clot in the lungs (pulmonary embolism).
- Emergency: pain, tingling, numbness or weakness in both legs, numbness or altered feeling around your genitals or bottom, or new trouble peeing or controlling your bladder or bowels. The same applies if you lose feeling in one leg. Call emergency services or go to an emergency department straight away. These can be signs of pressure on the nerves at the base of the spine (cauda equina syndrome).
Get help today
- Same day: the hip is hot and swollen, or the skin over it has changed color, or you have hip pain with a high temperature or feel hot, cold or shivery. Get medical help the same day, and go to an emergency department if you feel very unwell. A joint infection needs treatment quickly. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: at any time after your operation, even years later, new pain in your new hip along with a high temperature or feeling hot, cold or shivery, or a hip that becomes hot, red or swollen, which counts on its own, with or without pain and with or without a temperature. Contact your surgical team or get medical advice the same day. A new joint can become infected long after the operation, and that needs treating quickly. A normal temperature is not an all clear: OrthoInfo says fever is no longer considered a sign of an infection after a joint replacement, that the signs can be as little as mild redness and swelling and sometimes there are none at all, and that increased pain or stiffness in a joint that had been working well is one of them. So do not wait for a temperature before you report new or increasing pain in your new hip to your surgical team.
- Same day: you have had a hip replacement and your hip clunks and feels as if it partly slipped out of place and went back, even if it settles straight away and your leg looks normal. Stop the exercises, avoid the movement that brought it on, go back to your crutches or frame, and keep away from deep bending, crossing your legs and twisting on that leg until you have been seen. Contact your surgical team or get medical advice the same day. If the leg then looks shorter or turned, or you cannot move it or put weight on it, call emergency services.
- Same day: severe hip pain that came on suddenly without a fall, or pain that is getting worse quickly over a few days. Get medical advice the same day.
- Same day: you have had a hip replacement and, after a fall or a knock, even a small one, your hip, groin or thigh is newly painful, bruised or swollen, even if you can still walk and your leg looks normal. Stop the exercises, go back to your crutches or frame and keep your full weight off that leg, and contact your surgical team or get medical advice the same day. A break in the bone around a new hip is not always obvious at first, and walking normally on one can move the broken ends apart.
- Same day: new hip or groin pain after a fall, even a small one, if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time, even if you can still walk. Get medical advice the same day. A broken hip is not always obvious at first.
- Same day: after a fall, you are in pain, have hurt yourself or feel unwell, or you were on the floor for an hour or more, without any of the emergency signs above. Get medical advice the same day, even if you managed to get up.
- Same day: a leg or foot that is getting weaker, for example your foot drags, catches on the ground or slaps down when you walk (foot drop). Get medical advice the same day. If the weakness is getting worse by the hour, go to an emergency department.
- Same day: a calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Same day: you blacked out or fainted, even for a moment. Get medical advice the same day. Call emergency services instead if the person is not breathing, cannot be woken within 1 minute, has not fully recovered or has trouble speaking or moving, has chest pain or a pounding, fluttering or irregular heartbeat, fainted while exercising or lying down, is shaking or jerking, or was badly hurt.
- Same day: dizziness, lightheadedness, blurred vision or feeling faint when you stand up that is new for you, does not pass within a minute or two, keeps happening, or has made you fall. Sit or lie down, and get medical advice the same day. This can be a drop in blood pressure on standing (postural hypotension), a type of low blood pressure, which the NHS lists among the causes of falls, and your doctor can check it. Tell them about your medicines, because some can cause it. If it does not settle within a few minutes of sitting or lying still, call emergency services. If you faint, use the fainting line above.
- Same day: dizziness or feeling faint during or after exercise, other than the brief lightheadedness as you stand up covered in the line above, without any of the emergency signs above. Stop the exercises and get medical advice the same day. If you faint, it does not settle within a few minutes of sitting still, or you cannot stand or walk steadily, call emergency services.
- Same day: a child or teenager has sudden pain in the hip, thigh or knee, is limping, or cannot put weight on one leg. Get an urgent appointment with a doctor the same day. If they have a high temperature or seem very unwell, go to an emergency department. This page is for adults, and hip pain in children has different causes.
- Same day: hip or groin pain that is worse at night or does not ease with rest, and keeps getting worse. If you are being treated for cancer now, contact your cancer team the same day.
Book an appointment
- Within a day or two: hip or groin pain that is worse at night or does not ease with rest, and keeps getting worse. If you have had cancer, now or in the past, or are losing weight without trying, see your doctor sooner, within a day or two, and mention it. This applies even if the pain is not getting worse.
- Within a few days: hip or groin pain that is worse at night or does not ease with rest, and keeps getting worse. See your doctor within a few days.
- Within a few days: new groin or hip pain and you take steroid tablets long term, or have in the past, or you regularly drink a lot of alcohol. This can be a sign of a problem with the blood supply to the top of the thighbone (avascular necrosis). Book an appointment with your doctor within a few days and mention the steroids or alcohol.
- Routine: pain in your new hip that had settled and has come back, or pain that is getting worse month by month, for example in the groin or thigh when you first stand up and start to walk. This is not an emergency, but ask your surgical team for a review, as the parts of a new joint can loosen or wear over the years. Get medical advice the same day instead, not a routine appointment, if the hip also becomes hot, red or swollen, or you have a high temperature or feel hot, cold or shivery, or the pain is building week by week rather than month by month. A new joint can become infected years after the operation, and the two can feel similar at first.
Common questions
What is the best sleeping position for hip arthritis?
Side lying on the unaffected side, with enough padding between the legs that the top knee stays level with the top hip, suits most people. Lying on your back with a folded towel under both knees is the next one to try, because it keeps a stiff hip slightly bent instead of pulled straight. No trial has compared sleeping positions in hip osteoarthritis, so pick one, give it three or four nights, and judge it on how the hip feels when you stand up. If you are in the first months after a hip replacement, your surgical team sets which side you may lie on and which positions you may use, so follow them rather than this page.
Should I sleep on the painful side or the good side?
Start on the good side. The sore hip then carries nothing, and the padding between your legs stops it rolling inward and across your body, which is the position a stiff hip objects to. If the good side is where your other sore joint is, or you simply cannot drop off there, back lying is a legitimate alternative rather than a failure.
Is sleeping on my back bad for hip arthritis?
No, and the advice you will find online contradicts itself on this because nobody has tested it. The one adjustment to make is padding under the knees, so the hip sits a few degrees bent, not fully straight. From about 28 weeks of pregnancy the NHS advises going to sleep on your side rather than on your back, because it says sleeping on your back after that point can double the risk of stillbirth. So use side lying on the unaffected side with padding between your legs, and leave lying on your back until after the birth. The NHS also says not to worry if you wake up on your back: settle onto your side again and carry on. If you are in the first months after a hip replacement, your surgical team sets which side you may lie on and which positions you may use, so follow them rather than this page.
Where do I put the pillow?
Between the knees and shins, not between the thighs, and thick enough that the upper knee ends up level with the upper hip instead of dipping below it. A standard pillow folded once is usually about right for an adult. Then put a second, flatter pillow behind your back, which stops you drifting onto the painful side while you are asleep.
Why does my hip hurt more at night?
Partly because an arthritic joint stiffens when it is held still for hours, and partly because the pattern changes as the condition goes on. AAOS lists pain that flares up with vigorous activity, and says that over time painful symptoms may occur more often, including during rest or at night. The other half is simple: there is nothing else competing for your attention at 3am.
Does a firmer mattress help hip arthritis?
There is no good evidence either way for hip osteoarthritis, and we would not spend money on a mattress to treat a hip. What does matter is bed height. A bed low enough that your knees sit above your hips when you perch on the edge makes getting up harder than the night was, and a firmer or higher sleeping surface fixes that for less than the price of a mattress.
Why is my hip so stiff when I get out of bed?
Because it has not moved for hours. Morning stiffness that loosens within about 30 minutes fits osteoarthritis, and so does having none at all: from age 45, NICE accepts either of those in its advice on diagnosing it without an X-ray. Stiffness that is still there an hour or two later, or that affects several joints, should be mentioned to your doctor rather than worked around.
References
- National Institute for Health and Care Excellence. Osteoarthritis in over 16s: diagnosis and management (NG226). 2022. https://www.nice.org.uk/guidance/ng226
- American Academy of Orthopaedic Surgeons. Osteoarthritis of the hip. OrthoInfo. https://www.orthoinfo.org/en/diseases--conditions/osteoarthritis-of-the-hip/
- Hall M, Lawford BJ, Hinman RS, et al. Exercise for osteoarthritis of the hip. Cochrane Database of Systematic Reviews. 2026;(7):CD007912. https://doi.org/10.1002/14651858.CD007912.pub3
- NHS. Hip pain in adults. https://www.nhs.uk/symptoms/hip-pain/
- NHS. Head injury and concussion. https://www.nhs.uk/conditions/head-injury-and-concussion/
- NHS. Recovering from a hip replacement. Page last reviewed 6 March 2024. https://www.nhs.uk/tests-and-treatments/hip-replacement/recovering-from-a-hip-replacement/
- American Academy of Orthopaedic Surgeons. Total hip replacement. OrthoInfo. https://www.orthoinfo.org/en/treatment/total-hip-replacement/
- NHS. Osteoarthritis. https://www.nhs.uk/conditions/osteoarthritis/
- NHS. 27 weeks pregnant: the best sleeping positions during pregnancy. Best Start in Life week by week guide. https://www.nhs.uk/best-start-in-life/pregnancy/week-by-week-guide-to-pregnancy/2nd-trimester/week-27/
- NHS. Complications of a hip replacement. Page last reviewed 6 March 2024. https://www.nhs.uk/tests-and-treatments/hip-replacement/complications-of-a-hip-replacement/
- NHS. Low blood pressure (hypotension). Page last reviewed 11 July 2023. https://www.nhs.uk/conditions/low-blood-pressure-hypotension/
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-23.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.