
Part of Osteoporosis
Strength training for osteoporosis: how heavy, how often, and who was watching
Warning signs, and when to get help
How heavy should you lift with osteoporosis?
The guidance gives a dose and the internet gives a limit, and they are two different kinds of thing. That one distinction clears up most of the confusion on this subject.
The UK consensus statement recommends progressive resistance training on 2 or 3 days a week, at the maximum you can lift 8 to 12 times, building up to 3 sets for each exercise. It adds that lower intensity exercise with good technique is recommended before intensity goes up. Your physio will adjust this (Brooke-Wavell 2022).
Notice what that dose is made of. It is a proportion of your own strength, so it rises as you get stronger and it describes a 58 year old and an 84 year old equally well. A number of pounds does not do that. The Royal Osteoporosis Society says the same thing from the other end: there is not a specific weight that is safe or unsafe, it depends on your own body and on what feels right for you.
The consensus is also open about a choice it made. Earlier guidance recommended 8 repetitions at 80 to 85 percent of a one repetition maximum, and the group judged an 8 to 12 repetition maximum easier to apply outside a laboratory, while noting that supervised progressive resistance training at higher intensity is likely to have the greatest effect on bone density. So the dose you have been given is a usable version of a stronger one, chosen deliberately.
Is there a 10 pound limit with osteoporosis?
No. And the number is not simply unsupported, it is named in the literature as an example of what clinicians are asked to stop saying.
The Too Fit To Fracture Delphi panel recommends giving guidance on spine-sparing technique during daily activities and leisure, taking account of impairments, fracture risk, activity history and preference, rather than giving generic restrictions. The two examples of a generic restriction it names are lifting less than 10 lb (4.5 kg) and no twisting (Giangregorio 2015).
We went looking for the source of the number on the open web, because readers quote it constantly. What we found on the first page of results for this question was a patient forum thread, running to most of a results page on its own, in which members pass a 10 to 15 lb (4.5 to 6.8 kg) limit between themselves, one reports being told that people with severe osteoporosis should not lift heavy, and another reports being advised against lifting a 40 lb (18 kg) bag. None of it carried a source, and no national body page appeared alongside it.
That is a question with real demand and no answer published where people are looking. It is also how a figure nobody can trace turns into something everybody has heard. If you have been given a weight limit by your own clinician who knows your scan, your fracture history and how you move, that is different and it stands. A number from a forum is not.
What the heavy lifting trials actually did, and in whom
There is one trial everybody half remembers, and the specifics matter more than the headline.
LIFTMOR randomized 101 postmenopausal women, mean age 65, mean weight 63.1 kg (139 lb), with a T-score below minus 1.0, to 8 months of training or to a home-based low-intensity program. The training arm did twice-weekly, 30-minute, supervised sessions at 5 sets of 5 repetitions above 85 percent of a one repetition maximum. Bone density at the lumbar spine rose by 2.9 percent against a 1.2 percent loss in the comparison group, and at the femoral neck it rose 0.3 percent against a 1.9 percent loss. Compliance was 92 percent. There was one adverse event, a minor lower back spasm that cost 2 of 70 sessions (Watson 2018).
Three details in that paragraph are usually left out, and each one changes what you can take from it.
The entry criterion was a T-score below minus 1.0, which includes osteopenia as well as osteoporosis, and osteopenia is the larger group. Participants were screened for conditions and medications that affect bone and physical function, so the medically complicated reader was filtered out before the trial began. And the paper's own conclusion carries the condition inside the sentence: the training was effective and caused no adverse events under highly supervised conditions, in a sample described as otherwise healthy postmenopausal women with low to very low bone mass.
The same approach was then tested in men. LIFTMOR-M allocated 93 men, mean age 67, mean weight 82.1 kg (181 lb), with a mean femoral neck T-score of minus 1.6, to high-intensity resistance and impact training, to machine-based isometric work, or to a matched control group that was allocated rather than randomized, which is why its own title calls it semi-randomized. Bone density rose at the trochanter and the lumbar spine in the training arm against the control, and there were five minor adverse events across the two intervention arms (Harding 2020).
Did anybody check for spinal fractures?
Yes, directly. It is the result nobody quotes, and it is the one the question deserves.
The LIFTMOR participants were re-examined specifically for vertebral fracture, using lateral thoracolumbar bone density imaging, the semiquantitative Genant method and clinical measures of the upper back curve. There was no change in vertebral fracture classification in the training group, while a single new wedge deformity appeared in the comparison group, and the training group's standing-tall thoracic curve improved by 6.7 degrees against 1.6 in the comparison group. The paper's title states the finding plainly: high-intensity exercise did not cause vertebral fractures and improves thoracic kyphosis (Watson 2019).
Set beside that, the UK consensus looked for harm across 62 trials of exercise in this population. Eleven reported fractures during the study period, rarely attributable to the intervention, and the totals ran against expectation: 5.8 percent of exercise group participants fractured against 9.6 percent of controls. Its conclusion is that exercise is unlikely to cause a fracture, including a vertebral fracture, and does not need to be adapted according to fracture risk or a low bone density reading (Brooke-Wavell 2022). Read what that sentence is about, because it is the one most often stretched too far. It is about a scan result and a calculated risk score, not about a spine that has already broken: the same document sets out a separate and more cautious set of recommendations for people with a vertebral fracture or several low-trauma fractures, which is the next section of this page.
So two supervised trials in this population looked for vertebral fracture and did not find it, and a review of 62 trials found fewer fractures in the people who exercised. That is a stronger safety position than most readers have been given.
What changes when nobody is watching
The supervision in those trials is not a footnote to the results. It is part of them.
Every figure in the two sections above was produced in a supervised gym, with trained staff setting the load, in volunteers screened for other conditions, most of whom had osteopenia rather than established osteoporosis, and none of whom is described in those papers as having had a previous vertebral fracture. The reader of this page may be a 78 year old man with two previous spinal fractures, reading on a phone, in a commercial gym, with nobody watching.
Handing that reader a 5 by 5 above 85 percent of a one repetition maximum because a trial reported it safely would be an error of population, not of arithmetic. The protocol and its safety record came as a package, and the supervision was in the package.
What that means in practice is ordinary. Start with the 8 to 12 repetition dose, not the trial protocol. Get your starting load and your technique set by a physio (a physical therapist in the USA) once, which is usually a single appointment, and get it reviewed when the weights stop feeling hard. Healthy Bones Australia asks for more than one appointment: it recommends supervised exercise for people with diagnosed osteoporosis, and encourages anyone with the diagnosis, including people who have recovered from a fracture, to work with a physiotherapist or exercise physiologist. Where two national bodies differ like that, take the more cautious one if you are unsure which group you are in. Load up slowly enough that the increase is boring. And keep the spine out of the lift: hinge at the hips, keep the load close to your body, and do not bend and twist at once while you are holding something heavy, which the osteoporosis program sets out in full and osteoporosis posture and spine protection covers for daily life.
Finding that weight is the part nobody explains, and the Royal Osteoporosis Society is the one body that spells it out. Begin with something you can lift easily and add to it over weeks. If you cannot get through 8 repetitions with good technique, the weight is too heavy, so the next session goes lighter. If you reach 12 and feel you could carry on, it is too light. Lift and lower slowly, and if you cannot tell which it is, go lighter: a weight that is too light costs you a few weeks, and one that is too heavy costs you your technique on the last two repetitions, which is where it matters.
The same organization attaches a recovery instruction to the frequency, and the headline figure usually arrives without it. Spread your 2 or 3 days across the week and leave at least a day's rest between sessions. Three days in a row is not a keener version of this advice, it is a different and worse one, and muscle that has not recovered is muscle that lets your position go.
Four stop rules travel with this work. Stop the set when you cannot do the next repetition with good technique, even if you have not reached your number. The set ends there, and that is not a failure, it is the instruction. A repetition ground out with a rounded back is loaded spine flexion, which is the one thing the Australian position statement rules out by name (Beck 2017), so the count is never worth the position. If you have high blood pressure, breathe steadily through every repetition and never hold your breath. Put the weight down if you feel the strain in your back, which is the Royal Osteoporosis Society's own rule, and either drop the load or change your technique before you try again. And sudden back pain during or after a session, especially after a lift, a bend, a cough or a sneeze, is a same-day matter on this page rather than something to train through.
What changes if you have had a fracture in your spine
Different reader, different answer, and the published answer for this group is not a lighter version of the one above.
The UK consensus recommends individual advice from a physiotherapist for people with vertebral fractures or multiple low-trauma fractures, for both impact and progressive resistance training, at least at the start of a new program, and that recommendation is marked as expert consensus rather than evidence. In its own discussion of this group it goes past the start of the program, saying that tailoring the intensity of both impact and muscle-strengthening work, individually and progressively, under supervision, would often be appropriate. The Delphi panel goes further: where there is pain, more than one fracture, or a marked rounding of the upper back, it states that the risks of many activities may outweigh the benefits, and recommends a physical therapist consultation (Giangregorio 2015).
The evidence base for that group is genuinely thin, and saying so is more useful than pretending otherwise. A Cochrane review of exercise after osteoporotic vertebral fracture, covering 9 trials and 749 participants, concluded that there was not enough evidence to determine the effects of exercise on new fractures, falls or adverse events. It recorded four adverse events related to the exercise interventions across three trials, being a costal cartilage fracture, a rib fracture, knee pain and irritation from tape, on very low-quality evidence (Gibbs 2019).
Healing comes before any of it. The Royal Osteoporosis Society puts spinal fracture healing at 6 to 12 weeks, says movement does not affect the healing process, and advises waiting until the bone has healed, which can take up to three months, before building up strength exercises. The after-a-fracture section of the osteoporosis program has that sequence, and this page does not rebuild it or set a timeline of its own. Take your starting point from the clinician who knows your imaging.
That section has a shadow, and it is the reader who has had one of these fractures and does not know it. The Royal Osteoporosis Society says you may not always be aware a spinal fracture has occurred, and that the pain can be mistaken for something else, such as arthritis, so a diagnosis is not what puts you in this group. If you have lost height, your upper back has become more rounded, or you have back pain or pain that wraps around to your ribs with no clear cause, see your doctor before you start. A broken bone in the spine can cause any of them, and it does not always announce itself. If the pain came on suddenly, get medical advice the same day. Those signs are set out in full on osteoporosis posture and spine protection, and they matter more on this page than on most, because a weight in your hands is the one thing that loads a vertebra you have not had looked at.
Where to start, if you are starting from nothing
The commonest version of this question in clinic is not how heavy. It is where on earth to begin, and the answer is usually lower than people expect and progressed faster than they expect.
Bodyweight first. Osteoporosis Canada's own basic program starts with body weight and progresses to bands or weights, and names a squat, a lunge, a hinge or a bridge, with push, pull and press work alongside them. The chair squat is where most people begin, and sit to stand sits just below it on the days a chair squat is too much.
Then add resistance rather than repetitions. A band or a weight you can lift 8 to 12 times is the target, and the seated row with band is a reasonable upper body starting point. Back strengthening goes in at least twice a week, and the back extension on elbows is usually the first version of it.
Two things about the list below before you start it. The back extension is done lying face down on the floor, and for a lot of readers of this page getting down there and back up is the risky part rather than the lift, so if the floor is hard or unsafe for you, leave that one out for now: osteoporosis posture and spine protection has a version done in a chair, and your physio can tell you whether the floor ones are for you. And two of them have you on your feet, so use a chair that will not slide, keep a kitchen counter or a sturdy worktop within reach, and wear flat shoes that fit and grip rather than socks or bare feet. If you have fallen in the past year or feel unsteady, keep a hand on the support for every repetition and practice only when somebody else is at home.
One check applies even if nobody has ever mentioned a fracture to you, and this is the page where a weight goes into your hands. If you have lost height, your upper back has become more rounded, or you have back pain or pain that wraps around to your ribs with no clear cause, see your doctor before you start, and the same day if that pain came on suddenly. Not having a diagnosis is not the same as not having a fracture.
There is also a group this page cannot set a load for, and in osteoporosis it is not a small one. If you have had a hip replacement, a broken hip fixed with screws, a nail or a plate, or any operation on your spine, including cement injected into a broken vertebra, ask the team that operated what you may load and when, and start from their answer rather than from the dose on this page. Metalwork holds bone, it does not thicken it, and the bone it is anchored in is the thin bone that broke in the first place. In osteoporotic patients having spinal deformity surgery, hardware failure, a fusion that does not take and collapse at the top of the repair are all recognized as commoner than in people with normal bone (Baroudi 2024), which is why the limits for a spine with metal in it come from the surgeon who put it there rather than from a general exercise dose. None of that is a reason to skip strength work, which this group usually needs more than most, and none of it is something this page can replace the review appointments for.
One progression to be careful about, because it is the one the internet suggests next. Adding weight that hangs on your shoulders and trunk, in a weighted vest or a loaded backpack, is a different proposition from a weight in your hands, and nobody has tested a vest in people with established osteoporosis and a previous fracture. Weighted vests with osteoporosis sets out what the trials did and did not measure. Ask your physio before you put one on, and especially if you have had a fracture in your spine or your upper back has become more rounded. A vest you cannot put down mid-set is also the wrong place to start if you have had spinal surgery or cement into a vertebra, so that one goes to your surgical team.
Exercises that can help
Four starting points rather than a program, easiest first, and body weight before any weight. Sit to stand often starts at 2 to 3 sets of 5 to 10, once a day or on most days, with your physio setting the chair height and the numbers. The chair squat often starts at 2 to 3 sets of 8 to 12 at a seat height you can manage with control. The seated row with band often starts at 2 to 3 sets of 10 to 15 pulls, with a band light enough that you can stay upright throughout. Back extension on elbows often starts at 1 to 3 sets of 5 to 10 lifts, each held for about 5 seconds. What these build toward is the published dose on this page, a weight you can lift 8 to 12 times building up to 3 sets on 2 to 3 days a week, and not the 5 sets of 5 above 85 percent of a one repetition maximum from the supervised trial, which is not a starting point for anyone training alone. Where this paragraph and an exercise page differ, the exercise page wins. Your physio will adjust this.
The exercises below carry their own stop signs and precautions. Open the line under an exercise and read them before you try it.
 Sit to stand
Stop signs and precautions for the sit to stand
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try sit to stand. Standing up from a low seat bends the hip past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask them how high your seat should be. If you are pregnant, check with your midwife or physio before you start.
- Set up before the first stand: use a chair that will not slide, ideally with its back against a wall, and have someone nearby, or set the chair beside a kitchen counter you can reach, if you are not sure of your balance or you have fallen in the past year. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet.
When to stop and get help
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services.
- Sharp pain in the knee, hip or lower back.
- Your knee gives way or you feel you might fall.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
- You are pregnant and notice bleeding or fluid leaking from your vagina, regular painful tightenings, tummy pain that does not settle when you rest or comes with lower back pain, or a change in your baby's usual movements, such as moving less than usual. Stop and contact your midwife or maternity unit straight away. Do the same for a severe headache, problems with your vision such as blurring or flashing lights, pain just below your ribs, or sudden swelling of your face, hands or feet, which can be signs of pre-eclampsia. Call emergency services if the bleeding is heavy, the tummy pain is severe, bleeding or tummy pain comes with pain in your shoulder or feeling sick, faint or dizzy, or a headache comes on suddenly and is very severe.
 Chair squat
Stop signs and precautions for the chair squat
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- Knee pain on the way down is a sign to put a cushion back rather than push through it, and after knee surgery your physio will tell you how deep to go. If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try chair squats. A low seat makes the hip bend past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask them what seat height suits you.
- Osteoporosis, a recent fall or shaky balance are all reasons to keep a kitchen counter within reach for every rep, and to ask your physio before you take a cushion away.
When to stop and get help
- A sharp pain in your knees, hips or low back, or knee pain that builds rep by rep.
- A knee buckles, or you start to lose your balance.
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
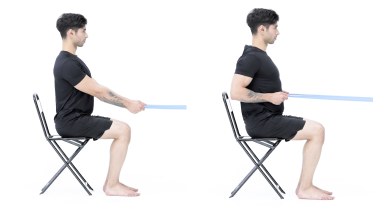 Seated row with band
Stop signs and precautions for the seated row with band
Before you start
- After shoulder surgery, rows with a band usually wait until later in rehab, so check with your surgeon or physio first.
- After heart or chest surgery, pulling against a band usually waits until your breastbone has had time to heal, so ask your surgeon or surgical team when to start: only the team that wired it can clear loaded pulling. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
- If you have high blood pressure, breathe steadily through every repetition and never hold your breath.
- Do not lean forward to reach the band or twist to one side as you pull, and if you have had a fracture in your spine, check with your physio before you start.
When to stop and get help
- A sharp pain or catching feeling in your shoulder as you pull.
- Pain, tingling or numbness spreading down an arm.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- A sudden pop or snap at the front of your elbow, sudden sharp pain there, or the muscle at the front of your upper arm bunches up or changes shape. Stop and go to an urgent care center or emergency department the same day, even if you can still bend the elbow, as this can be a torn biceps tendon.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Back extension on elbows
Stop signs and precautions for the back extension on elbows
Before you start
- After recent back surgery, follow your surgeon's plan. If you have had heart or chest surgery in the last few months, check with your surgeon or surgical team before lying face down and pushing up through your arms, as both put pressure on the healing breastbone, and only the team that wired it can say when it will take that. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
- If you have had a fracture in your spine, check with your physio before you begin.
- If you have been told you have narrowing of the spinal canal (spinal stenosis) or a forward-slipped vertebra (spondylolisthesis), ask your physio before you start, because bending backward often aggravates both.
- Lying face down is one to clear with your physio if you are pregnant.
- If you have high blood pressure, breathe steadily through every hold and never hold your breath.
When to stop and get help
- Pain spreads into your buttock or down a leg, or you get numbness or tingling in a leg.
- A sharp or pinching pain in your lower back that does not ease once you lie flat again.
- Neck pain during the lift, or pain, numbness or tingling spreading into an arm.
- Numbness around your genitals or bottom, new trouble with your bladder or bowels, pain, tingling, numbness or weakness in both legs, or loss of feeling in one leg. Call emergency services or go to an emergency department straight away, and do not drive yourself.
- Your leg or foot gets weaker, for example your foot drags, catches on the ground or slaps down when you walk (foot drop). Get medical advice the same day. If the weakness is getting worse by the hour, go to an emergency department.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
Three pages carry the rest of this. The osteoporosis program puts the whole thing into stages with videos. The best exercises for osteoporosis explains why strength is only one of three jobs, and exercises to avoid with osteoporosis sorts out which movement restrictions have a basis. If your real problem is age and weakness rather than bone, strength training for seniors over 70 and our guide to resistance training for older adults are written for that.
Related exercise programs
Warning signs
Get emergency help now
- Emergency: if chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
- Emergency: any sign of a stroke, even if it goes away. That means a face that droops on one side, an arm you cannot lift or keep up, slurred or muddled speech, weakness or numbness on one side of your body or face, sudden blurred vision, double vision or loss of sight, trouble swallowing, sudden dizziness with unsteadiness or falling over, a sudden severe headache, or a sudden fall where your legs give way but you do not black out (a drop attack). Call emergency services straight away.
- Emergency: a racing, pounding, fluttering or irregular heartbeat that does not settle when you rest, or that comes with dizziness, feeling faint or fainting, chest pain or shortness of breath. Call emergency services straight away. If it has already stopped, get medical advice the same day.
- Emergency: you have just fallen and cannot get up, or you think you may have hurt your head, neck, back or hip. Stay where you are, keep warm and call emergency services, or get someone to call for you. Nobody should try to lift you off the floor, and nobody should pull you up by the arms: being hauled upright can move a broken bone that has not slipped yet and can make an injured neck or back worse. Someone helping should call for help, keep you warm and stay with you. If you got up and walked without trouble and only notice pain later, without any of the emergency signs in this list, use the same-day lines in it instead.
- Emergency: you fell and cannot remember the fall or how it happened. Go to an emergency department straight away, and do not drive yourself. You may have blacked out or hit your head without knowing it.
- Emergency: you have had a fall or an injury and now have severe hip pain, or you cannot walk or put weight on the leg. Call emergency services or go to an emergency department. This can be a sign of a broken hip (hip fracture).
- Emergency: numbness, tingling or altered feeling around or under your genitals, between your inner thighs, or around your bottom (anus), for example it feels different when you wipe after using the toilet. Call emergency services or go to an emergency department straight away, and do not drive yourself. This can be a sign of pressure on the bundle of nerves at the base of the spine (cauda equina syndrome), which needs emergency treatment.
- Emergency: you find it hard to start peeing, cannot pee, cannot feel yourself peeing or cannot control when you pee, or you do not notice when you need to poo or cannot control when you poo, and this is not normal for you. The same applies to a new change in how your genitals feel during sex, new trouble getting or keeping an erection, new trouble ejaculating, or new trouble reaching orgasm. Call emergency services or go to an emergency department straight away, and do not drive yourself. These can also be signs of cauda equina syndrome.
- Emergency: sciatica in both legs, or pain, tingling, numbness or weakness in both legs. The same applies if you lose feeling in one leg. Call emergency services or go to an emergency department straight away, and do not drive yourself.
- Emergency: new problems walking, for example your legs feel stiff, heavy or weak or you have become unsteady on your feet, new trouble controlling your bladder or bowels, or new numbness or pins and needles in a band around your chest or tummy, or below it. Call emergency services or go to an emergency department straight away. These can be signs of pressure on the spinal cord in the upper back.
- Emergency: back or leg pain that started after a serious accident, such as a car crash or a fall from a height, or back pain with chest pain. Call emergency services. If the pain started straight after the accident, keep still while you wait.
- Emergency: sudden, severe pain in your lower back or tummy that is not like your usual back pain, if you have been told you have a swelling of the main blood vessel in your tummy (abdominal aortic aneurysm), you are over 60, you smoke or used to smoke, or you have high blood pressure. The same applies if sudden, severe back or tummy pain comes with feeling faint or passing out, pale, sweaty or clammy skin (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), a racing heartbeat or being short of breath. Call emergency services straight away. This can be a sign of an aneurysm bursting, which needs treatment in hospital at once.
- Emergency: new neck or back pain after a fall, a knock or a jolt, even a minor one such as a trip or a sudden stop in a car, if you have a condition that stiffens the spine, such as ankylosing spondylitis. Call emergency services or go to an emergency department straight away, do not drive yourself, and tell the staff about your spine condition, so they keep your neck and back in their usual position. A stiff spine can break after a small injury, and the break is easy to miss at first. If the pain started straight after the injury, or you also have numbness, tingling or weakness in your arms or legs, keep still and call emergency services.
- Emergency: back pain with a fever, or you feel hot, shivery or very unwell, and you also have new weakness, numbness or tingling in one or both legs, or new trouble with your bladder or bowels. Call emergency services or go to an emergency department straight away, and do not drive yourself. This can be an infection pressing on the nerves in the spine (spinal epidural abscess), which needs emergency treatment.
- Emergency: you have had cancer, now or in the past, and your back or neck pain feels like a tight band around your body, or you have new or worsening pain spreading down an arm or leg, weakness, numbness, pins and needles or a loss of feeling in your arms or legs, trouble walking, or trouble controlling your bladder or bowels. Those symptoms count on their own, with or without back or neck pain. Call your cancer team's emergency number straight away, or go to an emergency department if you do not have one or cannot get through, and do not drive yourself. This can be cancer pressing on the spinal cord (metastatic spinal cord compression), which needs treatment straight away.
Get help today
- Same day: back pain after a minor fall or strain if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time. Get medical advice the same day. Until it has been checked, stop the exercises and keep away from lifting, bending forward and twisting, because those load a bone in the spine that may be broken.
- Back pain that comes on suddenly after lifting, bending, a cough or a sneeze, even without a fall, if you have low bone density (osteoporosis). Get medical advice the same day. This can be a sign of a broken bone in the spine (vertebral fracture). Stop the exercises until you have been checked, and keep away from lifting, bending forward and twisting in the meantime, because those load a broken vertebra whether you are exercising or not.
- Severe pain that comes on suddenly or is getting worse quickly. Get medical advice the same day.
- Back or leg pain with a fever, or you feel hot, cold, shivery or generally unwell. Get medical advice the same day, and go to an emergency department if you feel very unwell. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: new hip or groin pain after a fall, even a small one, if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time, even if you can still walk. Get medical advice the same day, and say that you fell and that your bones are thin. Until it has been checked, stop the exercises and keep as much weight off that leg as you can, using your stick, frame or crutches if you have them and asking someone for help to move about, because a crack in the hip that has not slipped yet can slip when you walk on it, and a hip that has slipped usually needs a bigger operation than one that has not. A broken hip is not always obvious at first, and a first X-ray does not always show it, so if you have been checked and sent home and you still cannot walk on that leg, or the pain is getting worse, go back and say so.
- Same day: you have had a hip replacement, or a broken hip fixed with screws, a nail or a plate, and after a fall or a knock, even a small one, your hip, groin or thigh is newly painful, bruised or swollen, even if you can still walk and your leg looks normal. Stop the exercises and keep your full weight off that leg, using your stick, frame or crutches if you have them and asking someone for help to move about, then contact your surgical team or get medical advice the same day. A break in the bone around a new hip, or around metalwork left in the bone, is not always obvious at first, and walking normally on one can move the broken ends apart.
- A leg or foot that is getting weaker, for example your foot drags, catches on the ground or slaps down when you walk (foot drop). Get medical advice the same day. If the weakness is getting worse by the hour, go to an emergency department.
- Same day: a calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- You have back pain and have lost weight without trying. Get medical advice the same day and mention the weight loss.
- New back pain and you have had cancer, now or in the past. Get medical advice the same day and mention your cancer history. If you are being treated for cancer now, contact your cancer team the same day.
- Same day: you blacked out or fainted, even for a moment. Get medical advice the same day. Call emergency services instead if the person is not breathing, cannot be woken within 1 minute, has not fully recovered or has trouble speaking or moving, has chest pain or a pounding, fluttering or irregular heartbeat, fainted while exercising or lying down, is shaking or jerking, or was badly hurt.
- Same day: dizziness, lightheadedness, blurred vision or feeling faint when you stand up that is new for you, does not pass within a minute or two, keeps happening, or has made you fall. Sit or lie down, and get medical advice the same day. This can be a drop in blood pressure on standing (postural hypotension), a type of low blood pressure, which the NHS lists among the causes of falls, and your doctor can check it. Tell them about your medicines, because some can cause it. If it does not settle within a few minutes of sitting or lying still, call emergency services. If you faint, use the fainting line above.
- Same day: dizziness or feeling faint during or after exercise, other than the brief lightheadedness as you stand up covered in the line above, without any of the emergency signs above. Stop the exercises and get medical advice the same day. If you faint, it does not settle within a few minutes of sitting still, or you cannot stand or walk steadily, call emergency services.
- Same day: pain that is worse at night, or does not ease at all when you rest. If you have had cancer, now or in the past, or you have lost weight without trying, get medical advice the same day.
Book an appointment
- Within a few days: pain that is worse at night, or does not ease at all when you rest. See your doctor within a few days.
- Routine: you have lost height, or your upper back has become more rounded and you are starting to stoop, or you have back pain, or pain that wraps around to your ribs, with no clear cause. Book an appointment with your doctor. A broken bone in the spine can cause this, and it does not always cause the pain you would expect. If the pain came on suddenly, get medical advice the same day.
Common questions
Can you lift weights with osteoporosis?
For most people yes, and the guidance is more enthusiastic about it than the internet is. The UK consensus recommends progressive resistance training on 2 or 3 days a week at a weight you can lift 8 to 12 times, building toward 3 sets per exercise (Brooke-Wavell 2022). The statement marks that one E, meaning it came from the evidence the group reviewed, where its posture recommendations are marked C and the document itself describes them as consensus rather than evidence based. The systematic review of adverse events in this population concluded that people with osteoporosis or osteopenia can safely take part in structured exercise programs, at home or in supervised facilities (Kunutsor 2018). The two parts that need a person rather than a page are your starting load and your technique, and both are a single appointment's work.
How heavy should you lift with osteoporosis?
Heavy enough that 8 to 12 repetitions is genuinely hard, which means the number on the weight goes up as you get stronger. That is why the published dose is a proportion of your own strength and not a figure in pounds or kilos: the same 5 kg (11 lb) is a warm-up for one reader and a maximum for another. The consensus also says plainly that lower intensity exercise with good technique comes first, before intensity goes up. The Royal Osteoporosis Society puts the other half of it in one sentence: there is not a specific weight that is safe or unsafe.
Is weight training good for osteoporosis?
It is the part of the exercise advice that sits on the firmest ground. The UK consensus marks its two headline progressive resistance recommendations E, for the evidence it reviewed, where its impact and posture recommendations are marked C for expert consensus, and of the posture ones it says in its own words that they are consensus rather than evidence based. The Australian position statement says bone responds positively to impact activities and to high intensity progressive resistance training (Beck 2017). What it does for your bone density is modest, measured in single-figure percentages over months of training, which is why the consensus describes the effect of exercise on bone as much smaller than that of osteoporosis medicine. The strength itself is worth having for its own sake, because it is what gets you off a low chair and helps you catch a stumble.
Can you deadlift with osteoporosis?
The UK consensus names squats and deadlifts among acceptable compound exercises, so the lift is not forbidden, and the hip hinge that a deadlift is built on is the exact movement the bending advice asks you to use instead of rounding your back. That is not the same as saying go and pull a loaded bar off the floor this week. A deadlift is a technical lift, it loads the spine more than almost anything else in a gym, and the trials that reported no fractures were supervised sessions with trained staff. If you want to do it, get a physio or a coach who knows the condition to teach it and set the load, start absurdly light, and treat sudden back pain during or after a session as the same-day warning it is on this page. If you have had a fracture in your spine, that conversation comes before the lift, not after it.
Do I need supervision to do strength training with osteoporosis?
For the ordinary 8 to 12 repetition dose, no, as long as somebody has set your starting load and checked how you move. The national bodies lean further toward supervision than that answer does, and the difference is worth knowing. The UK consensus itself says resistance exercise is ideally supervised, to get the technique right and keep the injury risk down, with programs starting at lower loads until the technique is there (Brooke-Wavell 2022). Healthy Bones Australia goes further and says supervised exercise is recommended for people with diagnosed osteoporosis, and that adults with the diagnosis, including those who have recovered from a fracture, are encouraged to work with a physiotherapist or exercise physiologist. For the heavy protocols you will read about online, the supervision is not a detail of the trial, it is part of the result: the authors of the main trial attached their safety claim to highly supervised conditions in the conclusion itself (Watson 2018). The UK consensus recommends individual advice from a physiotherapist at the start of a new program for anyone with a vertebral fracture or several low-trauma fractures, and the Delphi panel recommends seeing a physical therapist where there is pain, more than one fracture or a marked rounding of the upper back (Giangregorio 2015). If that is you, the appointment is the first step rather than an optional extra.
References
- Brooke-Wavell K, Skelton DA, Barker KL, et al. Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022;56(15):837-846. https://doi.org/10.1136/bjsports-2021-104634
- Watson SL, Weeks BK, Weis LJ, et al. High-intensity resistance and impact training improves bone mineral density and physical function in postmenopausal women with osteopenia and osteoporosis: the LIFTMOR randomized controlled trial. Journal of Bone and Mineral Research. 2018;33(2):211-220. https://doi.org/10.1002/jbmr.3284
- Watson SL, Weeks BK, Weis LJ, et al. High-intensity exercise did not cause vertebral fractures and improves thoracic kyphosis in postmenopausal women with low to very low bone mass: the LIFTMOR trial. Osteoporosis International. 2019;30(5):957-964. https://doi.org/10.1007/s00198-018-04829-z
- Harding AT, Weeks BK, Lambert C, et al. A comparison of bone-targeted exercise strategies to reduce fracture risk in middle-aged and older men with osteopenia and osteoporosis: LIFTMOR-M semi-randomized controlled trial. Journal of Bone and Mineral Research. 2020;35(8):1404-1414. https://doi.org/10.1002/jbmr.4008
- Kunutsor SK, Leyland S, Skelton DA, et al. Adverse events and safety issues associated with physical activity and exercise for adults with osteoporosis and osteopenia: a systematic review of observational studies and an updated review of interventional studies. Journal of Frailty, Sarcopenia and Falls. 2018;3(4):155-178. https://doi.org/10.22540/JFSF-03-155
- Giangregorio LM, McGill S, Wark JD, et al. Too Fit To Fracture: outcomes of a Delphi consensus process on physical activity and exercise recommendations for adults with osteoporosis with or without vertebral fractures. Osteoporosis International. 2015;26(3):891-910. https://doi.org/10.1007/s00198-014-2881-4
- Giangregorio LM, Papaioannou A, MacIntyre NJ, et al. Too Fit To Fracture: exercise recommendations for individuals with osteoporosis or osteoporotic vertebral fracture. Osteoporosis International. 2014;25(3):821-835. https://doi.org/10.1007/s00198-013-2523-2
- Gibbs JC, MacIntyre NJ, Ponzano M, et al. Exercise for improving outcomes after osteoporotic vertebral fracture. Cochrane Database of Systematic Reviews. 2019;7(7):CD008618. https://doi.org/10.1002/14651858.CD008618.pub3
- Beck BR, Daly RM, Singh MA, Taaffe DR. Exercise and Sports Science Australia (ESSA) position statement on exercise prescription for the prevention and management of osteoporosis. Journal of Science and Medicine in Sport. 2017;20(5):438-445. https://doi.org/10.1016/j.jsams.2016.10.001
- Baroudi M, Daher M, Maheshwari K, et al. Surgical management of adult spinal deformity patients with osteoporosis. Journal of Clinical Medicine. 2024;13(23):7173. https://doi.org/10.3390/jcm13237173
- Royal Osteoporosis Society. How to exercise safely for bones. https://theros.org.uk/information-and-support/exercise/how-to-exercise-safely-for-bones/
- Royal Osteoporosis Society. Strength exercise to help make your bones stronger. https://theros.org.uk/information-and-support/exercise/exercise-for-bones/strength-exercise-to-help-make-your-bones-stronger/
- Royal Osteoporosis Society. Spinal fractures (vertebral fractures). https://theros.org.uk/information-and-support/living-with-osteoporosis-and-broken-bones/spinal-fractures-vertebral-fractures/
- Osteoporosis Canada. Too Fit To Fracture. https://osteoporosis.ca/too-fit-to-fracture/
- Healthy Bones Australia. Exercise and bone health. https://healthybonesaustralia.org.au/your-bone-health/exercise-bone-health/
- Bone Health and Osteoporosis Foundation. Exercise and safe movement. https://www.bonehealthandosteoporosis.org/patients/treatment/exercisesafe-movement/
- NHS. Osteoporosis. https://www.nhs.uk/conditions/osteoporosis/
- NHS. Back pain. https://www.nhs.uk/conditions/back-pain/
- NHS. Falls. https://www.nhs.uk/conditions/falls/
- NHS. Symptoms of a stroke. https://www.nhs.uk/conditions/stroke/symptoms/
- NHS. Heart attack. https://www.nhs.uk/conditions/heart-attack/
- NHS. Fainting. https://www.nhs.uk/symptoms/fainting/
- NHS. Low blood pressure (hypotension). Page last reviewed 11 July 2023. https://www.nhs.uk/conditions/low-blood-pressure-hypotension/
- NHS. Deep vein thrombosis (DVT). Page last reviewed 30 April 2026. https://www.nhs.uk/conditions/deep-vein-thrombosis-dvt/
- NHS. Sepsis. Page last reviewed 14 May 2026. https://www.nhs.uk/conditions/sepsis/
- NHS. Abdominal aortic aneurysm. https://www.nhs.uk/conditions/abdominal-aortic-aneurysm/
- Darouiche RO. Spinal epidural abscess. New England Journal of Medicine. 2006;355(19):2012-2020. https://doi.org/10.1056/NEJMra055111
- Cancer Research UK. Spinal cord compression. https://www.cancerresearchuk.org/about-cancer/coping/physically/spinal-cord-compression
Written and checked by the PocketPhysio editorial team. Last updated 2026-11-06.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.