
Part of Meniscus tear
Do I need surgery for a meniscus tear, or will physio do?
Warning signs, and when to get help
What do the trials comparing surgery and physio show?
This is one of the better studied questions in knee surgery, and the answer has been consistent for over a decade.
A Norwegian trial, OMEX, randomized 140 adults aged roughly 36 to 60 with a degenerative tear on the inner side of the knee to either 12 weeks of supervised exercise or keyhole surgery to trim the meniscus. Knee scores at 2 years were similar in both groups, and the exercise group had stronger thigh muscles at 3 months (Kise and colleagues, 2016). Ten years on, the two groups still looked alike, including what their X-rays showed (Berg and colleagues, 2025).
A Dutch trial, ESCAPE, randomized 321 people aged 45 to 70 with a tear that was not blocking the joint to early surgery or to 16 sessions of physical therapy over 8 weeks. Physical therapy was not worse than surgery for knee function over 2 years (van de Graaf and colleagues, 2018).
In the United States, METEOR randomized 351 people aged 45 or over who had a meniscal tear alongside mild to moderate knee arthritis on imaging. At 6 months the surgical group had improved by 20.9 points on the WOMAC physical function score and the physical therapy group by 18.5, a difference of 2.4 points that was not statistically significant (Katz and colleagues, 2013). A Swedish trial of 96 middle-aged people with a degenerative tear on the inner side found both groups improved and stayed improved, with no difference between them at 2 years or at 5 years, and concluded that surgery followed by exercise was not better than the same exercise alone (Herrlin and colleagues, 2013).
Pulling the trials together, a meta-analysis of 9 trials in middle-aged and older people with a degenerative knee found a small benefit in pain for the groups that had arthroscopy: 2.4 mm on a 0 to 100 mm pain scale with all the follow-up points combined, and 3 to 5 mm at 3 and 6 months, with nothing left by 1 to 2 years. Its authors called that benefit small and inconsequential. The same review counted the harms from a separate set of 9 studies, which included registries and case series as well as trials, and recorded symptomatic deep vein thrombosis at about 4 events per 1,000 procedures, along with pulmonary embolism, infection and death (Thorlund and colleagues, 2015). Those harm figures describe arthroscopy done to trim or clean up a worn knee in middle-aged and older people. They are not figures for a meniscal repair in a young knee, and they are not a full list of what can go wrong after knee surgery.
Who do those trials not apply to?
This is where most of the confusion comes from, because the guidelines are precise about it and the headlines are not.
The BMJ guideline panel that read this evidence made a strong recommendation against arthroscopic surgery in nearly all people with degenerative knee disease, whether or not the knee clicks or catches. It also said plainly who it had not studied: young people with sports injuries, and anyone of any age with a major knee injury. Its definition of degenerative knee disease leaves out a knee whose symptoms began after a major injury with the joint swelling up. The panel named one possible exception, a knee that truly cannot straighten (Siemieniuk and colleagues, 2017).
So if you are 24 and your knee went pop in a tackle on Saturday, none of the trials above is about you. The OMEX trial deliberately excluded acute injury, locked knees and ligament damage. Read a meniscus tear without an injury to work out which group your tear sits in.
When is surgery the better conversation?
A few situations push the discussion toward a surgeon rather than away from one.
A locked knee is the clearest of them. If the knee is stuck bent and will not fully straighten even when you relax it and try gently, a torn fragment may be caught in the joint. ESSKA recommends prompt repair of a bucket-handle tear that cannot be reduced (Kopf and colleagues, 2020), and this is the situation the BMJ panel left open. It is a same-day assessment, not a referral letter in a fortnight.
Next is a tear from a real injury in a younger knee. ESSKA puts keeping the meniscus first and says that when a repair is needed it should be done as early as possible, because early repairs appear to do better (Kopf and colleagues, 2020). Waiting to see if it settles can cost you the chance to repair it.
Then there is a degenerative tear that has not responded to good non-surgical care, and the two guideline groups differ here. ESSKA suggests surgery may be considered if pain or catching persists after about 3 months despite non-surgical care, and earlier for people with considerable catching or locking, while noting that catching and locking are hard to define (Beaufils and colleagues, 2017). The BMJ panel went further and advised against arthroscopy in nearly all cases, whether or not the knee catches (Siemieniuk and colleagues, 2017). Where two groups of experts disagree, a conversation with a knee surgeon is the honest next step.
Trim or repair, and why the difference matters so much
These are two different operations with two different recoveries, and people often arrive having been told only that they are "having the knee done".
A trim takes the torn piece out. Nothing has to heal afterward, so recovery is usually quick. The trade is that there is less meniscus left to spread the load, and ESSKA puts preservation first partly because both symptoms and X-rays tend to be worse in the long run after a trim than after a repair (Kopf and colleagues, 2020).
A repair stitches the torn edges and leaves them to knit, which takes months. For a while the stitches hold the tear while you walk on it, so the aftercare is stricter: surgeons limit weight bearing, how far the knee bends, and when you may squat, kneel or twist, and they lift those limits at different points. No society guideline sets those numbers, and they genuinely differ from surgeon to surgeon, so the instructions from your own operation are the ones that count. A repair can also come apart before the tear has healed, which is a failure a trim cannot have, and that is one of the reasons the limits exist. A trimmed meniscus can still tear again later, so neither operation is a guarantee.
Which of the two is even possible is decided by the tear, not by your age. The outer rim of the meniscus has a blood supply and can knit, the inner part has very little, and tissue that is already worn and frayed holds stitches poorly. That is why a 25 year old with a fresh tear in the outer rim is often a repair candidate while a 55 year old with a degenerative tear through the inner part usually is not, even though both are called a meniscus tear. ESSKA still puts keeping the meniscus first wherever that is possible, and reserves trimming an injury tear for cases where repair and leaving the tear alone are both unsuitable (Kopf and colleagues, 2020). A surgeon often cannot be sure which operation you need until they are looking at the tear, so it is worth asking what they will do if it turns out not to be repairable.
What does the physio option actually involve?
Not a pamphlet and three leg lifts. In OMEX the program ran 12 weeks with 24 to 36 supervised sessions of progressive strength and balance work, and in ESCAPE it was 16 sessions over 8 weeks (Kise and colleagues, 2016; van de Graaf and colleagues, 2018). That is the dose the results came from, and a trial of exercise that never got past the gentle stage has not really been tried. The meniscus tear program is built on the same pattern, with exercises to avoid with a meniscus tear covering what to turn down meanwhile.
Exercise does not settle every knee, and the trials are honest about that. In the Norwegian and Dutch trials, 19% and 29% of the people in the exercise groups went on to have surgery within the 2 years, and in METEOR 30% of the physical therapy group had surgery within 6 months (Katz and colleagues, 2013). Choosing physio first is not a door closing.
Questions worth taking to the surgeon
These are the ones patients tell me afterward they wish they had asked. They are a starting point rather than a checklist from a guideline.
- Is my tear the kind you would repair, or the kind you would trim, and why?
- What do you expect the operation to change for me, and what will it probably not change?
- What happens if I give the exercises another 3 months, and is there anything I could lose by waiting?
- How long are the weight bearing and bending limits afterward, and who do I ring if something changes?
- If the tear turns out not to be repairable once you are looking at it, what will you do instead, and how does that change my recovery?
- What are the main risks for someone like me?
Writing down the two or three things you most want to get back to doing keeps the conversation on your life rather than on the scan. If getting back to a sport is the point of it, return to sport after a meniscus tear covers what has to be true first, and if the knee is also arthritic, when to consider surgery for knee arthritis covers the other operations that come up.
Exercises that can help
These are the kind of exercises the trial programs were built from, and getting the thigh muscle working before an operation is something surgeons ask for too. They are not a program for after an operation: following a repair in particular, the limits your surgeon sets on weight bearing and on how far the knee bends rule several of these out in the early weeks, so if you have had surgery on this knee, work from the plan your surgeon and physio gave you instead of this list. Quad sets are often 10 repetitions with a 5 to 10 second hold, several times a day. Seated knee extension is often 2 to 3 sets of 10 to 15 on each leg with a short hold, once a day. The mini squat often starts at 2 to 3 sets of 10 to 15 once a day, and the step up at 2 to 3 sets of 8 to 12 on each leg, done next to a stair rail or a kitchen counter you can touch. Single leg stance often starts at 5 to 10 lifts on each leg, holding each for a few seconds, and both of those wait until your knee has been checked if it is catching, locking or giving way. Your physio will adjust this, and after an operation your surgeon's plan comes first.
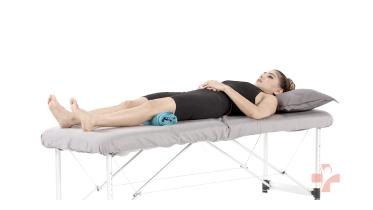 Quad sets (towel under knee)
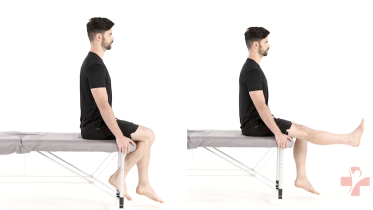 Seated knee extension
 Mini squat
 Step up
 Single leg stance
Check with your doctor before you start if you have a heart or lung condition, or blood pressure that is not under control.
If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, keep a hand on a kitchen counter throughout the single leg stance and for every step up, practice only when someone else is at home, and ask your doctor or physio about a falls check. If you live alone, that rule still stands, so plan around it rather than ignoring it. Do the single leg stance at your physio appointments or in a class instead, keep to the lying and seated exercises when you are on your own, and ask your physio which of the standing exercises you may do alone. Keep your phone in a pocket rather than in another room, so you can reach it from the floor, and ask about an alarm you wear.
If you do fall and cannot get up, or you think you may have hurt your head, neck, back or hip, stay where you are, keep warm and call emergency services, or get someone to call for you. Do not let anyone haul you up first.
If your knee is giving way, leave the single leg stance out until it has been checked, as the warning list below explains. If you have had a hip replacement, several of these exercises bend the hip past a right angle or put your weight on one leg, so get the go-ahead from your surgeon or physio first. If you are pregnant and past the first three months, check with your physio before exercising flat on your back, as the quad sets are done lying down. If you have high blood pressure, breathe steadily through every hold and never hold your breath.
If you have had any operation on this knee, follow the plan your surgeon and physio gave you rather than this list, because the limits after a repair on weight bearing, bending, squatting, kneeling and twisting are set by your own surgeon and are different from the ones here. If you no longer have them, ring the team who operated rather than working from a program written for a knee that has not been operated on, including this one. Until you reach them, stay with whatever you were last told you could do rather than moving on, keep using any crutches or brace you were given, and add nothing new from this page.
If the tear came from a twist, a fall or a tackle and nobody has assessed the knee yet, get that done before you start, because some of those tears are best repaired early. This page is for adults. A child or teenager with a knee injury should be assessed by a doctor or physio before starting any exercise program.
Related exercise programs
Warning signs
Get emergency help now
- Emergency: the knee has moved out of place, looks misshapen or is pointing at an odd angle, or you have tingling or no feeling in the knee, leg or toes, or your foot turns cold, pale or blue. Go to an emergency department straight away. Do not drive yourself: ask someone to drive you or call an ambulance.
- Emergency: the knee became very swollen very quickly, within a few hours of a twist, fall or blow, or you felt a pop or snap. Go to an emergency department straight away. Do not drive yourself: ask someone to drive you or call an ambulance. Swelling from a meniscus tear often builds up more slowly, over a few hours to 2 or 3 days, and a meniscus tear from sport often comes with other damage inside the knee, such as a torn ligament (the ACL), so fast swelling needs checking.
Get help today
- Same day: the knee is locked, which means it is stuck bent and you cannot fully straighten it, even after gently trying to move it, or you cannot bend or straighten the leg at all. Get assessed the same day by a doctor, at urgent care or at an emergency department. A torn piece of meniscus can get caught in the joint and block it, and when a tear like this can be repaired, it should be done as early as possible. A knee that catches for a moment and then frees itself can happen with a meniscus tear. That is not the same as a locked knee, but tell your physio or doctor about it.
- Same day: you felt the kneecap slip out of place and it went back by itself. Get assessed the same day.
- Same day: since an operation on your meniscus, the knee locks, catches or gives way again, or you feel a pop or a shift inside it, or it swells up or becomes much more painful after a twist, a kneel or a deep bend. Keep your weight off it and contact your surgical team, or get assessed the same day at urgent care or an emergency department. A repair can come apart before the tear has healed, and a trimmed meniscus can tear again. If the knee is only a little achy after a busy day, with no swelling and no catching, it is not an emergency, but tell your physio or surgeon in the next few days.
- Same day: the knee swells up with no clear reason, especially if you take medicine to thin your blood. Get medical advice the same day.
- Same day: you cannot walk or put weight on the leg, whether or not there was a fall or injury, or you have very bad knee pain after a fall or injury, or very bad knee pain that came on suddenly with no injury at all. Get medical advice the same day.
- Same day: the knee keeps giving way under you, or it gave way after a recent injury, or it gives way and is also very painful or swollen. Get medical advice the same day. If it only happens now and then, with no recent injury and no swelling, it is not an emergency, but book an assessment with a physio or doctor in the next few days. Until it has been checked, leave out the exercises you do standing on one leg, hold the rail on stairs and take care on uneven ground, because a knee that gives way without warning is how people fall.
- Same day: since your operation, your wound is oozing, leaking or has pus coming out of it, or its edges start to come apart, or your knee is tender, swollen, painful or red and it is not getting better or is getting worse, or you have a high temperature or feel hot and cold or shivery. Redness can be harder to see on brown or black skin. Contact your surgical team the same day, or get urgent medical advice if you cannot reach them. These can be signs of an infection in the wound or the knee joint. If you feel very unwell, go to an emergency department. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: the knee is hot, red and swollen, or you have knee pain with a high temperature or feel hot, cold or shivery. Get medical advice the same day, and go to an emergency department if you feel very unwell. This can be a sign of infection in the joint, which needs treatment quickly.
- Same day: a calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Same day: pain at night or at rest that keeps getting worse. If you are being treated for cancer now, contact your cancer team the same day.
Book an appointment
- Within a day or two: pain at night or at rest that keeps getting worse. If you have had cancer, now or in the past, see your doctor sooner, within a day or two, and mention it, even if the pain is not getting worse. Do the same if you have knee pain and are losing weight without trying, even if it does not hurt at night.
- Within a few days: pain at night or at rest that keeps getting worse. See your doctor within a few days.
Common questions
Do I need surgery for a torn meniscus?
Most middle-aged people with a degenerative tear do not need it at first. A BMJ guideline panel made a strong recommendation against keyhole surgery for nearly all people with degenerative knee disease, including degenerative tears (Siemieniuk and colleagues, 2017). The ESSKA consensus says trimming the meniscus should not be the first treatment (Beaufils and colleagues, 2017). Surgery is more likely to be discussed early for a locked knee, or for a younger person whose tear came from an injury and may be repairable (Kopf and colleagues, 2020).
Is physio as good as surgery for a meniscus tear?
For a degenerative tear in a knee that is not locked, the trials say the two end up in much the same place. The Norwegian trial found no difference in knee scores at 2 years and still no difference at 10 years (Kise and colleagues, 2016; Berg and colleagues, 2025). A Dutch trial found physical therapy was not worse than early surgery over 2 years (van de Graaf and colleagues, 2018). A US trial in people with a tear and knee arthritis found no significant difference at 6 months (Katz and colleagues, 2013). None of those trials included locked knees or fresh major injuries, so they do not answer the question for everybody.
How long should I try physio before thinking about surgery?
The ESSKA consensus says 3 to 6 months should pass from the day the symptoms started before surgery is offered for a degenerative tear in a knee that is not locked and not arthritic, and that the time is used for physiotherapy or home exercise, with anti-inflammatory medicine or an injection if needed (Beaufils and colleagues, 2017). That clock runs from when the pain began, not from the day you start the exercises. Give the program a proper run of 3 months or more before you judge it. For a younger person whose tear came from an injury, do not wait months: get it assessed early (Kopf and colleagues, 2020).
What are the risks of keyhole knee surgery?
They are small but they are real, which matters when the expected benefit is also small. Reviewing 9 studies of harms after arthroscopy on a degenerative knee, including registries and case series as well as trials, one meta-analysis recorded symptomatic deep vein thrombosis at about 4 events per 1,000 procedures, along with pulmonary embolism, infection and death (Thorlund and colleagues, 2015). Those numbers come from trimming and cleaning up a worn knee in middle-aged and older people, so they are not the risk figures for a young person having a tear repaired, and they are not a full list either: a repair can also fail before the tear has healed and need a second operation. Your surgeon will give you the figures that apply to you and to their own practice, which is the conversation to have rather than reading a number off a website.
Can physio fix a locked knee?
No, and it should not be the plan. A knee that is stuck bent and will not fully straighten can have a torn piece of meniscus caught in the joint, blocking it. The BMJ panel named a knee that truly cannot straighten as the one possible exception to its recommendation against arthroscopy (Siemieniuk and colleagues, 2017), and ESSKA recommends prompt repair of a bucket-handle tear that cannot be reduced (Kopf and colleagues, 2020). Get it assessed the same day, as the warning list below sets out. A knee that catches for a moment and then frees itself is not the same thing, but tell your physio or doctor about it. If you cannot tell which of the two you have, treat it as the same-day one.
References
- Kise NJ, Risberg MA, Stensrud S, Ranstam J, Engebretsen L, Roos EM. Exercise therapy versus arthroscopic partial meniscectomy for degenerative meniscal tear in middle aged patients: randomised controlled trial with two year follow-up. BMJ. 2016;354:i3740. https://doi.org/10.1136/bmj.i3740
- Berg B, Roos EM, Englund M, et al. Arthroscopic partial meniscectomy versus exercise therapy for degenerative meniscal tears: 10-year follow-up of the OMEX randomised controlled trial. British Journal of Sports Medicine. 2025;59(2):91-98. https://doi.org/10.1136/bjsports-2024-108644
- van de Graaf VA, Noorduyn JCA, Willigenburg NW, et al. Effect of early surgery vs physical therapy on knee function among patients with nonobstructive meniscal tears: the ESCAPE randomized clinical trial. JAMA. 2018;320(13):1328-1337. https://doi.org/10.1001/jama.2018.13308
- Katz JN, Brophy RH, Chaisson CE, et al. Surgery versus physical therapy for a meniscal tear and osteoarthritis. New England Journal of Medicine. 2013;368(18):1675-1684. https://doi.org/10.1056/NEJMoa1301408
- Herrlin SV, Wange PO, Lapidus G, Hallander M, Werner S, Weidenhielm L. Is arthroscopic surgery beneficial in treating non-traumatic, degenerative medial meniscal tears? A five year follow-up. Knee Surgery, Sports Traumatology, Arthroscopy. 2013;21(2):358-364. https://doi.org/10.1007/s00167-012-1960-3
- Thorlund JB, Juhl CB, Roos EM, Lohmander LS. Arthroscopic surgery for degenerative knee: systematic review and meta-analysis of benefits and harms. BMJ. 2015;350:h2747. https://doi.org/10.1136/bmj.h2747
- Siemieniuk RAC, Harris IA, Agoritsas T, et al. Arthroscopic surgery for degenerative knee arthritis and meniscal tears: a clinical practice guideline. BMJ. 2017;357:j1982. https://doi.org/10.1136/bmj.j1982
- Beaufils P, Becker R, Kopf S, et al. Surgical management of degenerative meniscus lesions: the 2016 ESSKA meniscus consensus. Knee Surgery, Sports Traumatology, Arthroscopy. 2017;25(2):335-346. https://doi.org/10.1007/s00167-016-4407-4
- Kopf S, Beaufils P, Hirschmann MT, et al. Management of traumatic meniscus tears: the 2019 ESSKA meniscus consensus. Knee Surgery, Sports Traumatology, Arthroscopy. 2020;28(4):1177-1194. https://doi.org/10.1007/s00167-020-05847-3
- American Academy of Orthopaedic Surgeons. Meniscus Tears. OrthoInfo. https://www.orthoinfo.org/en/diseases--conditions/meniscus-tears/
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-16.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.