
Knee osteoarthritis exercises and physiotherapy
Warning signs, and when to get help
What is knee osteoarthritis?
Osteoarthritis is the most common kind of arthritis. In the knee, the cartilage that lines the joint gets thinner and the bone underneath changes. The knee can feel stiff and sore, especially after rest or a long day on your feet.
An X-ray is only part of the picture. A review of the research found that X-ray changes and knee pain often do not match: some people with a lot of change on the scan have little pain, and some with mild changes hurt a lot (Bedson and Croft 2008). NICE advises that in people aged 45 or over whose joint pain comes on with activity, and who have either no morning stiffness at all or morning stiffness that clears inside 30 minutes, osteoarthritis can usually be diagnosed from the symptoms and an examination, without an X-ray.
Why does exercise help knee osteoarthritis?
Stronger thigh and hip muscles help support the knee, and regular movement eases stiffness. NICE in the UK and the international osteoarthritis society OARSI both recommend exercise as a core treatment.
The latest Cochrane review (Lawford 2024) found that exercise probably improves pain and physical function in the short term. But the average benefit in the trials was small, and the authors could not be sure it was big enough to make a clear difference. Sticking with it matters, so choose exercises you can keep up. That is why the program below starts gently.
What getting better usually looks like
Pain and stiffness do not fade evenly, and knowing the usual order saves a lot of worry. Morning stiffness and the first few minutes of walking tend to ease first. Stairs are usually last, and going down them is the slowest of all, because the thigh has to control your whole body weight while the knee bends. Plenty of people are walking comfortably on the flat for weeks while stairs are still the worst part of the day.
Two things turn up on most swollen knees. The thigh muscle becomes harder to switch on, so the leg feels weaker than the soreness alone would explain, and the knee stops going fully straight. That is why stage 1 starts with quad sets and short arc quads rather than squats. Both ask the thigh to work in the last part of straightening, which is the part a swollen knee gives up first, and terminal knee extension in stage 2 is the standing version of the same idea.
The compensation most people make without noticing is a quiet shift of weight onto the good leg. You stand on it while the kettle boils and lean over it to get out of a chair. Your step on the sore side gets a little shorter. None of that is wrong, and all of it keeps the sore leg weak. Watching yourself get up from one chair is usually enough to spot it.
How to use this program
Pick the stage that matches you today. If you are not sure, start at stage 1. Move up a stage when the current one feels easy and your knee settles well afterwards.
Each exercise page gives a typical starting dose. As a rough guide, many programs use 2 to 3 sets of 8 to 15 repetitions. The lying and sitting exercises can be done most days, while harder strength work such as squats and split squats is often done 2 to 3 days a week so the muscles can recover between sessions. Your physio will adjust the exercises and the numbers to suit you.
Breathe normally through every repetition rather than holding your breath, especially if you have high blood pressure. If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, keep a hand on a kitchen counter, a handrail or a sturdy chair back for the whole of the standing exercises, practice only when someone else is at home, and ask your doctor or physio about a falls check.
NICE also recommends general aerobic activity, and walking, cycling and swimming are common choices. If you carry extra weight, NICE advises that losing weight improves pain and function, and that any amount of weight loss is likely to help.
The exercise program
The exercises below carry their own stop signs and precautions. Open the line under an exercise and read them before you try it.
Stage 1: Get the muscles working
For painful or very stiff knees, and for anyone new to exercise. These are done lying or sitting, so the knee is not carrying body weight yet.
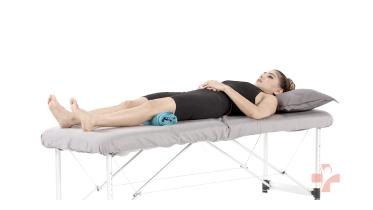 Quad sets (towel under knee)
Stop signs and precautions for the quad sets (towel under knee)
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
When to stop and get help
- Your knee pain goes up sharply.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
 Short arc quads
Stop signs and precautions for the short arc quads
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
When to stop and get help
- Knee pain increases sharply during the set.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Your wound becomes more red, hot, swollen or painful, or starts to leak. Contact your medical team the same day.
 Straight leg raise
Stop signs and precautions for the straight leg raise
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try this exercise. Some operations limit this kind of work for the first months, so the timing depends on your surgery. Lifting a straight leg is the heaviest way to use the muscles at the front of the hip, and after a periacetabular osteotomy a North American physiotherapy consensus panel asks for this exact movement, a straight leg lift while you are on your back, to be left out for 8 to 12 weeks.
- If you are pregnant and past the first three months, check with your physio before exercising flat on your back.
When to stop and get help
- Your lower back hurts.
- Knee pain increases during the set.
- You feel sharp pain in the front of the hip or groin.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Your wound becomes more red, hot, swollen or painful, or starts to leak. Contact your medical team the same day.
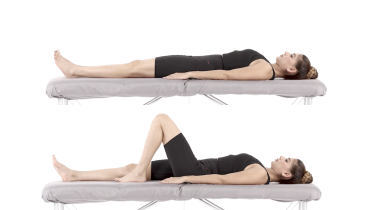 Heel slides
Stop signs and precautions for the heel slides
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try heel slides. Sliding the heel toward you bends the hip, and many surgeons set a limit on how far it can bend for the first months after some operations, so find out what yours is.
- If you are pregnant and past the first three months, check with your physio before exercising flat on your back.
When to stop and get help
- Pain in the knee or hip becomes sharp or keeps increasing with each rep.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Your wound becomes more red, hot, swollen or painful, or starts to leak. Contact your medical team the same day.
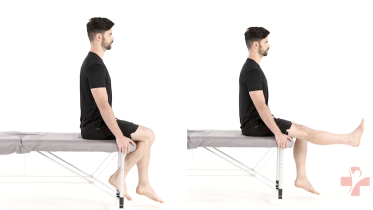 Seated knee extension
Stop signs and precautions for the seated knee extension
Before you start
- After knee ligament surgery, such as an ACL reconstruction, get the go-ahead from your surgeon or physio before you do this one. Many protocols limit how far the knee may straighten against resistance in sitting during the early stage.
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. Ask again before you add an ankle weight.
When to stop and get help
- You feel sharp pain at the front of the knee or under the kneecap.
- The knee swells up or is clearly more painful later that day or the next morning.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Glute bridge
Stop signs and precautions for the glute bridge
Before you start
- After hip, knee or back surgery, your surgeon's protocol decides when you can start bridges. Once you are past the first three months of pregnancy, check with your physio before exercising flat on your back.
- A bridge needs the knee bent to about 90 degrees before you lift, so if you have had knee surgery and been given a limit on how far the knee may bend, leave this one out and ask your surgeon or physio whether the bend it needs is allowed yet.
When to stop and get help
- You feel back pain rather than buttock work, even when you lift a little lower.
- Pain spreads down the leg or you get numbness or tingling.
- Your hamstrings (the back of the thighs) cramp. This is a common complaint with bridges, and bringing your feet a little closer to your bottom often eases it.
- Pain in the knee itself, or a knee that swells or is clearly more painful the next morning. The position holds the knee bent throughout, so after knee surgery stop and check with your surgeon or physio before you try it again.
Stage 2: Build strength standing up
When stage 1 feels easy, usually after one to three weeks. These train the knee in standing and work the side of the hip. If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, do the standing ones the way 'How to use this program' above sets out, with a hand on a kitchen counter throughout and someone else at home. For the squat, only go as deep as feels comfortable and controlled, and you can put a chair behind you to touch down on.
 Mini squat
Stop signs and precautions for the mini squat
Before you start
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try mini squats. Some operations limit this kind of work for the first months, so the timing depends on your surgery.
- After a knee replacement, including a partial one, or other knee surgery, get the go-ahead from your surgeon or physio and ask how deep you may go. A squat bends the knee and loads it at the same time, so if you have been given a limit on how far the knee may bend, this is the exercise it applies to first. Keep it shallow and controlled until they say otherwise.
When to stop and get help
- Knee pain is sharp or keeps getting worse through the set.
- The knee swells, gives way or feels unstable afterwards.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You feel unsteady enough that you might fall. Hold on to something firm and sit down.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
 Squat
Stop signs and precautions for the squat
Before you start
- If you have had a hip or knee replacement, get the go-ahead from your surgeon or physio before you try squats. A deeper squat bends the hip well past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask them how deep you may go.
When to stop and get help
- Sharp pain in the knee, hip or lower back, or pain that keeps building through the set.
- The knee gives way, locks or catches.
- The knee swells after the session.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Terminal knee extension with band
Stop signs and precautions for the terminal knee extension with band
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
When to stop and get help
- Pain at the front of the knee or behind the kneecap that builds during the set.
- The knee gives way, locks or catches.
- The knee is more swollen after the session than before it.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
 Clamshell
Stop signs and precautions for the clamshell
Before you start
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try clamshells. Opening the knee turns the thigh outward, and many surgeons ask you to avoid that for the first months after some operations. Lying on your side may also be limited in that time.
When to stop and get help
- You feel sharp or pinching pain in the hip or groin.
- Pain spreads into the leg, or you notice numbness or tingling.
- Pain on the outside of your hip builds during the set or is worse the next morning.
Stage 3: Stairs and single-leg strength
When stage 2 feels easy and the knee settles well afterwards. Step ups practice stairs, and the split squat loads one leg at a time. Side lying hip abduction is a harder version of the clamshell. Balance and control work (neuromuscular exercise) is part of programs such as GLA:D, and your physio can add balance exercises that suit you, such as standing on one leg while holding a counter.
 Step up
Stop signs and precautions for the step up
Before you start
- If you have had a hip or knee replacement, or other hip or knee surgery, get the go-ahead from your surgeon or physio before you try step ups. Some operations limit this kind of work for the first months, so the timing depends on your surgery. Your surgeon or physio will also tell you what step height is right for you.
- With a heart condition or high blood pressure, check with your doctor before you start.
- If you have fallen in the past year, have osteoporosis or feel unsteady on your feet, set the step beside a handrail, a kitchen counter or a sturdy chair back, keep one hand on it for every repetition, and ask your physio whether to start with step ups at all or to build up on a single stair first.
When to stop and get help
- You feel sharp pain in the knee or the knee gives way.
- Pain at the front of the knee builds with each rep.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You feel unsteady enough that you might fall. Stop and sit down.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Split squat
Stop signs and precautions for the split squat
Before you start
- If you have had a hip or knee replacement, or other hip or knee surgery, get the go-ahead from your surgeon or physio before you try split squats. Some operations limit this kind of work for the first months, so the timing depends on your surgery.
- If you are pregnant, check with your midwife or physio before you start.
- With a heart condition or high blood pressure, check with your doctor before you start.
- If you have fallen in the past year, have osteoporosis or feel unsteady on your feet, set up beside a kitchen counter, a handrail or a sturdy chair back, keep one hand on it for every repetition, and ask your physio whether to start with split squats at all or to build up with both feet side by side first.
When to stop and get help
- You feel sharp pain in the knee, hip or groin, or the knee gives way.
- Knee pain builds with each rep, or is clearly worse the next morning.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Side lying hip abduction
Stop signs and precautions for the side lying hip abduction
Before you start
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try side-lying hip abduction. Some operations limit this kind of work for the first months, so the timing depends on your surgery. With some surgical approaches, side leg lifts wait until the tissues at the side of the hip have healed.
When to stop and get help
- You feel sharp pain in the side of the hip, the groin or the lower back.
- Pain spreads down the leg or you get numbness or tingling.
Stairs, chairs and the first minutes of the day
While the knee is sore, the usual advice on stairs is to lead with your stronger leg going up, and to put the sore leg down first coming down so the stronger leg does the lowering. Hold the rail and take one step at a time. Treat it as a short-term aid rather than a habit. Step ups and the split squat are in stage 3 so that you can get back to taking stairs normally.
Chair height decides whether half of this program is possible. A dining chair is easier than a sofa, and a firm cushion on top raises it further, which is often the difference between a set you can do and one you cannot. Start at the height you can manage without hauling on your hands, then lower it over the weeks. Sit to stand and the chair squat are built on the same idea.
The stiffest part of the day is the first few minutes of it. Quad sets and a few heel slides in bed, before your feet reach the floor, take about two minutes and make the first walk of the morning easier. Two setup details from our own exercise pages: the band for terminal knee extension sits just above the crease at the back of the knee or it slides down, and a rolled towel instead of a foam roller makes short arc quads easier because the knee starts less bent.
If kneeling is part of your work or your garden, the trouble is usually how long you stay down rather than kneeling itself. A thick pad and getting up every few minutes beats one long spell on a hard floor.
What to avoid or change
You do not need to avoid movement, but you may need to change how much you do. Long spells of kneeling, deep squats with heavy weights and sudden jumps in walking distance can flare the knee. Build up in small steps instead.
When to see a physio or doctor
See a physio or doctor if your knee is not improving after 6 to 8 weeks of regular exercise, if pain is stopping you sleeping or doing daily tasks, or if the knee keeps giving way. It is also worth getting help at the start if you are not sure which stage suits you. Mention it as well if the knee comes with a stiff hip, groin pain or trouble reaching your foot to put a sock on, because hip arthritis can show up as knee pain and that changes which joint needs looking at.
Check with your doctor before you start if you have a heart or lung condition, or blood pressure that is not under control. After a knee replacement or other knee surgery, follow the program from your surgical team and physio instead of this one. If you have had a hip replacement or other hip surgery, several of these exercises bend the hip past a right angle or take the leg out to the side, so get the go-ahead from your surgeon or physio first.
For physiotherapists
This page gives patients a starting framework. Most people with knee osteoarthritis do better with a program adjusted to their pain and strength and to what they want to get back to doing. A patient-reported measure such as the KOOS, alongside a performance test from the OARSI recommended set such as the 30-second chair stand test (Dobson 2013), helps show progress over the first 6 to 12 weeks.
Questions about knee osteoarthritis
- Best exercise equipment for knee arthritis: what you actually need
- Cycling and swimming for knee arthritis: how to set up and build up
- Exercises to avoid with knee arthritis: what to change instead
- Is walking good for knee arthritis? How far to go and how to build up
- Knee arthritis flare up: what to do, how long it lasts and when to worry
- Knee brace for arthritis: does it help, and which type?
- Weight loss and knee arthritis: how much helps and how to start
- Surgery for knee arthritis: when to consider it and which kind
Warning signs
Get emergency help now
- Your foot became weak or numb at the moment of the knee injury or in the hours after it, for example your foot drags, catches on the ground or slaps down when you walk (foot drop), you cannot pull your foot or toes upward, or the top of your foot has lost feeling. Go to an emergency department straight away. Do not drive yourself: ask someone to drive you or call an ambulance. The nerve that lifts the foot wraps round the bone on the outer side of the knee, and the same force that injures the knee can stretch it. A foot that has been weak or numb from that moment goes with the more severe injuries, where more than one ligament has been torn or the whole knee has been out of place, and in those the artery behind the knee has to be checked on the day. So this one is not watched at home to see whether it gets worse.
Get help today
- The knee is hot, red and swollen, or you have knee pain with a high temperature or feel hot, cold or shivery. Get medical advice the same day, and go to an emergency department if you feel very unwell. This can be a sign of infection in the joint, which needs treatment quickly.
- You cannot walk or put weight on the leg, whether or not there was a fall or injury, or you have very bad knee pain after a fall or injury, or very bad knee pain that came on suddenly with no injury at all. Get medical advice the same day. If the knee has changed shape, swelled up very quickly or you felt a pop or snap, or your foot turns cold, pale or blue or you have tingling or no feeling in the leg or foot, go to an emergency department straight away, and do not drive yourself.
- The knee locks and you cannot straighten it, or it keeps giving way under you. Get medical advice the same day. Until it has been checked, leave out the exercises you do standing on one leg, hold the rail on stairs and take care on uneven ground, because a knee that gives way without warning is how people fall.
- The knee swells up with no clear reason, especially if you take medicine to thin your blood. Get medical advice the same day.
- A calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- A leg or foot that is getting weaker, for example your foot drags, catches on the ground or slaps down when you walk (foot drop). Get medical advice the same day. If the weakness is getting worse by the hour, go to an emergency department. If the weakness started at the moment of your knee injury or in the hours after it, the emergency department line above applies instead.
- Pain at night or at rest that keeps getting worse. If you are being treated for cancer now, contact your cancer team the same day.
Book an appointment
- Pain at night or at rest that keeps getting worse. If you have had cancer, now or in the past, see your doctor sooner, within a day or two, and mention it, even if the pain is not getting worse. Do the same if you have knee pain and are losing weight without trying, even if it does not hurt at night.
- Pain at night or at rest that keeps getting worse. See your doctor within a few days.
Common questions
Is it safe to exercise with knee osteoarthritis?
For most people, yes. NICE and OARSI both recommend exercise as a core treatment. A review of trials found that exercise that loads the knee does not appear to harm the joint cartilage, although the evidence is still limited (Bricca 2019). Start at a level you can manage and build up slowly.
Should exercises hurt?
A little discomfort is common and is usually fine if it settles by the next morning and is not building up from week to week. Sharp pain, or a knee that is more painful or swollen the next day, means the load was too much. Your physio will help you set a limit. One kind of swelling is not an overdone session: a knee that is hot to touch, or swollen along with a temperature or feeling unwell, needs medical advice the same day, as the warning signs on this page say, because an infection in a joint feels much the same from the inside as too much exercise.
How long before exercise helps?
Give it several weeks. The GLA:D program, for example, runs twice a week for 6 weeks, and people in it reported less pain on average at their 3-month check (Skou and Roos 2017). Strength builds slowly, so doing a little regularly matters more than doing a lot at once.
Do I need equipment?
Very little. Most of these exercises need only a chair, a towel and a step or the bottom stair. Terminal knee extension uses a resistance band.
Is walking good for knee arthritis?
For most people, yes, in the amounts your knee settles from. NICE recommends general aerobic activity alongside strength work, and walking is the simplest way to get it. If one long walk leaves the knee sore for a day or two, split the same distance into shorter walks through the day and add to it slowly.
What exercises should I avoid with knee osteoarthritis?
The answer is in how your own knee responds over the next day, not in a list of banned movements. The usual culprits are deep squats under heavy weight and long spells of kneeling. A sudden jump in how far you walk does it too. If something leaves the knee more painful or more swollen the next morning, do less of it next time rather than dropping it for good.
Are cycling and swimming good for knee osteoarthritis?
Both are common choices, and they are useful while standing exercise is still too sore. They put less weight through the knee than walking, so you can often do more minutes for the same next-day soreness. Set a bike saddle high enough that the knee does not bend sharply at the top of the pedal stroke. Neither replaces strength work, so keep the program going alongside.
Do knee braces help?
They are not a first step. NICE advises against routinely offering insoles, braces, tape, splints or supports for osteoarthritis unless the joint is unstable or being loaded abnormally, exercise is not working or is not suitable without one, and the aid is likely to improve your movement and function. NICE does suggest considering a walking aid such as a stick for people with osteoarthritis in a leg joint, which includes the knee, and a physio can set its height and show you how to use it.
Does losing weight help knee arthritis?
It does if you are carrying extra weight. NICE advises that losing weight improves pain and function, and that any amount of weight loss is likely to help, which is worth knowing if a big target feels out of reach. The two sides work together in practice: getting stronger lets you move more, and weighing less makes the strength work easier.
What should I do when my knee flares up?
Reduce the amount rather than stopping. Drop back a stage for a few days, keep the lying and sitting exercises going so the thigh does not switch off, and cut walking back to a distance that leaves the knee no worse the next morning. Most flares settle over days, and then you build up again in small steps. A flare that does not follow that pattern, or that comes with any of the warning signs on this page, needs checking rather than managing at home.
When should I consider a knee replacement?
It is a conversation rather than a line you cross. NICE advises that joint replacement is worth discussing when your symptoms have a big effect on your quality of life and treatment without surgery, such as exercise, weight loss and pain relief, has not worked or is not suitable. NICE is also clear that age, sex, smoking, other health conditions and being overweight should not be used to keep you from being referred. Getting as strong as you can beforehand is useful either way.
References
- National Institute for Health and Care Excellence. Osteoarthritis in over 16s: diagnosis and management (NG226). 2022. https://www.nice.org.uk/guidance/ng226
- Bannuru RR, Osani MC, Vaysbrot EE, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage. 2019;27(11):1578-1589. doi:10.1016/j.joca.2019.06.011
- Lawford BJ, Hall M, Hinman RS, et al. Exercise for osteoarthritis of the knee. Cochrane Database of Systematic Reviews. 2024;(12):CD004376. doi:10.1002/14651858.CD004376.pub4
- Skou ST, Roos EM. Good Life with osteoArthritis in Denmark (GLA:D): evidence-based education and supervised neuromuscular exercise delivered by certified physiotherapists nationwide. BMC Musculoskeletal Disorders. 2017;18:72. doi:10.1186/s12891-017-1439-y
- Bricca A, Juhl CB, Steultjens M, Wirth W, Roos EM. Impact of exercise on articular cartilage in people at risk of, or with established, knee osteoarthritis: a systematic review of randomised controlled trials. British Journal of Sports Medicine. 2019;53(15):940-947. doi:10.1136/bjsports-2017-098661
- Bedson J, Croft PR. The discordance between clinical and radiographic knee osteoarthritis: a systematic search and summary of the literature. BMC Musculoskeletal Disorders. 2008;9:116. doi:10.1186/1471-2474-9-116
- Dobson F, Hinman RS, Roos EM, et al. OARSI recommended performance-based tests to assess physical function in people diagnosed with hip or knee osteoarthritis. Osteoarthritis and Cartilage. 2013;21(8):1042-1052. doi:10.1016/j.joca.2013.05.002
Written and checked by the PocketPhysio editorial team. Last updated 2026-11-02.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.