
Post intensive care syndrome: recovering after intensive care
Warning signs, and when to get help
How long does it take to recover after intensive care?
Months, and for a fair number of people more than a year. The NHS says many people who leave an intensive care unit go on to recover well, and in the same breath lists what can hang about: weakness and stiffness, extreme tiredness and no energy, a lost appetite and lost weight, broken sleep, depression, anxiety or post-traumatic stress, and trouble thinking clearly or remembering things. It puts the timescale at several months and says to get medical advice if any of it is persistent. Post intensive care syndrome is the name that pattern goes under.
The far end of the range has been measured properly in one group. Herridge and colleagues (2011) followed 109 people who survived acute respiratory distress syndrome, a severe lung injury, at 3, 6 and 12 months and then once a year out to five years after they left intensive care. At five years the median distance they covered in a six minute walk was 436 meters, 76 percent of what would be predicted for them, and their physical quality of life score averaged 41 where the matched population average is 50. Younger patients came back faster than older ones, and neither group reached predicted normal by five years.
Read that cohort for what it was. These were survivors of one severe lung condition, and they are not a forecast for somebody who spent two nights in intensive care after an operation. What the study is good for is the shape of the thing: improvement still going on years later, and a tail that does not fully close.
The first signs of progress are nearly always in what you can do rather than in what you can lift. Getting off the toilet without hauling on something. Washing your own hair. Staying awake through a whole visit instead of sleeping through the second half of it.
One flat week is ordinary and tells you nothing. A month with nothing moving, or ground actually lost, is information, and it belongs with the review further down this page rather than with another month of patience.
Why you are this weak: ICU-acquired weakness is not the same as being out of condition
A week lying on a general ward costs you fitness. A critical illness can go further than that and damage the nerves and the muscle themselves, which is why this weakness behaves differently and why the word deconditioning does not cover it.
Critical illness polyneuropathy affects the nerves running out to the muscles, and critical illness myopathy affects the muscle itself; together they are usually called ICU-acquired weakness. In the unit they announce themselves as weakness and as difficulty getting off the ventilator. The changes described in the tissue are degeneration of nerve fibers, loss of myosin, which is the protein a muscle uses to pull, and death of muscle cells, and the diagnosis rests on clinical examination, electrical testing of nerve and muscle, and sometimes a muscle biopsy (Latronico and Bolton, 2011). Not all of it is damage to the structure: the same paper describes functional changes too, nerves and muscle that stop carrying the electrical signal properly for a while, with muscle weakness that reverses, so not all of this weakness is permanent.
The same paper is blunt about what follows. These problems lengthen time on the ventilator and time in hospital, raise the risk of dying in hospital, and leave lasting disability in people who survive. On the other side of the ledger, the authors suggest that rehabilitation started early, in the unit itself, might improve how well people function and how independent they are afterward, and might is their word rather than ours.
This page gives you no figure for how common it is, and that is deliberate. The percentages in circulation come from studies that defined the problem differently in different groups of patients, and we could not trace any of them back to a single piece of work we had read, so we are not passing one on. What you lose by not having a number is nothing you could act on.
What all that means in practice comes in two halves, pointing in opposite directions. Strength returning from nerve and muscle damage returns slowly, so slow is expected and is not evidence you are doing the program wrong. The other half is the next section: weakness that is getting worse rather than better is not this, and it is not something to train through. If you were on a general ward rather than in intensive care and want the ordinary loss of condition explained, recovering strength after a hospital stay is that page.
What is post intensive care syndrome, and what does it not mean?
It is an umbrella term. A group of stakeholders from the organizations that look after intensive care survivors agreed it at a Society of Critical Care Medicine conference, as a way of naming new or worsening problems in physical, cognitive or mental health that arise after a critical illness and carry on past the hospital stay (Needham and colleagues, 2012). A later review of the field is blunter still: post intensive care syndrome is not a medical diagnosis but a concept for raising awareness of what happens after intensive care (Hiser and colleagues, 2023). Nobody is going to hand you a test result for it.
How common the pattern is has been measured, and the way it was measured matters. A Dutch study put the same set of questions to 2,345 people twice, once about their health before intensive care and once a year afterward. New physical, mental health or thinking problems at the one year mark were reported by 58 percent of those admitted for a medical reason, 64 percent of those admitted after urgent surgery and 43 percent of those admitted after a planned operation (Geense and colleagues, 2021).
How that first set of answers was collected differs between those groups, and it is worth knowing: people coming in for a planned operation filled the questionnaire in before admission, while those admitted as an emergency, or their relatives, were asked afterward to describe how they had been (Hiser and colleagues, 2023). A remembered baseline is not a measured one. The same review points out that the physical side was measured with a questionnaire that had never been validated, so read these figures as a sign that the problem is common. They are not a precise rate.
Now the half that matters more, because it is the half that gets people into trouble. An umbrella that covers weakness, tiredness, breathlessness, poor memory and low mood will cheerfully absorb a blood clot, a chest infection, a low blood count or a stroke, because every one of those arrives as weakness and tiredness too.
The label is not an explanation for a new symptom, and it is not a diagnosis you can give yourself. It is also not a measure of how hard you are trying, which is worth saying plainly to anybody who has been told to stay positive.
The weakness that needs a doctor today, not exercise
The particular trap on this page is that you have a license. You were in intensive care, so being weak and exhausted is explained in advance, and an explanation that good will swallow almost anything.
Two things separate loss of strength from a symptom: the direction it is traveling in, and what it has brought with it. Weakness left by a critical illness eases slowly, and eases a little further on a day you have eaten and slept. Weakness that is worse this week than last week, or that turned up over an afternoon, or that arrived alongside something new, is a symptom and goes to a doctor before it goes into a program.
Three patterns on this page are not ever filed under recovery. Anything on one side only, meaning an arm or leg that has gone weak or numb down one side, a face that droops, or speech that slurs, means calling emergency services even if it has already passed off. A foot that drags, catches on the ground or slaps down when you walk needs medical advice the same day. And sudden confusion is an emergency at home, while the quiet version of the same thing, somebody going withdrawn, slow to answer and off their food over hours or days, needs advice the same day; both lines are in the warning list at the foot of this page with what to do.
Never stop or change a prescribed medicine on your own. If you have become weak, dizzy or muddled since you came home, the list you came home with is worth going through with your doctor or pharmacist, and that is a conversation, not a decision you make at the kitchen table.
The fuller list of treatable things that get mistaken for loss of condition, the clot, the infection, the low blood count, the new medicine, the blood pressure that drops when you stand, the fluid the heart is not keeping up with, is written out on the hospital stay page, and each of them has its own line in the warning list below. The medicines are the exception, because there is no single symptom to watch for: they are a conversation with your doctor or pharmacist rather than a warning sign. If your admission included an operation, the signs that a repair or a new joint has given way are on that page too, and they are worth reading, because from the inside they look exactly like a bad week. The wound, breastbone, scar and tube signs that belong to somebody just home from critical care are in the warning list at the foot of this page.
Swallowing, voice and breathing after a breathing tube
A breathing tube passes between the vocal cords, and weeks of not swallowing and not speaking sit on top of that. NICE's own pre-discharge assessment list for people who have been critically ill names trouble swallowing and difficulty speaking among the physical problems to look for, so this is expected territory rather than an odd thing to bring up.
We give you no figure for how long a changed voice or a changed swallow lasts, because we have no source we have read that gives one for this group. What there is instead is a route, and it is a fast one. Coughing or choking on food or drink, food that sticks in your throat or chest, food or drink that comes back up, a voice that sounds wet or gurgly after you swallow, or being short of breath after eating or drinking all go to somebody today rather than into a plan you work out for yourself at home, and it is worth asking whether your swallowing should be assessed by a speech and language therapist. The same day line is in the warning list below with the two faster routes inside it: swallowing that goes wrong suddenly belongs with the stroke line and emergency services, and anybody choking who cannot cough, speak or breathe needs emergency services now. Cutting food smaller, eating alone so nobody sees it, and quietly giving up on drinks all hide the problem instead of fixing it.
A tracheostomy changes the picture a little, because that tube breathes below the voice box rather than through it. If you came home with one, or with a healing hole in your neck where one was, the NHS asks you to get urgent advice if your breathing turns noisy by day or at night, including snoring that is new, if your voice stays hoarse or weak for more than a week, if swallowing is a problem, if you cough or are sick after eating or drinking, or if the area is painful, raised or uncomfortable. That list is less mild than it sounds. The windpipe can narrow where a tube and its cuff sat, and what that looks like from the outside is breathing that gets noisier and harder rather than easier, which on this page of all pages is the thing most likely to be put down to lack of fitness. It belongs with the surgical or ear, nose and throat team rather than with a training plan.
Any bleeding from a tracheostomy, or from the hole where one was, needs emergency services, and so does any difficulty breathing. Both have their own lines in the warning list below.
After an operation in the chest or the neck, a hoarse, weak or breathy voice can also mean a nerve to the voice box was bruised on the way past, and that matters beyond the sound of it, because the same nerve helps close the airway when you swallow. So raise the voice and the swallowing together, in the same conversation.
Breathlessness is the other one that follows a breathing tube around, and there is a useful detail in the five year study. Lung function testing in those survivors came back normal to near normal, and they still walked only 76 percent of their predicted distance in six minutes (Herridge and colleagues, 2011). So the limit on what they could do was not simply a lung limit, which cuts both ways for a reader: being breathless on effort does not mean your lungs are ruined, and it does not mean you are merely unfit either.
New breathlessness, or breathlessness that is getting worse, is a different question from breathlessness that is slowly improving. The warning list below gives it several routes. The emergencies on it are a clot in the lungs, severe difficulty breathing where you are gasping or cannot get your words out or your lips or skin turn very pale, blue or gray, and breathlessness with pain spreading to your arm, neck, jaw, back or stomach even when your chest itself does not hurt. None of them is a reason to push harder. For breathing technique alongside the strength work, breathing exercises for long-term chest conditions covers what to practice, and cardiac rehab covers the same ground after a heart problem.
Memory, mood and the nights
This is not the soft part of the page. NICE puts the physical and the non-physical into the same assessment, done at the same time by the same service, which tells you how it is meant to be treated.
The NHS names sleep problems, depression, anxiety and post-traumatic stress, along with trouble thinking clearly and being forgetful, among the things that can last several months after intensive care. NICE's own list of non-physical problems goes further into the specifics: a pounding heart, irritability and sweating; feeling detached from yourself or from what is around you; avoiding reminders; tearfulness and pulling away from people; nightmares, delusions, hallucinations and flashbacks; losing memories, losing the thread, finding it hard to put things in order or organize anything, confusion, apathy, saying things you would not have said, and not seeing any of it in yourself; low self-esteem, a changed sense of your own body, and trouble in your closest relationships.
Four of those are worth knowing by name, because NICE treats them as markers that someone needs rehabilitation rather than as ordinary distress. Nightmares that keep coming back, especially when the person has started trying to stay awake to avoid them. Memories of what happened that push their way in uninvited. New anxiety or panic attacks that keep happening. And not wanting to talk about the illness, or changing the subject fast when it comes up.
When somebody asks how you are getting on, the legs get reported, because the legs are the acceptable answer. The memory, the nights and the mood get left out, and what is left out does not get a plan.
So say it anyway, in the same appointment, in the same sentence as the stairs. This page offers no treatment for any of it, because that belongs to whoever assesses you. What it can tell you is that it is part of a recognized pattern, that it is not a sign of weak character, and that the route for it is the route you already have.
One part of this does not wait for an appointment. Thoughts of suicide, or of harming yourself, have their own line in the warning list below, and they need help the same day even if you have no plan to act on them.
Who gets rehabilitation, when it starts, and what the review should be
In the UK there is a written answer to this, which is useful even where you live somewhere else, because it tells you what to ask for. NICE clinical guideline CG83 covers rehabilitation after critical illness in adults, and the quality standard QS158 sets out what a service is expected to deliver. CG83 was published in 2009 and written for England, so it is both old and local, and that is worth holding in mind.
It starts in the unit. CG83 asks for a short clinical assessment during the critical care stay, as early as is clinically possible, to work out who is at risk of physical and non-physical problems afterward. For somebody in that at-risk group, rehabilitation is meant to begin as early as is clinically possible, and NICE describes it as including a look through past and current medicines, support with nutrition, and an individual structured rehabilitation program with frequent reviews.
The at-risk list is how you find out whether any of this was written about you. On the physical side NICE names being unable to get out of bed without help; a critical care stay expected to be long; an obvious significant physical or neurological injury; not being able to think well enough to carry on exercising independently; not being able to breathe for yourself on 35 percent oxygen or less; breathing or mobility problems that were already there beforehand; and not being able to walk independently even a short distance. On the non-physical side it names the four markers in the section above.
Three things are meant to be handed to you, and they are the three most often missing. The contact details of the professional coordinating your rehabilitation, given once when you leave critical care and again when you leave hospital. A functional assessment before you go home, covering both sides of this: pain, fatigue and breathlessness; weakness and whether you can sit up, rise to standing and walk; swallowing; bladder and bowel control; vision, hearing and sensation; speech and writing; the practical list of equipment, transport, housing, money, work and getting out; and alongside all of that anxiety, low mood, post-traumatic symptoms, and the behavioral, thinking and social problems. And a review 2 to 3 months after you leave critical care, face to face, in hospital or in the community, repeating that same assessment, done by somebody who knows what happened to you in critical care and what your rehabilitation plan was.
That review is a gate rather than a courtesy call, and this is the single most useful sentence on the page. CG83 says that if you appear to be recovering more slowly than the goals you agreed, or something unexpected has turned up, that is where a referral to a rehabilitation or specialist service is made. It also asks for support for someone who is not getting better as fast as they expected. NICE goes on to say that a structured, supported self-directed rehabilitation manual running at least 6 weeks after critical care may be offered, coordinated throughout by a suitably skilled professional, and consider is the word it uses, so that is something to ask about rather than something you are owed.
QS158 is the other half, and it is the one to quote to a service rather than to a clinician. It has four quality statements: rehabilitation goals; transfer from critical care to a general ward; information on discharge from hospital; and follow-up after critical care discharge. It covers adults with rehabilitation needs after critical illness that required level 2 or level 3 critical care, and it leaves out conditions that have standards of their own, such as head injury, heart attack and stroke. It applies in England and Wales.
Outside the UK the words change and so does who pays. In the United States, Canada, Australia, New Zealand and across Europe, critical care follow-up is arranged differently from one hospital and one insurer to the next, and some units run a follow-up clinic while others have nothing of the sort. We are not going to tell you what you qualify for, because any answer would be wrong somewhere. What travels is the asking: who is coordinating my rehabilitation, when am I being reviewed, and what happens if I am behind.
What to ask for, and what to do if nobody has been in touch
Start with the thing everybody gets wrong. Leaving hospital means you no longer needed a hospital bed. It is not a clearance to start exercising, and it is not a set of limits, and who sets your limits and how to find them is worked through step by step on the hospital stay page.
Then there is a short list worth taking to any appointment, in writing, because people come out of critical illness tired and nothing spoken sticks.
- A name and a phone number for whoever is coordinating your rehabilitation.
- Whether the assessment before discharge was done, and what it found.
- The date of your 2 to 3 month review and who is doing it.
- A referral to rehabilitation, in those words, if you are behind the goals you agreed.
- Whether there is a self-directed rehabilitation manual you can be given.
- Whether the unit you were in runs a follow-up clinic.
- The memory, sleep and mood side, raised in the same conversation as the legs.
If nobody has been in touch, do not read the silence as a clearance. It usually means a form did not travel, and the review is the gate a referral comes through, so missing it quietly costs you the referral. In the UK, if the two month mark passes with nothing booked, ring the number on your discharge letter, or your own doctor's practice, and ask when the review is happening. Elsewhere, ask the unit whether it has a follow-up clinic and ask your own doctor for a rehabilitation referral.
Do not save a new symptom for the review. Anything new, anything suddenly worse, and anything in the warning list below goes now, at the speed that list sets. For practical help at home, and for what the rehabilitation service is called in your country, the hospital stay page covers both.
How to use this program
Start at stage 1 whatever you could do before you were admitted. The commonest mistake in the first fortnight is starting where you used to be rather than where you are, and the second commonest is doing a good day's worth of exercise on a good day and nothing for three days afterward. If even the seated work is beyond you today, do less of it rather than none: one or two of the exercises, once, is a start. A whole week where stage 1 is still beyond you is information for your doctor or physio rather than a reason to push harder, and it has its own line at the foot of the warning list.
Each exercise page gives a typical starting dose, and in the first weeks the bottom of that range is the useful version. The pages do not all mean the same thing by their number, so it is worth reading which.
Where a page says several times a day, as the breathing, the ankle pumps, the quad sets and the grip squeeze do, that number belongs to each go. Where it gives a number once a day, as the knee extension, the band row and the chair stands do, that is the whole day, so split it across your two or three goes rather than repeating it in each one. What your legs feel by bedtime is the total. Stage 2 is one go a day, so there the page's number is the session.
If a physio is setting your numbers, theirs replace these. If nobody is, that is not a reason to wait: take the bottom of the range, let the next morning be the adjuster, and ring the number on your discharge letter or your own doctor's practice to ask for a rehabilitation referral and for someone to set the numbers properly. What to ask for is in the section above.
Soreness for a day or two after a new exercise is normal. Sharp pain during an exercise means stop that exercise for today, and a joint that is more painful or swollen the next day means the load was too much for now, so do less next time rather than stopping altogether. A calf or thigh that is swollen, warm or red is not ordinary soreness and is on the warning list below.
While you exercise, stop straight away if you get chest pain or pressure, feel dizzy or faint, notice a racing or irregular heartbeat, or become far more out of breath than the effort should cause. What to do next is in the warning list below. Breathe steadily through every repetition rather than holding your breath, which matters most if you have high blood pressure. If you have a healing wound on your tummy or your chest, that sentence is doing a second job: holding your breath and straining pushes on the repair from the inside, and that is how a wound comes apart early on and how a bulge appears at a scar later. Breathe out on the effort, and treat an exercise you can only manage by straining as too much for now.
Read the warning list at the foot of this page before you start rather than after something has gone wrong. Its first group is the one that needs emergency services rather than a phone call, and most of what is on the list looks, from the inside, exactly like being weak and tired after critical care.
If somebody is helping you, give them that list too. NICE's own account of what follows critical illness includes not seeing these changes in yourself, so the person in the room is often the first to notice you go gray, grip the counter harder or stop answering, and there is a section further down this page written for them.
If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, keep a hand on the counter throughout, practice only when someone else is at home, and ask your doctor or physio about a falls check. The balance and falls prevention program is the other half of this work, not a replacement for it.
If you have fallen in the past year, feel unsteady or take medicines that make you dizzy, and nobody can be there, stay with stage 1 until somebody can, or until a physio or doctor has seen you. That is not the same as doing nothing, because the seated work needs nobody in the room. The one exception inside stage 1 is standing up from the chair with the armrests, whose own page asks a reader who has fallen before to have somebody nearby for it.
If you live alone, that rule still stands, so plan around it rather than ignoring it. Do the standing and balance exercises at your physio appointments or a falls prevention class rather than by yourself, keep to the seated work of stage 1 when you are on your own, and ask your physio which of the standing exercises you may do alone. Keep your phone in a pocket rather than in another room, so you can reach it from the floor, and ask about an alarm you wear.
If you do fall and cannot get up, or you think you may have hurt your head, neck, back or hip, stay where you are, keep warm and call emergency services, or get someone to call for you. Do not let anyone haul you up first. That line and the rest of the fall routes, including what to do if you got up fine and only hurt later, are in the warning signs below.
Tiredness and weakness are not the same problem and do not answer to the same handling. The pacing side of it is covered on the hospital stay page.
Four situations change the plan. If your admission included an operation, your surgical team's plan replaces this one for as long as it runs, and the wound, clot and repair warning signs matter more than any exercise detail on this page. If the operation was done in a different hospital from the one that sent you home, which happens often after a critical illness, the team who operated is still the one to ask about the wound, about what the repair will take and about what you may lift, push or pull. Their details are on your operation note or your discharge letter, and your own doctor's practice can get hold of them. This page sets no lifting or weight limit of its own, because the limit depends on which operation you had and on the surgeon who did it, and no page can read it off for you.
This page is written for adults, so a child or young person who has been in intensive care follows the plan from their own team, and everything here is a question for that team first. If you are pregnant or recently gave birth, check with your midwife, doctor or physio before you start. And if you came home using oxygen, ask whoever set it up before you begin the standing work.
Heart or chest surgery adds one more. If your chest was opened through the breastbone, which is how most heart surgery and some other chest operations are done, leave out the band row and the wall push-up until your surgeon says the breastbone has healed enough for loaded pushing, pulling and lifting. Pushing yourself up out of a chair with your hands belongs on the same list, which is what the armrest version in stage 1 asks for, so ask your team about that one too. If they have asked you to keep your hands off the armrests, stand up with your arms held out in front of you instead. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
If you came home with a frame or crutches, say that your chest was opened when you ask about the exercises, because leaning and pushing through the arms on a walking aid loads the breastbone as well, and your team may want to change the aid rather than the exercise. If your chest was opened from the side instead, between the ribs, the breastbone rules are not yours, but the same question is: ask the team who operated what the arm on that side may push, pull and lift, and leave out anything that pulls at the wound until they have told you. The breastbone rules are set out in full on the cardiac rehab page.
And one more, if you came home with a tracheostomy tube still in place. Ask the team who look after it before you start the breathing exercise, and keep to the plan they gave you for cleaning it, for suctioning and for what to do if it blocks. Noisy breathing, a hoarse or weak voice, trouble swallowing and pain around the tube are in the warning list below, and any bleeding from it, or any difficulty breathing, needs emergency services.
The two stages below stop at walking about indoors. Stairs, load and getting back out of the house are stage 3 of the hospital stay program, which is where to go next, and the exercises carry on in the same order.
The exercise program
The exercises below carry their own stop signs and precautions. Open the line under an exercise and read them before you try it.
Stage 1: Sitting and lying, in short goes through the day
Start here whatever you could do before you were admitted, and stay here until somebody has cleared standing work for you. Nothing in this stage is done on your feet, so a wobble has nowhere to put you. The breathing exercise is here if you were ventilated or you find yourself short of breath, and if you came home with a tracheostomy tube still in place, ask the team who look after it before you start that one. Ankle pumps and quad sets wake the legs up, and the band row and the grip squeeze matter more than they look, because pushing out of a chair and holding a full mug are hand and arm jobs. Standing up with the armrests is the only exercise in this stage that lifts your own body weight, so leave it out and ask first if anyone limited how much weight goes through a leg, or told you to keep using a frame or crutches. If your chest was opened for heart or chest surgery, the band row and pushing up off the armrests both load the healing breastbone, so leave both of those out until your surgical team has cleared loaded pushing and pulling. Two or three short goes a day beat one long session while you tire this fast, and the bottom of the range on each exercise page is the right place to begin. The pages do not all mean the same thing by their number. The breathing, the ankle pumps, the quad sets and the grip squeeze are the ones whose own pages ask for them several times a day, so their number belongs to each go. The knee extension, the band row and standing up from the chair give a number for the whole day, so split that across your goes rather than doing it two or three times over.
 Diaphragmatic breathing
Stop signs and precautions for the diaphragmatic breathing
Before you start
- If lying flat makes you more short of breath, do not lie flat for this. Sit upright in a chair or prop yourself on pillows instead, which works just as well for learning the pattern. Being short of breath when you lie down, waking at night needing to sit up to breathe, more swelling in your ankles or legs, or gaining weight quickly over a few days are all reasons to get medical advice the same day rather than to practice through, because the NHS lists breathlessness when lying down among the reasons to get urgent advice.
- If you are pregnant and past the first three months, check with your physio before exercising flat on your back.
When to stop and get help
- Your fingers or the skin around your mouth start to tingle, or you feel light-headed or spaced out. This can mean you are breathing too fast or too deeply, so stop and let your breathing go back to normal. If it has not settled within a few minutes, get medical advice the same day. If you faint, or the numbness or tingling is on one side of your face or body, call emergency services, even if it goes away.
- You suddenly become short of breath, your chest feels tight or heavy, or you are far more short of breath than usual. Stop, rest and use your breathing control. Call emergency services if the breathlessness came on suddenly, your chest feels tight or heavy, your breathing does not go back to normal, you are gasping, choking or cannot get your words out, you have pain that spreads to your arms, back, neck or jaw, you feel suddenly confused or very drowsy, or your lips or skin turn very pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands). If everything settles quickly, get medical advice the same day before you do these exercises again.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Ankle pumps
Stop signs and precautions for the ankle pumps
Before you start
- Had surgery on your foot or ankle, or wearing a cast or boot? Check which movements are allowed before you start.
When to stop and get help
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- You suddenly become short of breath, get chest pain or pain in your upper back that may be worse when you breathe in, cough up blood, your heart beats very fast, or you faint. Call emergency services straight away, even if your leg looks normal, as this can be a blood clot in the lungs (pulmonary embolism).
- Any sharp pain in the foot or ankle.
- Emergency: while you are in a cast or boot, your toes turn blue, white or pale, or feel cold. Do not wait to see if raising your leg helps. Go to an emergency department straight away, and do not drive yourself. The cast or boot may be cutting off the blood supply, or pressure may be building up inside the leg (compartment syndrome), and both need checking quickly.
- In a cast or boot, the pain gets worse, your toes feel numb, tingle or burn or look more swollen, or the cast or boot feels too tight. Stop, raise your foot to about hip level and no higher, keep moving your toes and contact your fracture clinic or get medical advice straight away. If you wear a boot, loosen the straps but keep it on. Do not prop the foot higher than that and do not put ice on it, because if pressure is building up inside the lower leg both of those cut down the blood reaching your foot. If you cannot move your toes, the pain is severe even after painkillers, or the numbness, tingling, burning or swelling has not settled within 30 minutes of raising your foot, go to your fracture clinic or an emergency department straight away, and do not drive yourself.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
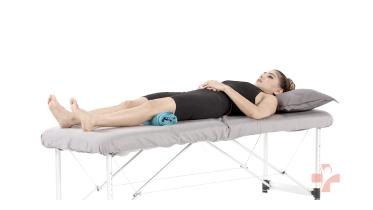 Quad sets (towel under knee)
Stop signs and precautions for the quad sets (towel under knee)
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
When to stop and get help
- Your knee pain goes up sharply.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
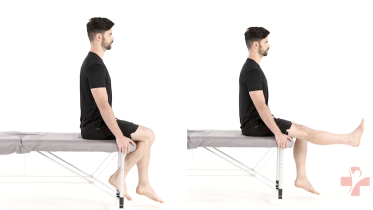 Seated knee extension
Stop signs and precautions for the seated knee extension
Before you start
- After knee ligament surgery, such as an ACL reconstruction, get the go-ahead from your surgeon or physio before you do this one. Many protocols limit how far the knee may straighten against resistance in sitting during the early stage.
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. Ask again before you add an ankle weight.
When to stop and get help
- You feel sharp pain at the front of the knee or under the kneecap.
- The knee swells up or is clearly more painful later that day or the next morning.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
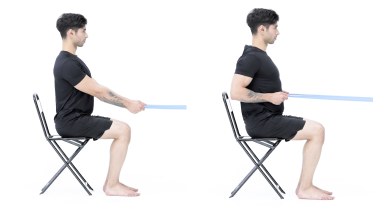 Seated row with band
Stop signs and precautions for the seated row with band
Before you start
- After shoulder surgery, rows with a band usually wait until later in rehab, so check with your surgeon or physio first.
- After heart or chest surgery, pulling against a band usually waits until your breastbone has had time to heal, so ask your surgeon or surgical team when to start: only the team that wired it can clear loaded pulling. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
- If you have high blood pressure, breathe steadily through every repetition and never hold your breath.
- Do not lean forward to reach the band or twist to one side as you pull, and if you have had a fracture in your spine, check with your physio before you start.
When to stop and get help
- A sharp pain or catching feeling in your shoulder as you pull.
- Pain, tingling or numbness spreading down an arm.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- A sudden pop or snap at the front of your elbow, sudden sharp pain there, or the muscle at the front of your upper arm bunches up or changes shape. Stop and go to an urgent care center or emergency department the same day, even if you can still bend the elbow, as this can be a torn biceps tendon.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Hand grip squeeze
Stop signs and precautions for the hand grip squeeze
Before you start
- After a broken wrist, hand or forearm, or surgery on any of them such as a tendon repair, start only when your doctor, surgeon, physio or hand therapist says the bone or repair is ready for this, and follow their plan for how much to do.
- Arthritis at the base of the thumb and rheumatoid arthritis can both flare with hard gripping. Ask your physio how firm to go, and skip it on days when the joints are hot and swollen.
- Keep breathing through each hold, because holding your breath while you strain can push your blood pressure up.
When to stop and get help
- Sharp pain in the wrist, a finger joint or at the base of the thumb.
- Your hand or fingers go numb or start to tingle. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- Hand joints that are more swollen, hot or stiff afterward.
- Since the fracture or cast, the hand is getting more painful rather than less, the skin becomes very sensitive to light touch, or the hand changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
 Sit to stand using armrests
Stop signs and precautions for the sit to stand using armrests
Before you start
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try sit to stand using armrests. Lowering into a chair and rising from it takes the hip beyond a right angle when the seat is low, and many surgeons ask you to avoid that for the first months after some operations.
- After recent heart or chest surgery through the breastbone, ask your surgeon or surgical team before you push up through the armrests, because pushing down through your hands loads the healing breastbone. If they have asked you to keep your hands off the armrests, stand up with your arms held out in front instead. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
- If knee pain builds as you go, or you have had knee surgery, check with your physio what seat height to use.
- If balance is a worry or you have fallen before, have someone nearby and place the chair next to a counter or wall you can reach once upright. If you have osteoporosis, set the chair up the same way, next to a counter or wall, though thin bones on their own are not a reason to wait until someone is at home before you stand up out of a chair. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet.
When to stop and get help
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services. A drop in blood pressure on standing, or a side effect of a medicine, can cause this, so mention your medicines when you get advice.
- Your knee, hip or back hurts sharply, or a wrist or shoulder hurts as you push on the armrests.
- A leg buckles, or you feel close to falling.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
Stage 2: Standing with a hand on the counter
Move up when stage 1 feels easy, you are no worse the next morning, and standing exercise has been cleared for you. One hand stays on a kitchen counter, a solid worktop or a sturdy chair back for the whole of every exercise here, not just for the first few repetitions, and the walking practice uses your stick, crutches or frame instead. Balance at a chair is the one exercise here that eventually asks you to take the hand off, and it has conditions of its own. Standing up without your hands is the exercise that earns its place in this stage, because it is the movement most people find has gone. Taking the hand off at balance at a chair is something you work up to here rather than start with, so do that one with your hand resting on the chair back, like everything else in this stage, until three things are true: you have done the other standing exercises for at least a week, standing up has not left you dizzy or lightheaded, and you have not had to grab your support to stay upright in any of them. Then let go for a few seconds at a time with the chair inside arm's reach, put your hand straight back the moment you sway, and do that part only when somebody else is in the house, whether or not you have ever fallen. Build toward the hold times its own page gives over weeks rather than in one session. Keep the hand on for now, and ask your physio or doctor to watch you let go before you try it on your own, if you have fallen in the past year, feel unsteady on your feet or take medicines that can make you dizzy. Tablets or injections to lower your risk of a blood clot are no reason to skip balance work, because getting steadier is what keeps you off the floor, but they are a reason to have somebody with you, and a knock to the head while you are taking them has its own line in the warning list below. The wall push-up loads your arms with your feet still on the floor, so leave that one out and ask first if an arm is in a sling or a splint, if your chest was opened for heart or chest surgery, or if anyone limited what you lift, push or pull. One go at each of these a day is plenty to begin with, and start at the bottom of the range each exercise page gives rather than the top, because seven exercises at the top of their ranges is far more standing work than it looks like on the page. The wall push-up page asks for a few days a week rather than every day, and the calf raise page offers either, so give those two a day off in between, and longer if your arms or calves are sore the next morning. If you came home with a walking aid it stays in your hand until a physio says otherwise. If nobody gave you one, do not buy one for this program, because the wrong height or the wrong hand makes walking less steady: practice the walking with a hand along the worktop or close to a wall instead, and ask your physio or doctor which aid, if any, suits you.
 Sit to stand
Stop signs and precautions for the sit to stand
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try sit to stand. Standing up from a low seat bends the hip past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask them how high your seat should be. If you are pregnant, check with your midwife or physio before you start.
- Set up before the first stand: use a chair that will not slide, ideally with its back against a wall, and have someone nearby, or set the chair beside a kitchen counter you can reach, if you are not sure of your balance or you have fallen in the past year. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet.
When to stop and get help
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services.
- Sharp pain in the knee, hip or lower back.
- Your knee gives way or you feel you might fall.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
- You are pregnant and notice bleeding or fluid leaking from your vagina, regular painful tightenings, tummy pain that does not settle when you rest or comes with lower back pain, or a change in your baby's usual movements, such as moving less than usual. Stop and contact your midwife or maternity unit straight away. Do the same for a severe headache, problems with your vision such as blurring or flashing lights, pain just below your ribs, or sudden swelling of your face, hands or feet, which can be signs of pre-eclampsia. Call emergency services if the bleeding is heavy, the tummy pain is severe, bleeding or tummy pain comes with pain in your shoulder or feeling sick, faint or dizzy, or a headache comes on suddenly and is very severe.
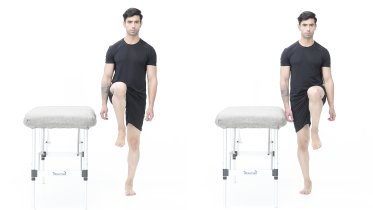 Standing marching
Stop signs and precautions for the standing marching
Before you start
- If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try standing marching. Bringing the knee up above hip height bends the hip past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask your team how high to lift, and when you may stand on the operated leg alone while the other knee comes up.
When to stop and get help
- A sharp pinch in the groin or the crease of the hip as your knee rises.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You feel unsteady even with your fingertips on the support. Grip it with your whole hand and lower the lifted foot.
 Standing hip abduction
Stop signs and precautions for the standing hip abduction
Before you start
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try standing hip abduction. Some operations limit this kind of work for the first months, so the timing depends on your surgery. Your surgical team will also tell you how far to lift.
When to stop and get help
- You feel sharp pain at the side of the hip, in the groin or in the lower back.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You feel unsteady, even with the chair.
- Pain, numbness or tingling runs down the leg.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Calf raises
Stop signs and precautions for the calf raises
Before you start
- After an Achilles tendon repair or ankle surgery, calf raises usually come in at a set stage of your surgeon's protocol, often on both feet before one. Check with your physio before you start.
- After a knee or hip replacement, or other leg surgery, follow your surgeon's or physio's plan, and hold a counter or a sturdy chair back for the whole set. Rising onto your toes puts your weight forward onto a smaller base, which is where the balance goes.
When to stop and get help
- Sharp pain in the Achilles tendon, heel or arch.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
- Achilles or heel pain that is clearly worse the next morning. Ease off and check with your physio.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- Your ankle gives way, or you lose your balance.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Standing balance at a chair
Stop signs and precautions for the standing balance at a chair
Before you start
- After a knee replacement or other knee surgery, a hip replacement, or a broken hip or leg fixed with screws, a nail or a plate, follow your surgeon's or physio's weight-bearing plan, and start this exercise only when they have cleared you. Taking your hand off the chair puts your full body weight through both legs, so if you have been told to put only part of your weight through that leg, or none of it, or to keep using a frame or crutches for now, this exercise is not yours yet, whatever the leg feels able to do. Keep the hand on the chair until they tell you it can come off.
When to stop and get help
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You start to tip and need the chair to catch yourself. Put your hand back on it, rest, then try a shorter hold.
 Wall push-ups
Stop signs and precautions for the wall push-ups
Before you start
- After a broken or dislocated elbow, or elbow surgery such as a tendon repair, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. If you have just hurt your arm and have severe pain or cannot move the elbow, do not exercise it. Go to an urgent care center or emergency department the same day. If you heard a snap or a crack at the moment of the injury, the arm looks a different shape or sits at an odd angle, a bone is showing, or your arm or hand tingles, feels numb or turns cold, pale or blue, go to an emergency department straight away or call emergency services, and do not drive yourself.
- After shoulder surgery, including a rotator cuff repair, or after a shoulder fracture or dislocation, follow your surgeon's or physio's plan, and do only the movements and range they have cleared. Many plans allow only passive movement at first, where the arm is moved for you and its muscles stay relaxed. Putting weight through your arms usually comes later, so check with your physio first.
- After recent heart or chest surgery, get your surgeon's or surgical team's okay first, because leaning your weight into your hands and pressing back off the wall loads the healing breastbone and the front of the chest. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
When to stop and get help
- Sharp pain in the shoulder, elbow or wrist.
- Pain, numbness or tingling spreads down the arm.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- Your feet start to slip on the floor.
- A sudden pop or tearing feeling in the shoulder that brings sharp pain, new weakness or trouble lifting the arm. Stop and contact your surgical team the same day, or get medical advice the same day if you have not had surgery.
- The shoulder feels as if it has slipped out of place, looks a different shape or suddenly locks so you cannot move the arm, or your hand turns cold, pale or blue. Go to an emergency department straight away, without driving yourself, and do not try to put the shoulder back in yourself.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
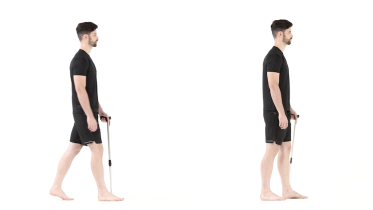 Walking with a cane
Stop signs and precautions for the walking with a cane
Before you start
- If you have broken a bone in your leg or had an operation on it, follow the weight-bearing plan your surgeon or physio gave you. Do not swap crutches or a frame for a single cane until they tell you that you are ready.
When to stop and get help
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You stumble, your leg gives way, or you have to grab something to stay upright. Stop and sit down.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- New or much worse pain in your hip, knee or ankle that changes the way you walk.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
- You have had a fall or an injury and now have severe hip pain, or you cannot walk or put weight on the leg. Call emergency services or go to an emergency department. This can be a sign of a broken hip (hip fracture).
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
For the person helping
You may well be the one reading this, because the person you are reading it for is too tired to. Two changes are worth more than anything else you will do, and both are things only you can see.
The first is confusion, and it has two faces. Somebody who suddenly goes muddled, much drowsier, unable to follow what is being said or who is seeing things that are not there is an emergency at home, whatever has caused it. The quiet version is the one that gets missed: withdrawing, answering slowly, moving about less, losing interest in food, over hours or days rather than weeks. That one needs advice the same day, and both lines are in the warning list at the foot of this page.
The second is the night side. If they have started trying to stay awake to avoid nightmares, if memories of the unit are pushing their way in, if panic has turned up and keeps turning up, or if they change the subject fast whenever the illness comes near, those are on NICE's own list of markers that somebody needs rehabilitation rather than ordinary distress. Report them the way you would report a swollen calf.
Then there is you. The five year follow-up of those lung injury survivors reported that physical and psychological problems developed or carried on in the family caregivers as well as in the patients, out to five years (Herridge and colleagues, 2011). Broken sleep, dread, going over the weeks in the unit again and again: that is part of the same picture, it has the same route through your own doctor, and asking early about carer support where you live is the sensible thing to do.
The practical half of helping, how to set the chair up, how to be present without taking the work away, and getting the medicine list reviewed, is on the hospital stay page.
When to see a physio or doctor
See a physio or your doctor if nothing has moved over two or three weeks, if the exercises in stage 1 are beyond you, if you are not sure which stage you belong in, or if you are behind the goals somebody set with you. In the UK, add one more trigger: the two month mark arriving with no review booked. A physical therapist (physiotherapist) can measure where you are now, which is far more useful before you start than after a disappointing month.
Check with your doctor before you begin if you have a heart or lung condition, blood pressure that is not under control, or if you came home on oxygen. If you were given a rehabilitation plan or a referral when you left, use that rather than this page, and take this page along if it helps the conversation.
Some things need help faster than an appointment, from a call to emergency services down to a visit in the next few days. They are all in the warning signs below, each with its own timing. Read that list before you start the program and again a fortnight later, because the items on it are not the ones you would think to watch for.
For physiotherapists
Treat ICU-acquired weakness as a diagnosis rather than as the severe end of deconditioning. Critical illness polyneuropathy and critical illness myopathy present as weakness and as failure to wean, the structural picture is axonal degeneration, myosin loss and muscle necrosis, and confirmation rests on clinical, electrophysiological and biopsy grounds; the same paper reports prolonged ventilation, longer hospitalization, higher hospital mortality and chronic disability in survivors, suggests glycemic control might reduce severity, and suggests early rehabilitation in the unit might improve functional recovery and independence (Latronico and Bolton, 2011). We state no prevalence figure anywhere on this page, because the figures in circulation rest on different definitions in different populations and none could be traced to a primary source here.
On in-unit dose, TEAM is the trial to have read. It is an Australian and New Zealand trial, with registered sites in the UK, Ireland and Germany as well (NCT03133377).
750 ventilated adults were randomized to increased early mobilization, through sedation minimization and daily physiotherapy, or to usual care. Mean daily active mobilization reached 20.8 minutes against 8.8, and the median number of days alive and out of hospital at 180 days was 143 against 145, a difference of 2.0 days fewer in the intervention group with a confidence interval running from 10 days fewer to 6 days more. Death by day 180 was 22.5 percent against 19.5 percent, serious adverse events occurred in 7 patients against 1, and adverse events potentially attributable to mobilization, meaning arrhythmias, altered blood pressure and desaturation, occurred in 9.2 percent against 4.1 percent (Hodgson and colleagues, 2022). More and earlier is therefore not established as better inside the unit, and the trial says nothing either way about what you do after discharge.
For the English pathway, CG83 recommendations 1.23 to 1.25 are the ones to quote in a letter. The 2 to 3 month functional reassessment is a referral gate, not a check-in call: slower recovery than the agreed rehabilitation goals, or unanticipated morbidity, is what triggers onward referral, and the reassessment is meant to repeat the pre-discharge dimensions so there is something to compare. QS158 is the service-level lever in England and Wales, with its four statements on rehabilitation goals, transfer to a general ward, discharge information and follow-up after critical care.
Measure the non-ventilatory limitation rather than assuming the lungs. In the five year ARDS cohort, pulmonary function was normal to near normal while the median six minute walk sat at 76 percent of predicted and the physical component summary at 41 against a norm of 50 (Herridge and colleagues, 2011). The six-minute walk test, the 30-second chair stand test and the Timed Up and Go each carry their own norms and are repeatable in a living room.
Screen the non-physical dimension at every contact, because a program that stops at the legs is the usual way this goes wrong. CG83 puts the physical and non-physical lists into one assessment for a reason, and the four at-risk markers it names, recurrent nightmares with sleep avoidance, intrusive memories, new recurrent anxiety or panic, and reluctance to discuss the illness, are askable in under a minute. Swallowing belongs in the same minute: it is on CG83's physical list, and the page's same-day dysphagia route is written for a patient who has quietly started avoiding drinks.
Warning signs
Get emergency help now
- Emergency: if chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
- Emergency: you are short of breath and you have pain that spreads to your arm, neck, jaw, back or stomach, even if your chest itself does not hurt. Call emergency services straight away. A heart attack does not always begin with chest pain, and the NHS names pain spreading to your arms, back, neck and jaw among the reasons to get emergency help when you are short of breath.
- Emergency: since your hospital stay, you suddenly become short of breath, you get chest pain or pain in your upper back that may be worse when you breathe in, you cough up blood, your heart is beating very fast, or you faint. Call emergency services straight away, even if your legs look normal. These can be signs of a blood clot in the lungs (pulmonary embolism).
- Emergency: severe difficulty breathing, meaning you are gasping, choking or cannot get your words out, or your lips or skin turn very pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands). Call emergency services straight away. This counts whether or not you have a cough or a temperature, and whether the breathlessness came on within the hour or built up over days. The NHS names both of these among the reasons to get emergency help for shortness of breath.
- Emergency: any sign of a stroke, even if it goes away. That means a face that droops on one side, an arm you cannot lift or keep up, slurred or muddled speech, weakness or numbness on one side of your body or face, sudden blurred vision, double vision or loss of sight, trouble swallowing, sudden dizziness with unsteadiness or falling over, a sudden severe headache, or a sudden fall where your legs give way but you do not black out (a drop attack). Call emergency services straight away.
- Emergency: sudden confusion, for example you, or the person you care for, suddenly become muddled, much drowsier than usual, unable to follow what is said, unsure where you are, or you see or hear things that are not there. Call emergency services or go to an emergency department straight away, without driving yourself, and take your medicines or a list of them with you. Sudden confusion can come from an infection, a stroke, a head injury, a low blood sugar level in someone with diabetes or other causes that need treating quickly.
- Emergency: a racing, pounding, fluttering or irregular heartbeat that does not settle when you rest, or that comes with dizziness, feeling faint or fainting, chest pain or shortness of breath. Call emergency services straight away. If it has already stopped, get medical advice the same day.
- Emergency: a wound from an operation that splits or gapes open, bleeds heavily, suddenly leaks a gush of pink, watery fluid, or has anything bulging or coming out of it. Call emergency services or go to an emergency department straight away, and do not drive yourself. Do not push anything back in and do not try to pull the wound closed; cover it with a clean dressing or a clean towel and lie down until help comes. A wound that is coming apart needs a surgeon rather than a dressing change, and it does not wait for a fever or for the next clinic appointment. If you cannot tell whether a wound is only starting to part at the edges or has come apart, treat it as this line rather than as the same day wound line further down this list.
- Emergency: blood coming from a tracheostomy tube, from the hole in your neck where one was, or coughed up through it, however little and even if it stops on its own. Call emergency services straight away. Bleeding there can come from a blood vessel lying against the windpipe, and a small bleed that settles by itself can be the warning before a large one.
- Emergency: you have just fallen and cannot get up, or you think you may have hurt your head, neck, back or hip. Stay where you are, keep warm and call emergency services, or get someone to call for you. If you got up and walked without trouble and only notice pain later, without any of the emergency signs above, use the same-day lines in this list instead.
- Emergency: you fell and cannot remember the fall or how it happened. Go to an emergency department straight away, and do not drive yourself. You may have blacked out or hit your head without knowing it.
- Emergency: after a knock to the head, being very drowsy or finding it hard to keep your eyes open, confusion, a fit (seizure), new weakness or numbness anywhere in your body, new trouble understanding, speaking, walking or keeping your balance, new problems seeing or hearing, clear fluid coming from your ears or nose, bleeding from your ears or bruising behind them, a black eye when your eye was not hit, a dent in your head or a wound with something stuck in it, or a change in behavior. Call emergency services straight away. These can be signs of an injury to the brain.
- Emergency: a knock to the head in a high-energy accident, even if you feel completely well. That means a fall from a height of more than 1 meter (about 3 feet) or more than 5 stairs, a crash at high speed, a car that rolled over, being thrown from a vehicle, being hit by a vehicle while walking or cycling, a bike crash, an accident on a quad bike or similar motorized vehicle, a fall from a horse, a diving accident, or any other heavy, fast impact to the head. Call emergency services straight away, without waiting to see how you feel. A high-energy head injury is a reason for emergency assessment on its own, with no symptoms needed.
- Emergency: after a knock to the head, you were knocked out, even for a moment, you cannot remember what happened just before or after, you have had a headache ever since, or you are being sick (vomiting). The same applies, even if you feel fine, if you take medicine that thins your blood, other than aspirin on its own, have a bleeding or clotting condition, have had brain surgery in the past, or had been drinking alcohol or taking drugs when it happened. Go to an emergency department straight away, and do not drive yourself.
- Emergency: severe neck pain after a knock to the head, whatever the fall or the knock was like. Keep still and call emergency services, and do not let anyone move you until someone trained has checked your neck. If the neck pain only starts later and nobody has checked your neck since, go to an emergency department straight away, and do not drive yourself.
- Emergency: after a knock to the head, swelling, a deep cut or severe pain at the exact spot that was hit. Call emergency services or go to an emergency department straight away, and do not drive yourself. These can be signs of a broken skull.
Get help today
- Same day: a calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Same day: in the days or weeks since you came home you are getting more and more tired, breathless doing everyday things such as walking to the toilet or getting dressed, dizzy or lightheaded, your heart is racing, or your skin looks paler than usual. Contact the team who looked after you, or get medical advice the same day. Tiredness and breathlessness that build up like this are not part of the usual recovery. Blood loss from an illness, an injury or an operation can leave you short of red blood cells (anemia), which is treatable, and a slow bleed or an infection can show up the same way. If breathlessness comes on suddenly, or you get chest pain, call emergency services, as the emergency line above explains.
- Same day: a new or worsening cough, phlegm, a high temperature, chest pain when you breathe or cough, or feeling more short of breath than you were when you came home. Get medical advice the same day. A chest infection can show up as a cough, breathlessness, a high temperature, chest pain, wheezing, an aching body, loss of appetite and tiredness, and the NHS notes that feeling confused is common in older people who have pneumonia, so the first sign is not always a cough. If you are struggling to breathe, your lips, skin or tongue turn pale, blue or blotchy, you cough up blood, your heart is beating very fast or you suddenly feel confused, call emergency services. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: you cough or choke when you eat or drink, food sticks in your throat or chest, your voice sounds wet or gurgly after you swallow, food or drink comes back up, or you are short of breath after eating or drinking. Get medical advice the same day, and ask whether you need your swallowing assessed by a speech and language therapist. The NHS names coughing or choking while eating or drinking, food that feels stuck, a wet, gurgly voice and being short of breath after eating as reasons to get urgent advice, and lists repeated chest infections, weight loss and dehydration among what a swallowing problem leads to over time. An unsafe swallow is one of the ways the chest infection in the line above starts, so this is worth raising even if your swallowing was checked before you came home. If trouble swallowing came on suddenly, use the stroke line above and call emergency services. If you or someone with you is choking and cannot cough, speak or breathe, call emergency services straight away.
- Same day: since your breathing tube or your tracheostomy came out, your breathing has turned noisy by day or at night, you snore when you did not before, your voice has stayed hoarse or weak for more than a week, swallowing has become a problem, you cough or are sick after eating or drinking, or the area where the tube was is painful, raised or uncomfortable. Get medical advice the same day and say that you were on a ventilator or had a tracheostomy, because the windpipe and the voice box can be narrowed or injured where a tube sat, and the NHS names each of these as a reason to get urgent advice once you are home after a tracheostomy. Breathing that gets noisier and harder rather than easier is not a fitness problem and does not belong in an exercise plan. If you have any difficulty breathing, call emergency services.
- Same day: you have become short of breath when you lie down flat, or you wake in the night needing to sit up to breathe, your ankles, legs or tummy are more swollen than when you came home, you have gained weight quickly over a few days, or you are coughing up frothy pink phlegm. Get medical advice the same day. The NHS lists breathlessness when you lie down, suddenly gaining weight and coughing up frothy pink phlegm as reasons to get urgent advice, because the heart may not be keeping up with the fluid in your body, which is treatable and is a common reason for going back into hospital in the first weeks at home. If you are struggling to breathe, your lips or skin turn pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands, the soles of the feet or the gums), or you have chest pain, call emergency services.
- Same day: since an operation, the wound is red, hot, swollen, leaking fluid or opening up, you have a fever or feel hot and shivery, or the pain in that area is new or getting worse quickly. Contact your surgical team or the ward you went home from the same day rather than waiting for your physio appointment, and if you cannot reach them, go to an emergency department the same day. This can be an infection in the wound or deeper, around a repair or a new joint. Redness can be harder to see on brown or black skin. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: since heart or chest surgery through your breastbone, the breastbone clicks, cracks, grinds or feels as if it shifts or moves apart when you cough, laugh, turn over in bed or use your arms, or the middle of your chest becomes more painful or feels loose. Stop the arm, pushing, pulling and lifting exercises, hold a folded towel or a cushion against your chest when you cough, and contact your surgical team the same day, or get urgent medical advice if you cannot reach them. A breastbone that has not knitted back together is a surgical problem rather than something exercise settles, and your physio cannot clear it. If the chest wound gapes open, bleeds heavily or you can see bone, go to an emergency department straight away.
- Same day: the skin around a drip, line, feeding tube, drain or catheter you came home with is red, hot, swollen, painful or leaking, the dressing keeps getting wet or dirty, or you get a temperature, feel shivery or feel suddenly unwell when it is used or flushed. Get medical advice the same day from the team who put it in or the ward you went home from, and if you cannot reach them, go to an emergency department the same day. An infection can pass straight into the blood from a line, which is why this one does not wait. If you feel very unwell, or you have any of the sepsis signs listed above, call emergency services.
- A soft lump at or near a scar from an operation on your tummy or groin, or at or near your belly button, that gets bigger when you cough or strain, or that gets smaller or disappears when you lie down. This can be a hernia, so see your doctor. If the lump becomes painful or tender, if it used to flatten when you lay down and now stays up, or if you have a bloated tummy, you feel or are being sick, you are constipated, or you have a high temperature or feel hot, cold or shivery, get medical help straight away, the same day, for example at urgent care or an emergency department, and do not try to push the lump back in yourself. If the pain is severe or came on suddenly, you cannot poo or pass wind at all, you are vomiting blood or your vomit looks like coffee grounds, or you have suddenly become confused, call emergency services or go to an emergency department straight away.
- Same day: in the past few hours or days you, or the person you care for, have become quieter and more withdrawn, slower to answer, harder to hold a conversation with, less interested in food, or are moving about less than usual, and this is a change from how you were. Get medical advice the same day and say when the change started. NICE names withdrawal, slow responses, reduced movement, worse concentration and a smaller appetite as the signs of the quiet kind of delirium, which is the kind most often missed, and asks for changes like these to be assessed rather than watched. Delirium is common and usually passes, but the cause of it needs finding. If the confusion came on suddenly, or they are much drowsier than usual, muddled or cannot follow what is said, use the emergency line above instead. If they also have a temperature, are not drinking, or you cannot keep them awake, call emergency services.
- Same day: thoughts of suicide or of harming yourself, even if you do not plan to act on them. Get urgent help the same day from your GP or NHS 111 in the UK, and you can also talk to Samaritans on 116 123. If you have harmed yourself or feel you may be about to, call emergency services or go to an emergency department straight away.
- Same day: you blacked out or fainted, even for a moment. Get medical advice the same day. Call emergency services instead if the person is not breathing, cannot be woken within 1 minute, has not fully recovered or has trouble speaking or moving, has chest pain or a pounding, fluttering or irregular heartbeat, fainted while exercising or lying down, is shaking or jerking, or was badly hurt.
- Same day: dizziness, lightheadedness, blurred vision or feeling faint when you stand up that is new for you, does not pass within a minute or two, keeps happening, or has made you fall. Sit or lie down, and get medical advice the same day. This can be a drop in blood pressure on standing (postural hypotension), a type of low blood pressure, which the NHS lists among the causes of falls, and your doctor can check it. Tell them about your medicines, because some can cause it. If it does not settle within a few minutes of sitting or lying still, call emergency services.
- Same day: dizziness or feeling faint during or after exercise, other than the brief lightheadedness as you stand up covered in the line above, without any of the emergency signs above. Stop the exercises and get medical advice the same day. If you faint, it does not settle within a few minutes of sitting still, or you cannot stand or walk steadily, call emergency services.
- Same day: after a fall, you are in pain, have hurt yourself or feel unwell, or you were on the floor for an hour or more, without any of the emergency signs above. Get medical advice the same day, even if you managed to get up.
- Same day: a leg or foot that is getting weaker, for example your foot drags, catches on the ground or slaps down when you walk (foot drop). Get medical advice the same day. If the weakness is getting worse by the hour, go to an emergency department.
- Same day: you are taking tablets or having injections to lower your risk of a blood clot and you notice blood in your urine, black or bloody stools, bleeding gums, a nosebleed that goes on and on, bruising far beyond what the knock would explain, or you are being sick or coughing up blood. Get medical advice the same day, and do not stop the medicine on your own. Bleeding more easily is the known trade-off of these medicines (NHS), and the dose or the type may need looking at. Go to an emergency department if the bleeding will not stop, you feel faint, or you bang your head while you are taking it, even if you feel fine, because the NHS advises getting urgent advice after a head injury on medicine that thins your blood and only a hospital can scan for a bleed inside the head.
- Same day: new hip or groin pain after a fall, even a small one, if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time, even if you can still walk. Get medical advice the same day. A broken hip is not always obvious at first.
- Same day: back pain after a minor fall or strain if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time. Get medical advice the same day. Until it has been checked, stop the exercises and keep away from lifting, bending forward and twisting, because those load a bone in the spine that may be broken.
- Same day: a sore, a blister or broken skin over a bony area such as a heel, hip, bottom, tailbone or elbow that is hot, swollen, red or darker than usual, has pus coming from it, is severely painful or getting more painful, or comes with a high temperature. Get medical advice the same day, from your doctor, a nurse or NHS 111 in the UK. An infected pressure sore (pressure ulcer) needs treating, and the risk is higher while you move less than usual and in the weeks after an operation (NHS). If you feel very unwell, or you have any of the sepsis signs listed above, call emergency services.
- Losing weight without trying. If you are being treated for cancer now, contact your cancer team the same day.
- Losing weight without trying. If you also have new back or neck pain, get medical advice the same day.
Book an appointment
- Losing weight without trying. See your doctor within a day or two and mention it.
- Within a few days: a patch of skin over a bony area, such as a heel, hip, bottom, tailbone or elbow, that is discolored and does not change color when you press it (usually red on white skin, purple or blue on brown or black skin), that feels warm, spongy or hard, or that is sore or itchy. Book an appointment with your doctor or nurse within a few days, keep the pressure off it until then and change position often. That is how a pressure sore (pressure ulcer) starts, and the risk is higher while you move less than usual, in the weeks after an operation, and where you sit or lie in one position for long (NHS). If it is already broken, weeping or painful, use the same day line above.
- Within a few days: you have had a fall, even if you were not hurt, or you keep tripping, stumbling or feeling that your legs might give way. Book an appointment with your doctor within a few days and ask about a falls assessment. Tell them about every fall, even the ones where you were not hurt.
- Routine: your strength or your walking has stopped improving over a week or two, or you cannot manage the exercises you were given, and you have none of the signs above. This is not an emergency, but ask your physio or your doctor for a review in the next week or two.
Common questions
How long can post intensive care syndrome last?
Months at least, and in some people years. The NHS puts the usual timescale for problems after intensive care at several months and says to get medical advice if any of them is persistent. The longest follow-up we can point you at tracked 109 survivors of acute respiratory distress syndrome, a severe lung injury, out to five years: at the five year mark the median distance they walked in six minutes was 436 meters, which is 76 percent of the predicted distance, and their physical quality of life score averaged 41 against a matched population average of 50 (Herridge and colleagues, 2011). Younger patients improved faster than older ones, and neither group got back to predicted normal. That was one severe condition and a long stay, so it is the far end of the range rather than a forecast for everybody, and improvement in that study was still happening years in rather than stopping at a tidy point.
How is post intensive care syndrome diagnosed?
It is not a single test, and it is not really a diagnosis in the way a broken bone is. The term came out of a stakeholders' conference convened by the Society of Critical Care Medicine, as a way of naming the problems that persist after critical illness (Needham and colleagues, 2012), and a later review puts it plainly: it is not a medical diagnosis but a concept for raising awareness of what follows intensive care (Hiser and colleagues, 2023). What happens in practice is an assessment of each part of it: strength and what you can physically manage, breathing, swallowing, mood, sleep, memory and attention. NICE asks for exactly that assessment before you leave hospital and again at the 2 to 3 month review, using the same list both times, so progress can be compared against something. The important half for you is that you do not need the label to be assessed or referred.
How is post intensive care syndrome treated?
By treating the parts of it you have, which is why no single treatment gets named here. For the physical side it is rehabilitation, started at the level you are at now and progressed, which is what the program on this page is. NICE describes an individual structured rehabilitation program with frequent reviews for people it classes as at risk, a review of the medicines, and support with nutrition, and it says a structured, supported self-directed rehabilitation manual running at least 6 weeks after critical care may be offered with a suitably skilled professional coordinating it throughout. The mood, sleep and memory side goes to whoever assesses it rather than to an exercise page. We name no medicine, because we have no source that supports one for this.
Can post intensive care syndrome be prevented?
Most of what is under discussion happens in the unit rather than at home, so this is not a question you failed. NICE asks for a short assessment during the critical care stay, as early as is clinically possible, to work out who is at risk of physical and non-physical problems, and for rehabilitation to start early in those people. What has not worked is the obvious idea of simply doing more, sooner. In a trial of 750 ventilated adults, more early active mobilization produced an average of 20.8 minutes of active movement a day against 8.8 minutes in usual care, did not increase the number of days patients were alive and out of hospital at 180 days, and came with more adverse events during mobilization, 9.2 percent against 4.1 percent (Hodgson and colleagues, 2022). Treat anyone selling prevention as a product with that in mind.
Why am I so weak after ICU?
Partly because a critical illness can damage the nerves and the muscle themselves, which is a different thing from losing fitness. Critical illness polyneuropathy affects the nerves and critical illness myopathy affects the muscle, and the two are often grouped as ICU-acquired weakness. The changes described include degeneration of nerve fibers, loss of myosin, which is the protein muscle uses to pull, and death of muscle cells, and the diagnosis rests on examination, electrical tests of nerve and muscle, and sometimes a muscle biopsy (Latronico and Bolton, 2011). Some of what the paper describes is functional rather than structural, nerves and muscle that stop carrying the signal properly for a time, with weakness that reverses. This page gives no figure for how many people get it, because the numbers in circulation come from studies that defined it differently in different groups of patients. The practical reading is that slow progress is expected, while weakness that is worse this week than last is a symptom and belongs with a doctor.
Does post intensive care syndrome affect the family?
The relatives come out of it marked too, and that is in the research rather than being a kind thought. The five year follow-up of ARDS survivors reported that physical and psychological problems developed or carried on in the patients' family caregivers as well as in the patients themselves, out to five years (Herridge and colleagues, 2011). The term itself was written to cover a family member as well as a survivor, which is why you will see it written as PICS-F (Needham and colleagues, 2012; Hiser and colleagues, 2023). In practice that looks like broken sleep, dreading the phone, going over the weeks in the unit again and again, and a steady tiredness that gets dismissed because somebody else was the patient. It has the same route as everything else on this page: tell your own doctor, and ask early what support exists for carers where you live.
References
- National Institute for Health and Care Excellence. Rehabilitation after critical illness in adults. Clinical guideline CG83. Published 25 March 2009. https://www.nice.org.uk/guidance/cg83
- National Institute for Health and Care Excellence. Rehabilitation after critical illness in adults. Quality standard QS158. Published 7 September 2017. https://www.nice.org.uk/guidance/qs158
- NHS. Intensive care. Page last reviewed 24 February 2023. https://www.nhs.uk/conditions/intensive-care/
- Latronico N, Bolton CF. Critical illness polyneuropathy and myopathy: a major cause of muscle weakness and paralysis. Lancet Neurology. 2011;10(10):931-941. https://doi.org/10.1016/S1474-4422(11)70178-8
- Herridge MS, Tansey CM, Matte A, et al. Functional disability 5 years after acute respiratory distress syndrome. New England Journal of Medicine. 2011;364(14):1293-1304. https://doi.org/10.1056/NEJMoa1011802
- Needham DM, Davidson J, Cohen H, et al. Improving long-term outcomes after discharge from intensive care unit: report from a stakeholders' conference. Critical Care Medicine. 2012;40(2):502-509. https://doi.org/10.1097/CCM.0b013e318232da75
- Hiser SL, Fatima A, Ali M, Needham DM. Post-intensive care syndrome (PICS): recent updates. Journal of Intensive Care. 2023;11:23. https://doi.org/10.1186/s40560-023-00670-7
- Geense WW, Zegers M, Peters MAA, et al. New Physical, Mental, and Cognitive Problems 1 Year after ICU Admission: A Prospective Multicenter Study. American Journal of Respiratory and Critical Care Medicine. 2021;203(12):1512-1521. https://doi.org/10.1164/rccm.202009-3381OC
- Hodgson CL, Bailey M, Bellomo R, et al. Early Active Mobilization during Mechanical Ventilation in the ICU. New England Journal of Medicine. 2022;387(19):1747-1758. https://doi.org/10.1056/NEJMoa2209083
- ClinicalTrials.gov. Treatment of Invasively Ventilated Adults With Early Activity and Mobilisation (TEAM III). NCT03133377. https://clinicaltrials.gov/study/NCT03133377
- National Institute for Health and Care Excellence. Delirium: prevention, diagnosis and management in hospital and long-term care. Clinical guideline CG103. Published 28 July 2010, last updated 18 January 2023. https://www.nice.org.uk/guidance/cg103
- National Institute for Health and Care Excellence. Head injury: assessment and early management. NICE guideline NG232. Published 18 May 2023. https://www.nice.org.uk/guidance/ng232
- NHS. Sudden confusion (delirium). Page last reviewed 28 May 2024. https://www.nhs.uk/symptoms/confusion/
- NHS. Symptoms of a stroke. Page last reviewed 12 September 2024. https://www.nhs.uk/conditions/stroke/symptoms/
- NHS. DVT (deep vein thrombosis). Page last reviewed 30 April 2026. https://www.nhs.uk/conditions/deep-vein-thrombosis-dvt/
- NHS. Pneumonia. Page last reviewed 17 July 2026. https://www.nhs.uk/conditions/pneumonia/
- NHS. Sepsis. Page last reviewed 14 May 2026. https://www.nhs.uk/conditions/sepsis/
- NHS. Dysphagia (swallowing problems). Page last reviewed 26 October 2026. https://www.nhs.uk/symptoms/swallowing-problems-dysphagia/
- NHS. Tracheostomy. Page last reviewed 26 January 2024. https://www.nhs.uk/conditions/tracheostomy/
- NHS. Hernia. Page last reviewed 19 May 2026. https://www.nhs.uk/conditions/hernia/
- NHS. Shortness of breath. Page last reviewed 30 January 2024. https://www.nhs.uk/symptoms/shortness-of-breath/
- NHS. Iron deficiency anaemia. Page last reviewed 26 January 2024. https://www.nhs.uk/conditions/iron-deficiency-anaemia/
- NHS. Low blood pressure (hypotension). Page last reviewed 11 July 2023. https://www.nhs.uk/conditions/low-blood-pressure-hypotension/
- NHS. Heart failure. Page last reviewed 26 June 2026. https://www.nhs.uk/conditions/heart-failure/
- NHS. Falls. Page last reviewed 6 March 2025. https://www.nhs.uk/conditions/falls/
- NHS. Fainting. Page last reviewed 17 August 2026. https://www.nhs.uk/symptoms/fainting/
- NHS. Head injury and concussion. Page last reviewed 29 May 2025. https://www.nhs.uk/conditions/head-injury-and-concussion/
- NHS. Help for suicidal thoughts. Page last reviewed 26 April 2024. https://www.nhs.uk/mental-health/feelings-symptoms-behaviours/behaviours/help-for-suicidal-thoughts/
- Sport and Recreation Alliance and UK Government. UK concussion guidelines for non-elite (grassroots) sport. Published 2023, updated November 2024. https://sportandrecreation.org.uk/campaigns-and-policy/concussion/concussion-guidelines-for-grassroots-sport-html-version
Written and checked by the PocketPhysio editorial team. Last updated 2026-11-03.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.