
Part of Running injuries: where they happen and what to do
Achilles pain when running: keep going, cut back or stop?
Warning signs, and when to get help
Can you keep running with Achilles pain?
In most cases, yes, with a limit. The Dutch multidisciplinary guideline on Achilles tendinopathy starts treatment with education, loading advice and progressive calf muscle strengthening for at least 12 weeks, and tells patients with chronic symptoms that waiting and seeing is not expected to produce much in the short term (de Vos and colleagues, 2021). The 2024 US clinical practice guideline says it as an instruction, on moderate evidence: complete rest is not indicated, and you should carry on with your activities within what the pain allows (Chimenti and colleagues, 2024). Silbernagel and colleagues (2020) make the same point from the other direction: complete rest and unloading the tendon can be harmful and can prolong recovery. A tendon that is never asked to work does not get any better at working.
The best evidence for running on it comes from Sweden. Silbernagel and colleagues (2007) took 38 people with Achilles tendinopathy and put them all on the same calf exercise program. Half also kept running and jumping, guided by a simple pain rule; the other half stopped those activities for the first 6 weeks. At every follow-up the two groups had done equally well, and the researchers found no harm from carrying on.
The rule they used is the one to borrow:
- Tendon pain during a run stays at 5 out of 10 or below.
- Any pain after the run is back to its usual level by the next morning.
- Pain and morning stiffness are not creeping up from one week to the next.
Break any one of those and the next run gets shorter or easier. Whether to run at all while the tendon is sore takes that decision on its own, including the three signs that mean stopping rather than trimming, and the pain monitoring model explains the scale and how physios use it across tendon problems.
How to change your running for a sore Achilles
Every push off loads the Achilles, so the question is how much, how fast and how often. Trim in this order.
Many physios take out the hills first, then fast running, strides and track sessions, and bring them back last. Uphill and faster running both ask the calf for a harder push off with each stride. This order is common practice rather than something trials have compared. What is left is easy running on flat ground.
Then look at the gaps between runs. A tendon that is still stiffer than usual from yesterday is a poor candidate for another session today, which is what the next-morning rule checks. Many physios also put a rest day or a cycling day between runs while symptoms are active. That is common practice, not a tested rule.
Shoes are worth a glance. An in-shoe heel lift is a reasonable thing to try while symptoms settle: in a randomized trial of 100 people with midportion Achilles tendinopathy, 12 mm lifts worn in both shoes for 12 weeks came out ahead of an eccentric calf exercise program on the Achilles symptom score, by 9.6 points, which was just short of the 10 points the researchers had set in advance as the smallest difference a patient would notice, and they were careful to say patients may not feel a worthwhile difference between the two (Rabusin and colleagues, 2021). The 2024 US clinical practice guideline lists heel lifts as an option on weak evidence, and describes what they are for in a way worth keeping: temporarily reducing how far the ankle bends up during activity (Chimenti and colleagues, 2024). Treat it as a comfort measure alongside the loading program rather than a replacement for it, and use a lift in both shoes so your legs stay level. The Guy's and St Thomas' leaflet suggests supportive footwear rather than flat shoes, so a sudden switch to flatter or more minimal running shoes is the change to avoid while the tendon is sore.
Does it matter where on the tendon it hurts?
Yes, for the running advice as well as the exercises. Pain in the cord of the tendon a few centimeters above the heel is midportion tendinopathy, which is what the Swedish trial studied and what the 2024 US physical therapy clinical practice guideline states as its own scope (Chimenti and colleagues, 2024). Pain on the heel bone itself was not what either was written about. Pain right at the back of the heel, where the tendon joins the bone, is insertional. Working out which of the two you have comes down to where the tendon is tender, what the back of your shoe does to it, and what the heel bone itself feels like under a finger.
Insertional pain dislikes the ankle bending up a long way, because that presses the tendon into the heel bone. The Kent Community Health NHS leaflet on insertional tendinopathy advises against walking uphill or on slopes and against flat shoes, and the same thinking applies to running. Stick to flat routes, keep a small heel in your running shoes, and skip any calf exercise that lets the heel drop below a step until your physio says otherwise. The Achilles tendinopathy program covers both types in stages.
Morning heel pain that sits under the heel rather than behind it is a different problem; heel pain in the morning sorts the two out.
When is the tendon ready for more running?
Silbernagel and Crossley (2015) proposed a return to sport program for runners and other athletes with midportion tendinopathy, and the readable version of its criteria is in Silbernagel and colleagues (2020). Before running and jumping come back, pain during daily walking should be minimal, 1 to 2 out of 10, and calf strength deficits should be dealt with first. There is a field test alongside it. Hop 20 times on the sore leg: people whose pain goes above 2 out of 10 over those hops will struggle to start running while keeping inside the pain monitoring limits.
Once you pass, start with short, easy runs on flat ground and use the next morning as your guide. The return to running plan gives a walk and run structure, and the calf work keeps going 2 to 3 times a week while you build. Hills, then speed, come back last.
How long before running feels normal again?
Longer than most runners expect. Guy's and St Thomas' tell patients that most people take 6 to 9 months of rehab to reach full, pain-free activity, and Silbernagel and colleagues (2020) note that a rushed return is a common reason the pain comes back. That does not mean 6 months off running. It means 6 months of running less than you want while the calf gets stronger.
Is it a tear?
A rupture announces itself in one moment. People describe a bang or a snap, or a feeling of being kicked in the back of the calf, followed by a leg that will not push off properly (Cambridge University Hospitals). OrthoInfo adds that you may not be able to rise onto your toes on that side. Other muscles can still point the foot down, so some people walk on afterward with only a limp, which is one reason ruptures get missed (Maffulli and colleagues, 2017).
None of the advice on this page applies to that. Stop, keep the weight off the leg and get to urgent care the same day. The Achilles tendon rupture program covers the stages after diagnosis, under your surgical or fracture team. The slower version of the same worry, whether weeks of Achilles pain can end in a snap, is a separate question, and the rupture risk in a tendon that already hurts answers it from the study the figure comes from.
Calf strength that fits around your running
Loading is the part that changes the tendon. The 2024 US clinical practice guideline makes it the first-line treatment on strong evidence, with loads as high as the tendon tolerates, and asks for it at least 3 times a week (Chimenti and colleagues, 2024). Silbernagel and colleagues (2020) rate exercise as having the strongest evidence of any treatment here, report that slow lowering, lifting with lowering and isometric holds have all worked, and put the floor lower, at twice a week. The list below starts gently and gets heavier. The strength training for runners page takes calf work further once the tendon has settled.
Some tendon pain during these is acceptable within the same 5 out of 10 rule, as long as it has settled by the next morning. If your pain is where the tendon joins the heel, keep your heels at floor level for every raise. Keep fingertips on a wall or counter for balance. After an Achilles tendon rupture or repair, follow your surgical or fracture team's plan instead, because single leg and weighted heel raises come at set stages of that rehab. If you have high blood pressure, breathe steadily through every hold and never hold your breath.
Exercises that can help
These follow the order most tendon programs use, from a hold to raises on two feet, then one, then added weight. Many programs start with wall press holds of 10 to 30 seconds repeated 3 to 5 times, 2 to 3 sets of 10 to 15 calf raises on both feet, 2 to 3 sets of 8 to 15 on each leg for the bent knee and single leg raises, and 3 sets of 8 to 12 for weighted raises 2 or 3 times a week. Read how often to do each one on its own page. Your physio will adjust this.
 Isometric calf press against a wall
 Calf raises
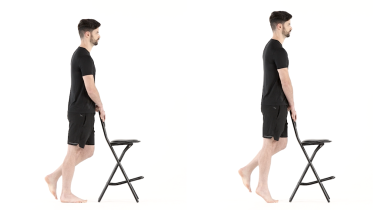 Bent-knee calf raise
 Single leg heel raise
 Weighted calf raise
When to see a physio (physical therapist)
Book an assessment if the tendon is getting worse despite trimming your running, if it hurts with ordinary walking, or if it has not improved after a few weeks. Before you book, it is worth checking the usual reasons Achilles pain stops improving, because the commonest ones are the dose, the consistency and the kind of pain being treated, and two of those you can answer yourself. A physio will pin down whether it is midportion or insertional, compare calf strength and endurance on each leg, and set both a loading dose and a running dose you can manage this week.
Book sooner if you have had a previous Achilles problem on either side, or have recently taken a fluoroquinolone antibiotic. The running injuries hub covers the other common problems by body area, and the warning signs below say how quickly to act.
Related exercise programs
Warning signs
Get help now, day or night
- Your tendon pain or swelling started while you were taking a fluoroquinolone antibiotic, such as ciprofloxacin or levofloxacin, or in the months after a course. Contact your doctor straight away. The UK medicines regulator (MHRA) advises stopping the antibiotic at the first sign of tendon pain or swelling and talking to your doctor. Hold off the calf exercises until you have been checked.
Get help today
- Same day: a sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
- Same day: a calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Same day: the pain started with a fall or a blow to the back of the ankle, and there is bruising or you cannot put weight on the foot. Get it checked the same day.
- Same day: the tendon or heel is hot, red and swollen, or you have a fever or feel unwell. Get medical help the same day, and go to an emergency department if you feel very unwell. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: the pain is there at night or at rest as well as with activity and keeps getting worse. If you are being treated for cancer now, contact your cancer team the same day.
Book an appointment
- Within a day or two: the pain is there at night or at rest as well as with activity and keeps getting worse. If you have had cancer, now or in the past, or are losing weight without trying, see your doctor sooner, within a day or two, and mention it. This applies even if the pain is not getting worse.
- Within a few days: the pain is there at night or at rest as well as with activity and keeps getting worse. See your doctor within a few days.
- Within a week or two: your heel or Achilles pain comes with back pain and stiffness that is worse in the morning and at night, or with painful, swollen joints elsewhere, or both heels became painful without an obvious reason. The same applies if you also have psoriasis, Crohn's disease or ulcerative colitis, or have had a red, painful, inflamed eye (iritis). This is not an emergency, but see your doctor in the next week or two, as it can be a sign of an inflammatory arthritis such as ankylosing spondylitis.
- Within a week or two: you have numbness, tingling, burning or loss of feeling in the foot, often along the outer edge. Book an assessment with a doctor or physio in the next week or two. If it came on over hours or days, started after an injury, is spreading, or comes with weakness in the foot, get medical advice the same day.
Common questions
Can I keep running with Achilles tendonitis?
Most people can keep some running. The Dutch multidisciplinary guideline tells patients with chronic Achilles tendinopathy that little or no improvement is expected in the short term from a wait-and-see approach (de Vos and colleagues, 2021), Silbernagel and colleagues (2020) warn that complete rest and unloading the tendon can be harmful and prolong recovery, and in the Swedish trial runners who carried on within a pain limit did as well as those who stopped (Silbernagel and colleagues, 2007). The limit was tendon pain of 5 out of 10 or less during and after running, gone by the next morning, and not building week to week. If the tendon is clearly stiffer the morning after, the run was too long or too fast. Your physio will adjust this.
Should I run hills with Achilles pain?
Not while it is sore. Many physios take hills out of your running first, ahead of speed work, and bring them back last. If the pain is right at the back of the heel (insertional), the Kent Community Health NHS leaflet advises against walking uphill or on slopes at all for now, because bending the ankle up presses the tendon into the heel bone. Flat routes, easy pace and the next-morning check are the plan until the tendon settles.
When can I run again after Achilles tendinopathy?
When everyday walking barely hurts and hopping is tolerable. Silbernagel and colleagues (2020) give it as a rule of thumb: before running and jumping come back, pain during daily walking should be minimal, 1 to 2 out of 10, and someone whose pain goes above 2 out of 10 over 20 hops on the sore leg will struggle to start running while staying inside the pain monitoring limits. They treat calf strength deficits as something to close first. Start with short, easy runs on flat ground and build from there.
How long does Achilles pain take to go away?
Months, more often than weeks. In the Guy's and St Thomas' NHS leaflet, most people take 6 to 9 months of rehab to get back to full activity without pain, and Silbernagel and colleagues (2020) note that some take a year or longer. Running does not have to stop for all of that time, but the tendon needs patience.
References
- Silbernagel KG, Thomee R, Eriksson BI, Karlsson J. Continued sports activity, using a pain-monitoring model, during rehabilitation in patients with Achilles tendinopathy: a randomized controlled study. American Journal of Sports Medicine. 2007;35(6):897-906. https://doi.org/10.1177/0363546506298279
- Chimenti RL, Neville C, Houck J, Cuddeford T, Carreira D, Martin RL. Achilles Pain, Stiffness, and Muscle Power Deficits: Midportion Achilles Tendinopathy Revision - 2024. Journal of Orthopaedic and Sports Physical Therapy. 2024;54(12):CPG1-CPG32. https://doi.org/10.2519/jospt.2024.0302
- de Vos RJ, van der Vlist AC, Zwerver J, Meuffels DE, Smithuis F, van Ingen R, van der Giesen F, Visser E, Balemans A, Pols M, Veen N, den Ouden M, Weir A. Dutch multidisciplinary guideline on Achilles tendinopathy. British Journal of Sports Medicine. 2021;55(20):1125-1134. https://doi.org/10.1136/bjsports-2020-103867
- Rabusin CL, Menz HB, McClelland JA, Evans AM, Malliaras P, Docking SI, Landorf KB, Gerrard JM, Munteanu SE. Efficacy of heel lifts versus calf muscle eccentric exercise for mid-portion Achilles tendinopathy (HEALTHY): a randomised trial. British Journal of Sports Medicine. 2021;55(9):486-492. https://doi.org/10.1136/bjsports-2019-101776
- Rabusin CL, Menz HB, McClelland JA, Evans AM, Landorf KB, Malliaras P, Docking SI, Munteanu SE. Efficacy of heel lifts versus calf muscle eccentric exercise for mid-portion Achilles tendinopathy (the HEALTHY trial): study protocol for a randomised trial. Journal of Foot and Ankle Research. 2019;12:20. https://doi.org/10.1186/s13047-019-0325-2
- Silbernagel KG, Crossley KM. A Proposed Return-to-Sport Program for Patients With Midportion Achilles Tendinopathy: Rationale and Implementation. Journal of Orthopaedic and Sports Physical Therapy. 2015;45(11):876-886. https://doi.org/10.2519/jospt.2015.5885
- Silbernagel KG, Hanlon S, Sprague A. Current Clinical Concepts: Conservative Management of Achilles Tendinopathy. Journal of Athletic Training. 2020;55(5):438-447. https://doi.org/10.4085/1062-6050-356-19
- Guy's and St Thomas' NHS Foundation Trust. Achilles tendinopathy. Patient information, resource number 4609/VER3. Last reviewed October 2024. https://www.guysandstthomas.nhs.uk/health-information/achilles-tendinopathy
- Kent Community Health NHS Foundation Trust. Achilles insertional tendinopathy. Patient leaflet 01271. Published 2 December 2024. https://www.kentcht.nhs.uk/leaflet/achilles-insertional-tendinopathy/
- American Academy of Orthopaedic Surgeons. Achilles tendon rupture (tear). OrthoInfo. https://www.orthoinfo.org/en/diseases--conditions/achilles-tendon-rupture-tear/
- Cambridge University Hospitals NHS Foundation Trust. Achilles tendon rupture. Patient information. Approved 14 January 2025. https://www.cuh.nhs.uk/patient-information/achilles-tendon-rupture/
- Maffulli N, Via AG, Oliva F. Chronic Achilles tendon rupture. Open Orthopaedics Journal. 2017;11:660-669. https://doi.org/10.2174/1874325001711010660
- NHS. Tendonitis. Page last reviewed 9 June 2023. https://www.nhs.uk/conditions/tendonitis/
- Medicines and Healthcare products Regulatory Agency. Fluoroquinolone antibiotics: must now only be prescribed when other commonly recommended antibiotics are inappropriate. Drug Safety Update. 22 January 2024. https://www.gov.uk/drug-safety-update/fluoroquinolone-antibiotics-must-now-only-be-prescribed-when-other-commonly-recommended-antibiotics-are-inappropriate
- NHS. Deep vein thrombosis (DVT). Page last reviewed 30 April 2026. https://www.nhs.uk/conditions/deep-vein-thrombosis-dvt/
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-16.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.