
Ozempic muscle loss: exercise to protect your muscle
Warning signs, and when to get help
Does Ozempic cause muscle loss?
Not by acting on muscle, as far as anyone has shown. What these medicines do is cut appetite, which produces an energy deficit that is both large and fast, and a body in that state draws on more than fat. The same thing turns up in dieting trials where no medicine is involved at all, which is where most of the evidence on this actually comes from. Our topic page on why muscle loss happens goes through that research in detail.
So the question worth asking is not whether the medicine is doing something to your muscle. It is whether anything in your week is telling your body that the muscle is still needed. For most people losing weight quickly, nothing is.
What the trials measured, and what they did not
The closest look at this in people actually taking one of these medicines is the SEMALEAN study. It enrolled 115 adults with obesity and followed 106 of them for a year. Mean body mass index was 46.3, about seven in ten of them were women, and all were treated with semaglutide 2.4 mg and scanned at the start, at 7 months and at 12 months. Lean mass fell by roughly 3 kg (6.6 lb) by month 7 and then stopped falling, while fat mass kept going down, 14 percent at 7 months and 18 percent at a year (Alissou 2026).
Then the same study measured something a scan cannot see. Average grip strength rose by 4.5 kg (10 lb) over the twelve months, and the proportion of the group meeting the criteria for sarcopenic obesity dropped from 49 percent to 33 percent. There was no control group, so none of it proves what the medicine caused. What it does show is that a number going down on a scan and a person getting weaker are two different events.
Read every figure on this subject as mass, not strength, and remember what lean mass includes: organs, body water and bone, as well as the muscle fiber people are worried about. There is one more limit worth saying plainly. No trial has yet tested a resistance training program in people taking semaglutide or tirzepatide. The review that argues hardest for one is a call for that trial rather than the trial itself (Locatelli 2024).
Nothing here is advice about your medicine
It is worth being blunt about this before you start anything. This page has nothing to say about whether to start one of these medicines, which one, what dose, how long to stay on it, or whether to space it out or pause it to hold on to muscle. Those questions belong with the prescriber who knows your history and with the pharmacist who dispenses it. Never stop or change a prescribed medicine on your own.
Exercise is not an alternative to a prescribed treatment, and nothing on this page is offered as one. Which medicines in this class are licensed, for whom, and under which name differs between the USA, the UK, Canada, Australia and New Zealand, so that question goes to your own prescriber too.
Pregnancy is the one prescribing point worth naming here, because of who reads a page like this. The NHS advises telling your doctor if you are pregnant or become pregnant while using semaglutide, because it is not used in pregnancy, and planning it with your prescriber in advance if you are hoping to conceive. Raise it with them rather than acting on it yourself.
What protects the muscle while the weight comes off
Load is the lever with evidence behind it, and the clearest numbers come from dieting research rather than from medicine trials. Sardeli and colleagues pooled six randomized trials of older adults with obesity on calorie restriction. Resistance training three times a week, for 12 to 24 weeks, prevented 93.5 percent of the lean body mass that the diet alone cost, about 0.8 kg (1.8 lb), and the weight and fat still came off as fast (Sardeli 2018). Those were older adults on a reduced-calorie diet, not adults on a GLP-1 medicine, and what the two situations share is the energy deficit.
Bone travels down with the muscle, and it gets talked about far less. In a year-long randomized trial of 195 adults who had already lost weight on a low-calorie diet, hip and spine density fell further on liraglutide alone than in the group that exercised, while the group doing both ended no different from placebo at either site (Jensen 2024). That trial used liraglutide 3.0 mg rather than the newer medicines, and in the parent trial the combination of exercise and medicine cut body fat percentage about twice as far as either on its own (Lundgren 2021). If you have already been told your bone density is low, raise this with your prescriber and your physio before the weight starts moving, and work from the osteoporosis program.
Protein is the other half of this, and it is not ours to set. There is no established daily target for people on these medicines, so you will find no number for it here; that is a dietitian's job, and our protein and exercise basics page explains the general picture without prescribing one.
How much training, how often, and how hard?
The frequency is not invented for this situation. The WHO guidelines ask adults for muscle-strengthening activity at moderate or greater intensity, working all the major muscle groups, on 2 or more days a week (Bull 2020). Two sessions is the floor worth defending, and three is better if the week allows it.
National guidance has now caught up with the question. The UK Chief Medical Officers' physical activity guidelines, updated in July 2026, say that when these medicines are taken both fat and muscle decrease, that the weight management versions are currently licensed only to be used alongside physical activity and other behavioral changes, and that muscle strengthening activity is likely to be of particular importance for holding on to muscle and preventing weight regain in people taking them or who have recently taken them. The same document says the evidence on that is still emerging, which is the honest state of it.
For the effort, finish each set with about 2 repetitions in reserve, meaning you could have done two more without the movement changing shape. Many programs sit at 2 to 3 sets of 8 to 12 repetitions for each movement, with a rest day between sessions. Your physio will adjust this, and each exercise page carries its own starting dose and its own stop signs.
How to use this program
Start at stage 1 in the week your medicine starts, if you can. Muscle responds to being asked, and the ask is easiest to establish before appetite and energy drop.
Pick the stage that matches you today rather than the one that matches your ambition. Move up when the current stage feels steady and you are recovering between sessions. The strength plan for 2 to 3 times a week shows how the sessions fit into a week, and exercises at home covers the equipment-free versions.
Breathe steadily through every repetition and never hold your breath, particularly if you have high blood pressure. With a heart condition, high blood pressure that is not under control, or a long gap since you last exercised, check with your doctor before you start. If you have fallen in the past year or feel unsteady, keep a hand on a kitchen counter for the whole of the standing work and ask your doctor or physio about a falls check.
If you have had a hip or knee replacement, get the go-ahead from your surgeon or physio before you try goblet squats and the deeper squats. A deep squat bends the hip well past a right angle, and many surgeons ask you to avoid that for the first months after some operations. After hip, knee or back surgery, bridges, step ups and single leg work start at the point your surgical team's protocol allows.
Run the band through your fingers and feel for nicks or tears before every session. If you have had shoulder surgery, or the shoulder has dislocated or feels loose, ask your physio before the overhead press and the band work, because hands up beside the head is the position an unstable shoulder objects to first. After an Achilles tendon repair or ankle surgery, calf raises come in at the stage your surgeon's protocol sets.
Stop the session for chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause. Sharp pain inside a repetition means stop that exercise for the day rather than push one more out.
The exercise program
Stage 1: Start the week your medicine starts
Five movements, a chair and a light band. This is the layer to get going in the first weeks, when appetite and energy are often at their lowest and a long session is the quickest way to stop altogether. Many people begin at 2 to 3 sets of 8 to 12, on 2 or 3 days of the week, with a rest day in between. Take the numbers from each exercise page rather than from this paragraph. Your physio will adjust this.
 Sit to stand
 Chair squat
 Wall push-ups
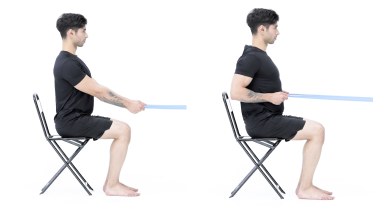 Seated row with band
 Calf raises
Stage 2: Load the big movements
When stage 1 feels steady and you can finish a set with about 2 repetitions still in reserve, usually after two to four weeks. A goblet squat can start with nothing in your hands, and the shoulder press with a 500 ml bottle of water in each hand, about 0.5 kg (1.1 lb). Add weight only after the pattern looks the same on the last repetition as on the first.
 Goblet squat
 Split squat
 Incline push-ups
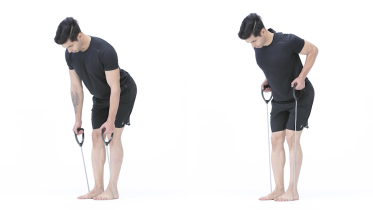 Bent-over band row
 Seated dumbbell shoulder press
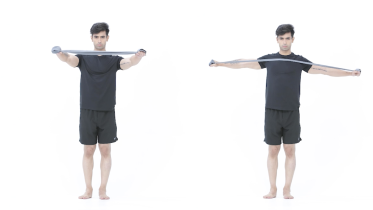 Band pull-apart
Stage 3: Keep adding load all the way down
For later in the weight loss, when stage 2 is comfortable. Single leg work and stairs are here because they are the jobs that go first when the legs get lighter and weaker at the same time. Keep a counter or a rail within reach for the single leg exercises, and go back a stage for a week rather than skipping sessions if a chest infection, a dose increase or a bad run of nausea knocks you off.
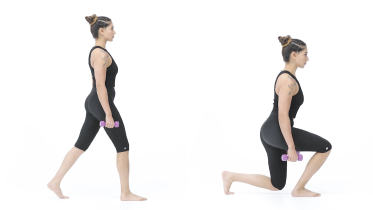 Dumbbell split squat
 Single leg deadlift
 Step up
 Push-ups
 Lat pulldown
 Stair climbing
Training around nausea, a small appetite and low energy
The first week or two after a dose increase is where most people quietly stop. Shrink the session instead. One set of each movement, done slowly, keeps the habit and most of the stimulus, and a 10 minute version you actually do beats a 40 minute version you skip.
Eat something small before you train if you can, train at the time of day you feel least queasy, and keep fluids going through the session. Dehydration is the one to watch rather than to push through, and the warning signs at the foot of this page set out when it becomes a same-day call to your prescriber.
Muscle soreness for a day or two after a new movement is ordinary. Feeling washed out for three days is a signal that the session was too big for the amount you are currently eating, so take the load down a step and build again.
Older adults on these medicines
Age changes the stakes rather than the plan. Starting with less muscle means a given percentage loss costs more function, and the jobs at risk are the ones that keep people independent: getting off a low chair, carrying shopping, managing stairs. Our page on older adults on GLP-1 medicines covers the detail, and if you have been told you have low muscle mass or strength for your age, the sarcopenia program is the matching page. Strength training for older adults is the general graded build-up over 65.
Measure something now so you have a comparison later. The 30-second chair stand test takes a minute and gives you a number you can repeat every few months, which is more useful than any home scan.
What happens when you stop
Appetite usually comes back, and weight often follows. The training is what decides what the regained weight is made of, which is the argument for treating the program as a permanent part of the week rather than something that runs alongside the prescription. Our page on after stopping the medicine goes through it, and the decision about stopping stays with the prescriber.
When to see a physio, a dietitian or your prescriber
See a physio if you want the starting loads set rather than guessed, if an old back, hip, knee or shoulder problem starts complaining once you add weight, or if you want your everyday function measured. Go sooner if strength is visibly going backwards, if you have been told you have low bone density, or if you have broken a bone from a minor fall.
A dietitian owns the eating side, including protein, and is the right referral if appetite has fallen so far that meals have become difficult. Everything about the medicine, including side effects, dose changes and how long to continue, goes to the prescriber. Any warning sign below is a reason to stop and get checked rather than to push on.
For physiotherapists
This page is a patient-facing framework, not a plan. The useful measures here are function and strength rather than body composition: grip dynamometry, the 30-second chair stand, gait speed, and the loads and repetitions the patient logs week to week. Lean mass on DXA or bioimpedance moves for reasons that have nothing to do with muscle protein, and SEMALEAN is the cleanest illustration of mass and strength parting company in this population (Alissou 2026).
Resistance training during a large energy deficit is the intervention with transferable evidence, carried over from calorie restriction trials in older adults rather than demonstrated in this group (Sardeli 2018; Locatelli 2024). And bone deserves a question at the first appointment, because the one randomized trial measuring it found density falling further on the medicine alone than in the exercising groups (Jensen 2024).
Warning signs
Get emergency help now
- Emergency: if chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
- Emergency: any sign of a stroke, even if it goes away. That means a face that droops on one side, an arm you cannot lift or keep up, slurred or muddled speech, weakness or numbness on one side of your body or face, sudden blurred vision, double vision or loss of sight, trouble swallowing, sudden dizziness with unsteadiness or falling over, a sudden severe headache, or a sudden fall where your legs give way but you do not black out (a drop attack). Call emergency services straight away.
- Emergency: sudden severe stomach pain together with pain spreading to your back, bloating that will not settle, a fast heartbeat, trouble breathing, or skin around your belly button, waist or upper outer thigh that looks blue or bruised (this can be harder to see on brown or black skin). Call emergency services or go to an emergency department, and do not drive yourself. If that sudden severe pain does not go away or keeps coming back, or comes with a high temperature or chills, without any of the signs above, get an urgent medical appointment or call your health service's urgent advice line the same day.
- Emergency: sudden, severe pain in your lower back or tummy that is not like your usual back pain, if you have been told you have a swelling of the main blood vessel in your tummy (abdominal aortic aneurysm), you are over 60, you smoke or used to smoke, or you have high blood pressure. The same applies if sudden, severe back or tummy pain comes with feeling faint or passing out, pale, sweaty or clammy skin, a racing heartbeat or being short of breath. Call emergency services straight away. This can be a sign of an aneurysm bursting, which needs treatment in hospital at once.
Get help today
- Same day: you feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services.
- Same day: dizziness or feeling faint during or after exercise, without any of the emergency signs above. Stop the exercises and get medical advice the same day. If you faint, it does not settle within a few minutes of sitting still, or you cannot stand or walk steadily, call emergency services.
- Same day: you blacked out or fainted, even for a moment. Get medical advice the same day. Call emergency services instead if the person is not breathing, cannot be woken within 1 minute, has not fully recovered or has trouble speaking or moving, has chest pain or a pounding, fluttering or irregular heartbeat, fainted while exercising or lying down, is shaking or jerking, or was badly hurt.
- Same day: shakiness, sweating, tingling lips, hunger, a pounding heartbeat, blurred vision, feeling weak or confusion during or after a session, if you take insulin or other diabetes medicines. These can be signs of low blood sugar, and the risk of it is higher when insulin or a sulfonylurea is taken alongside one of these medicines. Treat it the way your diabetes team has told you, then contact them or your prescriber the same day. If someone cannot be woken, cannot swallow safely or has a seizure, call emergency services.
- Same day: you cannot keep fluids down, you are being sick or have diarrhea that will not settle, you are peeing less than usual or your pee is dark yellow and strong smelling, you feel unusually tired, you feel dizzy when you stand up, or you are breathing quickly or your heart is racing. Contact your prescriber or get medical advice the same day, as these can be signs of dehydration. Call emergency services or go to an emergency department if your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), your skin feels cold, you are breathing fast or finding it hard to breathe, you are confused, or you are unusually sleepy or hard to wake.
- Same day: a calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Same day: back pain after a minor fall or strain if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time. Get medical advice the same day.
- Same day: losing weight without trying, for example weight coming off faster than you and your prescriber expected, or weight that keeps coming off after you no longer want it to. If you are being treated for cancer now, contact your cancer team the same day.
- Same day: losing weight without trying, for example weight coming off faster than you and your prescriber expected, or weight that keeps coming off after you no longer want it to. If you also have new back or neck pain, get medical advice the same day.
Book an appointment
- Within a day or two: losing weight without trying, for example weight coming off faster than you and your prescriber expected, or weight that keeps coming off after you no longer want it to. See your doctor within a day or two and mention it. Tell your prescriber as well, and do not change a medicine on your own.
- Within a few days: strength that is clearly going backwards, for example you need your hands to get out of a chair when you did not before, your grip gives out on jars and door handles, or you are stumbling on stairs. See a doctor or physio within a few days so someone can measure it rather than guess. Tell your prescriber as well, and do not change a medicine on your own.
Common questions
How much of the weight lost on Ozempic is muscle?
Nobody can give you a personal figure, and the numbers in circulation describe lean mass rather than muscle. In the SEMALEAN study, 106 adults with obesity on semaglutide 2.4 mg lost about 3 kg (6.6 lb) of lean mass over the first 7 months and then held steady, while fat mass carried on falling (Alissou 2026). Lean mass on a scan takes in organs, body water and bone as well as muscle fiber, so the share of your own loss that is muscle is not something a scale or a home body composition monitor can tell you.
Will exercise stop the muscle loss completely?
The honest answer is that no trial has tested a strength program in people taking semaglutide or tirzepatide, so the figure quoted for this comes from dieting research instead. In six trials of older adults with obesity on calorie restriction, resistance training three times a week held on to 93.5 percent of the lean body mass that dieting alone cost, and the fat loss was no slower for it (Sardeli 2018). That is a good reason to lift while the weight comes off, and not a promise about your own scan.
Should I eat more protein while taking one of these medicines?
Protein matters while you are in a large energy deficit, and there is no established daily target for people on these medicines, so this page gives no number. Appetite usually falls across the board, which means protein tends to fall with everything else. That is a conversation for a dietitian or your prescriber, who can set an amount against your kidney function, your other conditions and what you can actually face eating. Our page on protein and exercise basics covers the general ground.
Can I exercise instead of taking the medicine?
That is not a choice this page can help you make, and it is not one to make alone. Whether to start, continue, pause or stop a prescribed medicine depends on your health, your history and what the treatment is for, so it belongs with the prescriber who holds all three. Never stop or change a prescribed medicine on your own. What exercise does here is change what the weight loss is made of, which is a different job from the one the medicine was prescribed to do.
What if I feel too sick or too tired to train?
Shrink the session rather than cancel it. Keeping the same movements at one set each, done slowly, holds far more than a week off does, and nausea is usually worst in the days after a dose increase and then settles. If you cannot keep fluids down, are being sick or have diarrhea that will not settle, that is a same-day call to your prescriber rather than a training question, and the warning signs on this page say what to watch for.
References
- Alissou M, Demangeat T, Folope V, et al. Impact of semaglutide on fat mass, lean mass and muscle function in patients with obesity: the SEMALEAN study. Diabetes, Obesity and Metabolism. 2026;28(1):112-121. doi:10.1111/dom.70141
- Sardeli AV, Komatsu TR, Mori MA, Gaspari AF, Chacon-Mikahil MPT. Resistance training prevents muscle loss induced by caloric restriction in obese elderly individuals: a systematic review and meta-analysis. Nutrients. 2018;10(4):423. doi:10.3390/nu10040423
- Jensen SBK, Sorensen V, Sandsdal RM, et al. Bone health after exercise alone, GLP-1 receptor agonist treatment, or combination treatment: a secondary analysis of a randomized clinical trial. JAMA Network Open. 2024;7(6):e2416775. doi:10.1001/jamanetworkopen.2024.16775
- Lundgren JR, Janus C, Jensen SBK, et al. Healthy weight loss maintenance with exercise, liraglutide, or both combined. New England Journal of Medicine. 2021;384:1719-1730. doi:10.1056/NEJMoa2028198
- Locatelli JC, Costa JG, Haynes A, et al. Incretin-based weight loss pharmacotherapy: can resistance exercise optimize changes in body composition? Diabetes Care. 2024;47(10):1718-1730. doi:10.2337/dci23-0100
- Bull FC, Al-Ansari SS, Biddle S, et al. World Health Organization 2020 guidelines on physical activity and sedentary behaviour. British Journal of Sports Medicine. 2020;54(24):1451-1462. doi:10.1136/bjsports-2020-102955
- UK Chief Medical Officers. UK Chief Medical Officers' physical activity guidelines. Department of Health and Social Care. 2019, updated 10 July 2026. https://www.gov.uk/government/publications/physical-activity-guidelines-uk-chief-medical-officers-report
- NHS. Semaglutide: a medicine to manage type 2 diabetes or treat obesity. Page last reviewed 15 May 2026. https://www.nhs.uk/medicines/semaglutide/
- NHS. Acute pancreatitis. Page last reviewed 11 March 2026. https://www.nhs.uk/conditions/acute-pancreatitis/
- NHS. Low blood sugar (hypoglycaemia). Page last reviewed 3 August 2023. https://www.nhs.uk/conditions/low-blood-sugar-hypoglycaemia/
- NHS. Dehydration. Page last reviewed 1 May 2026. https://www.nhs.uk/conditions/dehydration/
- NHS. Unintentional weight loss. https://www.nhs.uk/symptoms/unintentional-weight-loss/
- NHS. Deep vein thrombosis (DVT). Page last reviewed 30 April 2026. https://www.nhs.uk/conditions/deep-vein-thrombosis-dvt/
- NHS. Symptoms of a stroke. https://www.nhs.uk/conditions/stroke/symptoms/
- NHS. Fainting. Page last reviewed 17 August 2026. https://www.nhs.uk/symptoms/fainting/
- NHS. Osteoporosis. https://www.nhs.uk/conditions/osteoporosis/
- NHS. Abdominal aortic aneurysm. https://www.nhs.uk/conditions/abdominal-aortic-aneurysm/
- National Institute for Health and Care Excellence. Abdominal aortic aneurysm: diagnosis and management (NG156). 2020. https://www.nice.org.uk/guidance/ng156
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-24.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.