
Deconditioning after illness: what it means and how to rebuild
Warning signs, and when to get help
What does deconditioning after illness mean?
Deconditioning is the word clinicians use for the physical capacity you lose while you are doing very little. Strength, stamina, balance and the habit of a movement all fade when nothing asks for them, and a long illness at home removes most of the asking without ever looking like bed rest.
The word is a description, not a disease, and that is where it gets slippery. Welch and colleagues, in a 2024 review in Age and Ageing, call hospital-associated deconditioning a broad term for a decline in any function of the body that follows a hospital stay, with the highest risk in older people and particularly in those living with frailty. Their caution about the term is the part to carry away. They say it is descriptive, that it probably leads to the organ dysfunction that goes with it being played down, and that it implies some ease of reversibility.
That matters because the word is reassuring in a way the situation may not be. Being told you are out of condition sounds like a problem that will solve itself with effort, and sometimes the organs involved have taken a real knock. Welch and colleagues also describe a cognitive side, which they define by delayed mental processing and place on a spectrum with full delirium at the far end, so count slower thinking as part of the picture. They are honest in both directions too: some of it may be reversible with early help, and the long-term effects can be severe.
One point of housekeeping about that review. It was written about deconditioning that follows a hospital stay, and most readers of this page were never admitted. The word is used the same way for both and the caution about the word travels, but the risk groups and the setting in that paper belong to hospital patients, not to someone who spent eight weeks on the sofa after a viral illness.
The other thing to know about the word is what it is doing in your notes. Deconditioning is a label of exclusion. It fits once somebody has looked for the treatable reasons you are weak and tired and not found one, and it fits badly when nobody has looked.
Why does a long illness take strength so fast?
Muscle keeps what it is asked for, and nothing else. Two weeks of flu takes out the stairs, the walk to the store, the standing up and sitting down twenty times a day, and the hour on your feet in the kitchen, and none of those comes back on its own when the fever does.
How fast the losing side goes has been measured properly in bed rest, and the figures are set out on our page on regaining strength after a hospital stay, so this page does not repeat them. The causes of muscle loss beyond simple inactivity, including what illness itself does, sit on the sarcopenia page.
What makes a long illness at home different is not the biology. It is that nothing marks the before and the after. There is no admission, no discharge letter, no day on which somebody said you had lost ground, so the weakness has no edges and gets read as the illness still being present. Plenty of people spend an extra month waiting to feel well enough to start, when what they are feeling is the loss of condition, not the infection.
Nobody has measured you either. A person coming out of hospital usually has a letter, a physio or at least a number to ring. After a long illness at home there is often nothing: no baseline, no limits, nobody who has cleared you for anything. That is the gap this page is written for, and it is the reason the next section comes before the program and not after it.
Before you start: what has to be checked first
Have the treatable causes looked for before you start building, not after the building fails. That is the order NICE sets in its UK guideline on the long-term effects of COVID-19 (NG188), which asks clinicians to see that any symptoms which could affect a person's ability to start rehabilitation safely have been investigated first, and to use a team approach covering the physical, psychological and psychiatric sides. It also asks for a personalized plan, written down, that says how symptoms will be managed and monitored, and that takes account of symptoms going up and down.
That recommendation was written for people living with the long-term effects of COVID-19. It is quoted here for the sequence it sets. The illness it was written about is beside the point, because that sequence is the same whatever left you weak.
NG188 is a UK document and names UK services. If you are in the USA, Canada, Australia, New Zealand or Europe, the request is the same and only the door is different: ask your doctor, or your physical therapist (physiotherapist), for an appointment about being weak and tired weeks after an illness, and say that you want the treatable causes looked at before you start a program. Taking a written list of what has changed and when does more for that appointment than describing how you feel.
In the meantime, stage 1 of the program below is chair work at a level below what an ordinary day already asks of you, and it does not wait for anybody, with two exceptions. If activity leaves you worse hours or days later, stage 1 is not your starting point either, and the section below headed 'If activity makes you worse hours or days later' explains why. And if you have had an operation on your chest, your tummy, your groin or your spine in the past few months, two of the five exercises in stage 1 are not neutral for you, so read 'If your deconditioning started with an operation' below before you begin even the seated work. Standing exercise and loaded work does wait. So does anything at all if one of the warning signs at the foot of this page fits you, because those are reasons to be seen rather than reasons to train.
Is it deconditioning, or something that needs treating?
This is the question the label is supposed to answer last, and too often answers first. A long illness leaves several reasons for being weak and tired that a blood test or a short examination can find, and the list a doctor usually works through runs roughly like this.
- Anemia, which is treatable and which shows up as tiredness, breathlessness and paler skin that build week by week instead of settling.
- A thyroid that has become underactive, and blood sugar.
- A heart or lung cause, which is why breathlessness on small effort sits in the warning list below and not in this one.
- An infection that never fully cleared.
- Low mood, which produces real physical fatigue and is treated in its own right.
- Weight coming off without your meaning it to, which has its own lines at the foot of this page.
- Medicines, including steroid tablets, which can leave muscle weaker and blood pressure lower than you expect.
The medicines one is worth a sentence of its own. People come out of a long illness on a different list from the one they went in with, and the effect on strength, balance and blood pressure is easy to put down to the illness. Never stop or change a prescribed medicine on your own. Take the whole list to your doctor or a pharmacist instead, and say that you have become weak, dizzy or muddled since the illness.
Dizziness or a racing heart when you stand up belongs here too. It is a common experience after weeks of lying and sitting, it is also how several treatable things present, and the way to settle it is a blood pressure and heart rate taken lying and then standing rather than a decision made at home. Until that has happened, it is a reason to be checked and not a reason to push through.
The test that separates loss of condition from a symptom is the direction of travel. Loss of condition is slowly better on a day when you have eaten and slept. Anything that is worse this week than last week, arrived suddenly, or has brought something new with it is a symptom, and it belongs with a doctor before it belongs with an exercise program. Every one of those is written out with its own route and timing in the warning signs at the foot of this page, and that list is worth a read before you start, while nothing has happened yet.
If activity makes you worse hours or days later, this page is not your starting point
Read this before the program. If activity reliably leaves you worse hours or days afterwards, out of proportion to what you did, and the recovery drags on for hours, days or longer, then the program below is the wrong treatment for you and a different kind of care is the right one.
That delayed pattern has a name, post-exertional malaise, also called post-exertional symptom exacerbation. NICE's UK guideline on ME/CFS (NG206) describes it as a worsening of symptoms that can follow minimal physical, mental, emotional or social activity, or activity that you used to manage without trouble. Its own account is that symptoms typically worsen 12 to 48 hours after the activity and last for days or even weeks, and that it sometimes tips a person into a relapse. The delay is the part that fools people, because a session that felt acceptable at the time gets cleared as safe before the bill arrives.
So the screening question is this one, and it is worth answering slowly. Does activity reliably leave you worse hours or days later, most often somewhere between 12 and 48 hours, out of proportion to what you did, with a recovery that takes hours, days or longer? If the answer is yes, do not start the program below. NICE's own criterion puts the worsening as often delayed by hours or days, and the recovery as lasting hours, days, weeks or longer, so a crash later the same evening that costs you the rest of the day counts too, and the 12 to 48 hour window is where it usually lands rather than a cut-off you have to meet.
Three things make people answer no to that question when the honest answer is yes. The first is the comparison buried in 'out of proportion': it means out of proportion to the activity, not to how unfit you have been told you are, so a shower or a short walk costing you the next two days counts however unfit you feel. The second is what counts as activity. NICE's description covers minimal physical, mental, emotional or social activity, so a phone call, a hard conversation or an hour of concentration can be the thing that sets it off, and a reader thinking only about exercise will miss her own pattern. The third is that it does not have to happen every single time for the pattern to be real.
If you cannot tell which of these two you are, do not settle it by trying: hold to the level of activity you already manage without a delayed crash, write down for a week what you did and how the next two days went, and take that to your doctor or physio. A week of notes answers this better than a week of guessing.
NICE lists four symptoms that have to be present together before ME/CFS is suspected, and they are a clinician's to assess, not yours to score. Debilitating fatigue that activity makes worse, that is not explained by too much exertion and that rest does not relieve much. Post-exertional malaise as described above, often delayed by hours or days, out of proportion to the activity, with a prolonged recovery. Sleep that does not refresh, or sleep that is disturbed. Difficulty thinking, which people describe as fog, slowness or losing words.
NICE is specific about what not to be given, and this page's own title is in the firing line. NG206 says not to offer any program that uses fixed incremental increases, naming graded exercise therapy as the example. It says not to offer generalized programs, including programs developed for healthy people or for people with other illnesses. It says not to offer any therapy based on physical activity or exercise as a cure for ME/CFS. And it says not to offer programs built on deconditioning and exercise avoidance theories as the thing keeping ME/CFS going.
There is one more in the same guideline, and it is the one most often broken by accident. NG206 says not to advise people with ME/CFS to exercise outside a program overseen by an ME/CFS specialist team, and it gives being told to go to the gym or to exercise more as the example, because that advice can make symptoms worse.
The program below is a generalized program that adds a planned amount each week. On NICE's wording, that is not your program, and the fact that it is written by physios does not change that.
What NG206 describes instead, where a personalized activity plan is agreed at all, is a different shape. It starts by finding a level of activity that does not worsen symptoms, then begins below that level rather than at it, holds it steady before any thought of increasing, adjusts up or down as things change, and treats recognizing a flare or relapse early as part of the plan. The sentence that matters in it for you is that this sits with a specialist team. That is what to ask for by name.
So here is the route. Go to your own doctor or physical therapist, say that activity makes you worse hours or days later rather than tiring you on the day, and ask to be referred to a service that knows about post-viral illness. In the UK that is the ME/CFS specialist team NG206 describes. In the USA, Canada, Australia, New Zealand and Europe the names differ and the question does not, so ask your doctor what exists locally and say plainly what the pattern is.
This is not a theoretical risk, and physiotherapy has already written about it. In a 2021 editorial in the Journal of Orthopaedic and Sports Physical Therapy, Decary and colleagues reported seeing more and more patients with long COVID who had adverse effects from exercise therapy, and whose symptoms looked strikingly like those of myalgic encephalomyelitis. They described patients who had tried to fight postviral fatigue with exercise-based rehabilitation, among them previously healthy and fit clinicians, and reported that physical therapists working in the community, private practice included, did not know about the safety problem. Being handed a graded program by a well-meaning clinician is a known event rather than a rare one, which is why it is fair to take this conversation to an appointment and hold your ground in it.
If none of that is you, and activity tires you on the day and leaves you no worse the morning after next, carry on down the page.
Can you reverse deconditioning, and how long does it take?
A good deal of it, usually, over weeks to months rather than days. Welch and colleagues put both halves of the honest answer in one sentence: deconditioning may be reversible with early intervention, and the long-term effects can be devastating. Which half applies to you depends on how long the inactivity ran, how old you are, how fit and well you were beforehand, and what the illness itself did.
We looked for a dependable figure for how long the regaining takes and did not find one. The figures that circulate are rules of thumb, not measurements: the ones we could trace back were repeated from one page to the next without a study behind them, and they do not agree with each other. The losing side is the half that has been measured cleanly, in bed rest, and those numbers sit on our page on regaining strength after a hospital stay. Anyone who hands you a neat ratio for the return is guessing with more confidence than the evidence supports.
What you can do is watch the right thing. Early on, what changes is not the size of what you can manage but the cost of it: the same walk takes less out of you, and you need less of the afternoon to recover from it. Capacity follows later. Writing down what you did and how the next two mornings went will tell you more about your own pattern in a month than any device will.
Two different plans, and how to tell which one is yours
There are two ways to rebuild activity and they are not variations of each other. Giving someone the wrong one is how harm happens.
The first is progressive overload. You find a level you can manage on an average day, hold it until it is easy, then add a small planned amount and check it against the next two mornings. That is the plan the program below follows, and the sequence of exercises it uses runs from chair work to standing to stairs and load, which our hospital stay page sets out in more detail for anyone who wants the whole ladder.
The second is energy management inside a limit. Here the aim is not to add but to stay below the level that sets symptoms off, and any increase comes much later, in smaller amounts, under the supervision of people who do this work. That is the plan for the reader who answered yes to the screening question above, and this page deliberately gives no numbers for it, because NG206 puts it with a specialist team rather than on a web page.
How to tell which is yours comes down to one observation, and it is about timing rather than severity. If activity tires you on the day and you are back to your usual level by the next morning or the one after it, the first plan fits. If the cost lands hours or days later, out of proportion, and drags on instead of clearing with a night's sleep, the second one does.
One more distinction, because the two get mixed up. If pain that has carried on since the illness is your main problem, and fatigue and weakness are not, our page on central sensitization and persistent pain answers that question instead. Fatigue and pain travel together and they do not respond to the same plan.
Eating, drinking and an appetite that has not come back
Appetite is usually the slowest thing to come back after weeks of being unwell, and nothing you do in the program below will build muscle on top of an intake that has shrunk with it. Small, frequent eating occasions tend to go down better than full plates while your appetite is still poor, and spreading the protein across them instead of loading it all into the evening is the version most people manage. Thirst goes quiet too, so a glass left wherever you actually sit works better than good intentions in the kitchen.
This page gives no protein target, because how much you need depends on your body size, your kidney function, your other conditions and what you are already eating. That number belongs to your doctor or a dietitian. If you want the detail on protein and muscle, the sarcopenia page covers it.
If you are losing weight without trying, eating much less than usual, or finding eating or swallowing difficult, that is not something to sort out once you are stronger. Losing weight without trying has its own lines in the warning list at the foot of this page, and coughing, choking or food sticking when you eat or drink has a line of its own there as well, because the two are not the same problem and they do not carry the same urgency. Both are the kind of thing a doctor can act on, and asking to see a dietitian is reasonable while the weight is still going down.
If your deconditioning started with an operation
Plenty of people arrive here weak and out of condition after an operation rather than after an illness, and the rebuilding works the same way, with one difference that outranks everything else on this page. Part of you is still healing, and only the team that operated knows what that part will take. Their program comes first and this page does not replace it. If theirs has finished, or nobody gave you one beyond being told to take it easy, read this before you start, stage 1 included.
Three things in the program load a healing chest or tummy wall rather than the legs. The seated row with a band in stage 1 is loaded pulling. The wall push-up in stage 2 is loaded pushing. And pushing yourself up out of a chair through the armrests, which is what stage 1 asks for, drives your weight through your hands and down the front of your chest.
If your chest was opened through the breastbone, which is how most heart surgery is done, leave all three out, along with anything you substitute for them, until your surgical team says the breastbone has healed enough for loaded pushing, pulling and lifting. If they have asked you to keep your hands off the armrests, stand up with your arms held out in front of you instead. The breastbone rules are set out in full on the cardiac rehab page. A breastbone that clicks, grinds or feels as if it shifts is in the warning signs at the foot of this page, and it goes to the team that wired it rather than to a physio.
After an operation on your tummy or your groin, ask your surgeon or surgical team one question in these words: how much may I lift, push and pull, and at what date or milestone does that change. Ask it even if you feel well, and ask again if all you were given was advice to take it easy.
This page sets no lifting limit of its own, and the reason is worth knowing. Loor and colleagues surveyed 420 surgeons in 2020 and found just over half advised avoiding heavy lifting and strenuous activity for 6 weeks after an open abdominal operation, while the advice after keyhole surgery ran from 2 weeks through to no restriction at all. Their own conclusion was that practice varies widely and the evidence is not there to settle it. So the limit that applies to you is your surgeon's rather than an average, and a page cannot hand it to you. Until you have it, keep to the seated work, breathe out on the effort of every repetition and never hold your breath, and treat a soft lump or bulge at or near the scar as the warning list below says.
After spine surgery the limits on bending, lifting and twisting are your surgeon's too, and the chair squat, the step up and the stairs in stage 3 sit inside those limits rather than outside them. After an operation on a leg or a hip, the question is how much weight you may put through it. If you have been told to put only part of your weight through that leg, or none of it, or to keep using a frame or crutches for now, the standing and stepping work here is not yours yet, whatever the leg feels able to do.
If the operation was a hip replacement, the movements to ask about by name are standing up from a low seat, the chair squat and standing marching, because each of them can take the hip past a right angle, which many surgeons limit for the first months after some approaches. Use a high, firm seat until your surgical team or your physio has given you your own limits. Sudden severe pain in a new hip with a leg you cannot move or stand on, or that suddenly looks shorter or turned in or out, is an emergency line at the foot of this page. New pain or stiffness in a replaced joint at any time, even years later, has a same-day line of its own there, because that is how an infection around a new joint shows itself and it is the easiest thing on this page to put down to being out of condition.
One last thing that is easy to miss once you are home and getting on with it. An operation that went well does not take the warning list at the foot of this page off you. A wound that turns red, hot, swollen or leaky, a fever, a calf that swells or aches, breathlessness that arrives suddenly: those go to the team that operated, the same day, rather than into a decision about whether to do the exercises.
How to use this program
Pick the stage that matches an average day, not a good one, and start at stage 1 if you are not sure which of the three fits. If activity leaves you worse hours or days later, none of the three is your starting point, stage 1 included, and the last paragraph of this section says where to go instead. Move up when the stage you are on has been easy for a week or two and you are no worse the next morning or the one after it, and drop back a stage for a few days after a bad night rather than stopping altogether.
Each exercise page gives a typical starting dose, and several of them offer more than the stage you are in intends, because each one is written for a single exercise and not for a whole week of them. Where they disagree, take the stage's numbers. Where an exercise works one leg at a time, the stage's repetitions are for each leg. Your physio will adjust both the exercises and the numbers to suit you.
If you do not have a physio, these stages are written to be followed without one, and you can ask your doctor's office for a referral to a physical therapist (physiotherapist) for a strength and balance program, which in many countries you can also book yourself. Ask for a program you can do at home, say that standing up and the stairs are the problem, and ask when they will review it.
Set the step size before you find out what kind of day you are having. One more repetition, one minute more walking, or a slightly lower seat, decided in advance and judged by the next two mornings, beats doing everything on a good day and nothing for the two days after.
If you have high blood pressure, breathe steadily through every repetition and never hold your breath. Check with your doctor before you start if you have a heart or lung condition, or blood pressure that is not under control. If your illness involved your heart or your lungs, the cardiac rehab and breathing exercises for COPD and long-term chest conditions pages are the better starting points.
If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, keep a hand on a kitchen counter, a handrail or a sturdy chair back for the whole of the standing exercises, practice only when someone else is at home, and ask your doctor or physio about a falls check. If that is you and nobody can be there, stay with stage 1 until somebody can, or until a physio or doctor has seen you, which is not the same as doing nothing, because the seated work in stage 1 needs nobody there. The one exception inside stage 1 is standing up from the chair with the armrests, whose own page asks a reader who has fallen before to have somebody nearby for it.
Use a firm, heavy chair that will not slide or tip, with its back against a wall. A wheeled office chair is not safe for this. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet. The balance and falls prevention program is the other half of this work and pairs with the strength side without replacing it. Balance practice is done on more days of the week than the strength work, so take its frequency from that page rather than from the stages here.
Soreness for a day or two after a new exercise is normal, and many programs accept mild discomfort that settles soon after and is no worse the next morning. Sharp pain during an exercise means stop that exercise for today, and a joint that is more painful or swollen the next day means the load was too much for now, so do less next time rather than stopping altogether. Being far more tired the next day than the session should explain means you did too much, so do less next time rather than giving up. If that happens more than once, even as you do less, stop putting it down to the exercise and read the section above this program again.
A calf or thigh that is swollen, warm or red is not ordinary soreness, and it is on the warning list below. If any line on that list fits you, it is a reason to be checked before you exercise again rather than something to train through.
This page is for adults. A child or teenager who has been ill for a long spell should follow the plan from their own doctor or physio, and ask them before trying anything here. If you are pregnant, check with your midwife or physio before you start. After an operation of any kind, follow the program from your surgical team and physio instead of this one for as long as it runs, and if nobody gave you one, or yours has finished, read the section above on deconditioning that started with an operation before you start here.
One last check before the first exercise, because it is the one that changes the whole plan rather than the numbers in it. If activity reliably leaves you worse hours or days afterwards, most often between 12 and 48 hours, out of proportion to what you did, with a recovery that takes hours, days or longer, do not start this program. Go back up to the section on activity that makes you worse hours or days later, which sets out what NICE says instead and who to ask for it.
The exercise program
The exercises below carry their own stop signs and precautions. Open the line under an exercise and read them before you try it.
Stage 1: A baseline you could repeat tomorrow
Start here whatever you were ill with, and stay here until you have been through the checks in 'Before you start' above. Almost everything in this stage is done sitting, so your weight is supported for most of it, a wobble cannot put you on the floor, and the demand sits below what an ordinary day already asks of you. Sit to stand using armrests is the one exercise here that lifts your body weight: use a firm, heavy chair with its back against a wall, and let the armrests take as much of the work as you need. Set every number low enough that you could do the same again tomorrow after a bad night, which means this stage's bottom end, one set of five, rather than the numbers an individual exercise page gives, because each of those pages is written for one exercise on its own rather than for five of them in the same day. As a general range, 1 to 2 sets of 5 to 10 slow repetitions, once or twice a day, suits most people starting here, and the breathing can be done most days. Your physio will adjust this.
 Diaphragmatic breathing
Stop signs and precautions for the diaphragmatic breathing
Before you start
- If lying flat makes you more short of breath, do not lie flat for this. Sit upright in a chair or prop yourself on pillows instead, which works just as well for learning the pattern. Being short of breath when you lie down, waking at night needing to sit up to breathe, more swelling in your ankles or legs, or gaining weight quickly over a few days are all reasons to get medical advice the same day rather than to practice through, because the NHS lists breathlessness when lying down among the reasons to get urgent advice.
- If you are pregnant and past the first three months, check with your physio before exercising flat on your back.
When to stop and get help
- Your fingers or the skin around your mouth start to tingle, or you feel light-headed or spaced out. This can mean you are breathing too fast or too deeply, so stop and let your breathing go back to normal. If it has not settled within a few minutes, get medical advice the same day. If you faint, or the numbness or tingling is on one side of your face or body, call emergency services, even if it goes away.
- You suddenly become short of breath, your chest feels tight or heavy, or you are far more short of breath than usual. Stop, rest and use your breathing control. Call emergency services if the breathlessness came on suddenly, your chest feels tight or heavy, your breathing does not go back to normal, you are gasping, choking or cannot get your words out, you have pain that spreads to your arms, back, neck or jaw, you feel suddenly confused or very drowsy, or your lips or skin turn very pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands). If everything settles quickly, get medical advice the same day before you do these exercises again.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
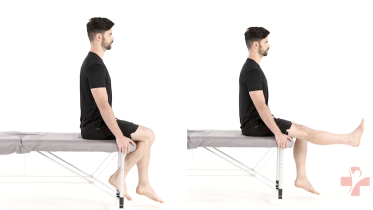 Seated knee extension
Stop signs and precautions for the seated knee extension
Before you start
- After knee ligament surgery, such as an ACL reconstruction, get the go-ahead from your surgeon or physio before you do this one. Many protocols limit how far the knee may straighten against resistance in sitting during the early stage.
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. Ask again before you add an ankle weight.
When to stop and get help
- You feel sharp pain at the front of the knee or under the kneecap.
- The knee swells up or is clearly more painful later that day or the next morning.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Sit to stand using armrests
Stop signs and precautions for the sit to stand using armrests
Before you start
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try sit to stand using armrests. Lowering into a chair and rising from it takes the hip beyond a right angle when the seat is low, and many surgeons ask you to avoid that for the first months after some operations.
- After recent heart or chest surgery through the breastbone, ask your surgeon or surgical team before you push up through the armrests, because pushing down through your hands loads the healing breastbone. If they have asked you to keep your hands off the armrests, stand up with your arms held out in front instead. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
- If knee pain builds as you go, or you have had knee surgery, check with your physio what seat height to use.
- If balance is a worry or you have fallen before, have someone nearby and place the chair next to a counter or wall you can reach once upright. If you have osteoporosis, set the chair up the same way, next to a counter or wall, though thin bones on their own are not a reason to wait until someone is at home before you stand up out of a chair. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet.
When to stop and get help
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services. A drop in blood pressure on standing, or a side effect of a medicine, can cause this, so mention your medicines when you get advice.
- Your knee, hip or back hurts sharply, or a wrist or shoulder hurts as you push on the armrests.
- A leg buckles, or you feel close to falling.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Hand grip squeeze
Stop signs and precautions for the hand grip squeeze
Before you start
- After a broken wrist, hand or forearm, or surgery on any of them such as a tendon repair, start only when your doctor, surgeon, physio or hand therapist says the bone or repair is ready for this, and follow their plan for how much to do.
- Arthritis at the base of the thumb and rheumatoid arthritis can both flare with hard gripping. Ask your physio how firm to go, and skip it on days when the joints are hot and swollen.
- Keep breathing through each hold, because holding your breath while you strain can push your blood pressure up.
When to stop and get help
- Sharp pain in the wrist, a finger joint or at the base of the thumb.
- Your hand or fingers go numb or start to tingle. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- Hand joints that are more swollen, hot or stiff afterward.
- Since the fracture or cast, the hand is getting more painful rather than less, the skin becomes very sensitive to light touch, or the hand changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
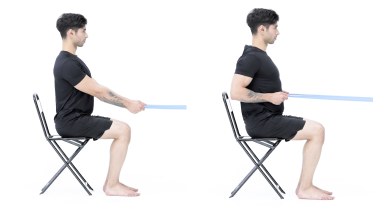 Seated row with band
Stop signs and precautions for the seated row with band
Before you start
- After shoulder surgery, rows with a band usually wait until later in rehab, so check with your surgeon or physio first.
- After heart or chest surgery, pulling against a band usually waits until your breastbone has had time to heal, so ask your surgeon or surgical team when to start: only the team that wired it can clear loaded pulling. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
- If you have high blood pressure, breathe steadily through every repetition and never hold your breath.
- Do not lean forward to reach the band or twist to one side as you pull, and if you have had a fracture in your spine, check with your physio before you start.
When to stop and get help
- A sharp pain or catching feeling in your shoulder as you pull.
- Pain, tingling or numbness spreading down an arm.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- A sudden pop or snap at the front of your elbow, sudden sharp pain there, or the muscle at the front of your upper arm bunches up or changes shape. Stop and go to an urgent care center or emergency department the same day, even if you can still bend the elbow, as this can be a torn biceps tendon.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
Stage 2: The same amount, standing up
Move up when stage 1 has been easy for a week or two, you are no worse the next morning or the morning after it, and standing work has been cleared by your doctor or physio. Keep one hand on a kitchen counter or a sturdy chair back for the whole of every standing exercise here, rather than just at the start of it. Balance at a chair is the one exception, because letting go is the exercise itself: keep the chair inside arm's reach, put your hand straight back on the moment you sway, and if you have fallen in the past year or feel unsteady on your feet, practice that one only when somebody else is at home. Balance is also the one thing here that is done on more days of the week than the strength work, so take its frequency from the balance and falls prevention program linked above rather than from this stage. If you have fallen in the past year, feel unsteady on your feet, or take medicines that make you dizzy, keep a hand on a kitchen counter, a handrail or a sturdy chair back for the whole of the standing exercises, practice only when someone else is at home, and ask your doctor or physio about a falls check. Standing up without pushing off the armrests is the exercise to judge this stage by, because it is the movement that fails first and the one that decides whether you get out of the house. Many programs use 1 to 3 sets of 8 to 15 repetitions on 2 or 3 days a week with a day in between, and a short walk on the days between, and your physio will adjust this. Start at the bottom of each range rather than the top, because six exercises at the top of their ranges adds up to far more standing work than it looks like on the page, and add repetitions before you add anything else.
 Sit to stand
Stop signs and precautions for the sit to stand
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try sit to stand. Standing up from a low seat bends the hip past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask them how high your seat should be. If you are pregnant, check with your midwife or physio before you start.
- Set up before the first stand: use a chair that will not slide, ideally with its back against a wall, and have someone nearby, or set the chair beside a kitchen counter you can reach, if you are not sure of your balance or you have fallen in the past year. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet.
When to stop and get help
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services.
- Sharp pain in the knee, hip or lower back.
- Your knee gives way or you feel you might fall.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
- You are pregnant and notice bleeding or fluid leaking from your vagina, regular painful tightenings, tummy pain that does not settle when you rest or comes with lower back pain, or a change in your baby's usual movements, such as moving less than usual. Stop and contact your midwife or maternity unit straight away. Do the same for a severe headache, problems with your vision such as blurring or flashing lights, pain just below your ribs, or sudden swelling of your face, hands or feet, which can be signs of pre-eclampsia. Call emergency services if the bleeding is heavy, the tummy pain is severe, bleeding or tummy pain comes with pain in your shoulder or feeling sick, faint or dizzy, or a headache comes on suddenly and is very severe.
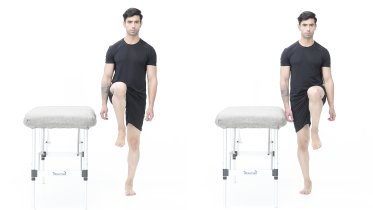 Standing marching
Stop signs and precautions for the standing marching
Before you start
- If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try standing marching. Bringing the knee up above hip height bends the hip past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask your team how high to lift, and when you may stand on the operated leg alone while the other knee comes up.
When to stop and get help
- A sharp pinch in the groin or the crease of the hip as your knee rises.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You feel unsteady even with your fingertips on the support. Grip it with your whole hand and lower the lifted foot.
 Calf raises
Stop signs and precautions for the calf raises
Before you start
- After an Achilles tendon repair or ankle surgery, calf raises usually come in at a set stage of your surgeon's protocol, often on both feet before one. Check with your physio before you start.
- After a knee or hip replacement, or other leg surgery, follow your surgeon's or physio's plan, and hold a counter or a sturdy chair back for the whole set. Rising onto your toes puts your weight forward onto a smaller base, which is where the balance goes.
When to stop and get help
- Sharp pain in the Achilles tendon, heel or arch.
- A sudden pop or snap at the back of your ankle or heel, a feeling that someone kicked you there, or sudden pain there after which you cannot push off or rise onto your toes on that leg. Stop, take the weight off that leg carefully and go to an urgent care center or emergency department the same day, even if you can still walk, as this can be a torn Achilles tendon.
- Achilles or heel pain that is clearly worse the next morning. Ease off and check with your physio.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- Your ankle gives way, or you lose your balance.
- Since the fracture or cast, the foot or ankle is getting more painful rather than less, the skin becomes very sensitive to light touch, or the foot changes color, temperature, swelling or sweating compared with the other one, or looks shiny. See your doctor or physio as soon as you can, within a few days at most, as this can be complex regional pain syndrome (CRPS) and early treatment may help.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Standing hip abduction
Stop signs and precautions for the standing hip abduction
Before you start
- If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try standing hip abduction. Some operations limit this kind of work for the first months, so the timing depends on your surgery. Your surgical team will also tell you how far to lift.
When to stop and get help
- You feel sharp pain at the side of the hip, in the groin or in the lower back.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You feel unsteady, even with the chair.
- Pain, numbness or tingling runs down the leg.
- Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Standing balance at a chair
Stop signs and precautions for the standing balance at a chair
Before you start
- After a knee replacement or other knee surgery, a hip replacement, or a broken hip or leg fixed with screws, a nail or a plate, follow your surgeon's or physio's weight-bearing plan, and start this exercise only when they have cleared you. Taking your hand off the chair puts your full body weight through both legs, so if you have been told to put only part of your weight through that leg, or none of it, or to keep using a frame or crutches for now, this exercise is not yours yet, whatever the leg feels able to do. Keep the hand on the chair until they tell you it can come off.
When to stop and get help
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You start to tip and need the chair to catch yourself. Put your hand back on it, rest, then try a shorter hold.
 Wall push-ups
Stop signs and precautions for the wall push-ups
Before you start
- After a broken or dislocated elbow, or elbow surgery such as a tendon repair, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. If you have just hurt your arm and have severe pain or cannot move the elbow, do not exercise it. Go to an urgent care center or emergency department the same day. If you heard a snap or a crack at the moment of the injury, the arm looks a different shape or sits at an odd angle, a bone is showing, or your arm or hand tingles, feels numb or turns cold, pale or blue, go to an emergency department straight away or call emergency services, and do not drive yourself.
- After shoulder surgery, including a rotator cuff repair, or after a shoulder fracture or dislocation, follow your surgeon's or physio's plan, and do only the movements and range they have cleared. Many plans allow only passive movement at first, where the arm is moved for you and its muscles stay relaxed. Putting weight through your arms usually comes later, so check with your physio first.
- After recent heart or chest surgery, get your surgeon's or surgical team's okay first, because leaning your weight into your hands and pressing back off the wall loads the healing breastbone and the front of the chest. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
When to stop and get help
- Sharp pain in the shoulder, elbow or wrist.
- Pain, numbness or tingling spreads down the arm.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- Your feet start to slip on the floor.
- A sudden pop or tearing feeling in the shoulder that brings sharp pain, new weakness or trouble lifting the arm. Stop and contact your surgical team the same day, or get medical advice the same day if you have not had surgery.
- The shoulder feels as if it has slipped out of place, looks a different shape or suddenly locks so you cannot move the arm, or your hand turns cold, pale or blue. Go to an emergency department straight away, without driving yourself, and do not try to put the shoulder back in yourself.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
Stage 3: Load, stairs and getting back out of the house
Move up when stage 2 feels routine, your balance is steady, and the standing work leaves you no worse the next morning or the morning after it. This is the stage that decides whether you get back to what you did before, because strength stops improving once the load stops rising. Change one thing at a time and judge it by the next two mornings: a lower seat, one more step up, a minute more walking, or a slightly heavier weight, never two of them in the same week. Many programs use 2 to 3 sets of 8 to 12 repetitions for the loaded work, on 2 or 3 days a week with a rest day between, and the walking fills the days in between, so start the curl with no weight at all or with something light such as a 0.5 kg (1 lb) can. The loaded work here means the chair squat, the step up, the stairs and the curl, and where one of their own pages offers a daily option, follow this stage instead, because each of those pages is written for one exercise on its own rather than for four of them in the same week. Hold the handrail for the stairs, use a low step, and your physio will adjust all of this.
 Chair squat
Stop signs and precautions for the chair squat
Before you start
- After a knee fracture or knee surgery, including a knee replacement, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you.
- Knee pain on the way down is a sign to put a cushion back rather than push through it, and after knee surgery your physio will tell you how deep to go. If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try chair squats. A low seat makes the hip bend past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Ask them what seat height suits you.
- Osteoporosis, a recent fall or shaky balance are all reasons to keep a kitchen counter within reach for every rep, and to ask your physio before you take a cushion away.
When to stop and get help
- A sharp pain in your knees, hips or low back, or knee pain that builds rep by rep.
- A knee buckles, or you start to lose your balance.
- You feel dizzy, lightheaded or faint as you get up. Sit back down and wait for it to pass. If it does not pass within a minute or two, or it keeps happening, get medical advice the same day before you practice again. If you faint, or it does not settle within a few minutes of keeping still, call emergency services.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Step up
Stop signs and precautions for the step up
Before you start
- If you have had a hip or knee replacement, or other hip or knee surgery, get the go-ahead from your surgeon or physio before you try step ups. Some operations limit this kind of work for the first months, so the timing depends on your surgery. Your surgeon or physio will also tell you what step height is right for you.
- With a heart condition or high blood pressure, check with your doctor before you start.
- If you have fallen in the past year, have osteoporosis or feel unsteady on your feet, set the step beside a handrail, a kitchen counter or a sturdy chair back, keep one hand on it for every repetition, and ask your physio whether to start with step ups at all or to build up on a single stair first.
When to stop and get help
- You feel sharp pain in the knee or the knee gives way.
- Pain at the front of the knee builds with each rep.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- You feel unsteady enough that you might fall. Stop and sit down.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Stair climbing
Stop signs and precautions for the stair climbing
Before you start
- If you have had a hip or knee replacement, or other hip or knee surgery, get the go-ahead from your surgeon or physio before you try stair climbing. Some operations limit this kind of work for the first months, so the timing depends on your surgery.
- With a heart condition or high blood pressure, check with your doctor before you start.
- If you have fallen in the past year, have osteoporosis or feel unsteady on your feet, have someone with you for the first sessions and ask your physio whether to start on a single step.
When to stop and get help
- A sharp pain in your knee or hip, or a knee that gives way.
- The knee or hip is more swollen, or clearly more painful, the next morning. Stairs load the thigh harder than anything else in a home program, so cut the number of trips rather than pushing on, and after knee or hip surgery check with your physio before you build it up again.
- You feel unsteady or catch your foot on a step. Hold the rail, stop, and sit down on a step until you feel settled.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Hold your support, sit down and get medical advice the same day before you practice again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
 Biceps curl
Stop signs and precautions for the biceps curl
Before you start
- After a broken or dislocated elbow, or elbow surgery such as a tendon repair, follow your surgeon's or physio's plan, and start this exercise only when they have cleared you. If you have just hurt your arm and have severe pain or cannot move the elbow, do not exercise it. Go to an urgent care center or emergency department the same day. If you heard a snap or a crack at the moment of the injury, the arm looks a different shape or sits at an odd angle, a bone is showing, or your arm or hand tingles, feels numb or turns cold, pale or blue, go to an emergency department straight away or call emergency services, and do not drive yourself.
- After a biceps tendon repair or shoulder surgery, curls against resistance usually wait until your surgeon's protocol allows them. Check with your physio before you pick up a weight.
- Keep breathing through each repetition rather than holding your breath, especially if you have high blood pressure.
When to stop and get help
- Sharp pain at the front of the shoulder or at the elbow.
- A sudden pop or snap at the front of your elbow, sudden sharp pain there, or the muscle at the front of your upper arm bunches up or changes shape. Stop and go to an urgent care center or emergency department the same day, even if you can still bend the elbow, as this can be a torn biceps tendon.
- Pain, numbness or tingling that spreads down the arm.
- Pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day. If one side of your face or body suddenly goes numb or weak, or your speech becomes slurred or muddled, call emergency services, even if it goes away.
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
 Brisk walking
Stop signs and precautions for the brisk walking
Before you start
- With a heart or lung condition, high blood pressure, or after a recent operation, ask your doctor or physio how much to walk and how fast before you start. If you are pregnant, check with your midwife or physio before you start.
When to stop and get help
- Chest pain or pressure, dizziness or feeling faint, a racing or irregular heartbeat, or being far more out of breath than the effort should cause.
- You feel dizzy, lightheaded, faint or sick, or the room seems to spin. Stop, sit down and get medical advice the same day before you exercise again. If you faint, it does not settle within a few minutes of sitting still, your vision suddenly blurs or goes double, or you cannot stand or walk steadily, call emergency services.
- A sharp pain in a foot, ankle, knee or hip that changes the way you walk.
- Aching, cramping or tightness in a calf, thigh or buttock that comes on at about the same walking distance every time and clears within a few minutes of standing still, and a doctor has not checked it yet. Keep the walk gentle and book an appointment with your doctor before you build up any further, as narrowed arteries in the legs (peripheral arterial disease) can cause this and are managed differently. If leg pain carries on while you are resting or in bed, or wakes you at night, get medical advice the same day. If a foot or leg suddenly turns cold, pale or blue, or suddenly becomes very painful, numb or weak, call emergency services and do not drive yourself, because the blood supply to the leg may be blocked and a leg that has gone numb or weak with it can be impossible to save if it is not treated within about six hours.
- Your calf or thigh becomes swollen, warm, tender, red or darker than usual, or has a throbbing or cramping pain that feels different from normal muscle ache. Stop and get medical advice the same day, as this can be a blood clot. If you are also short of breath or have chest pain, call emergency services.
- You feel unsteady on your feet or close to falling.
- You are pregnant and notice bleeding or fluid leaking from your vagina, regular painful tightenings, tummy pain that does not settle when you rest or comes with lower back pain, or a change in your baby's usual movements, such as moving less than usual. Stop and contact your midwife or maternity unit straight away. Do the same for a severe headache, problems with your vision such as blurring or flashing lights, pain just below your ribs, or sudden swelling of your face, hands or feet, which can be signs of pre-eclampsia. Call emergency services if the bleeding is heavy, the tummy pain is severe, bleeding or tummy pain comes with pain in your shoulder or feeling sick, faint or dizzy, or a headache comes on suddenly and is very severe.
When to see a physio or doctor
See your doctor before you start if nobody has looked into why you are weak and tired, which is the point of the section above on what has to be checked first. See a physio if you do not know which stage suits you, if standing up from a chair or managing the stairs is beyond you, if you feel unsteady, or if progress has stalled for a week or two on a program you have been keeping to.
Go sooner, not later, if activity makes you worse hours or days afterwards. That pattern changes what the right treatment is. Say it in those words at the appointment instead of calling it tiredness.
Some of what is on the warning list below does not wait for an appointment. A few of those signs mean calling emergency services, some mean being seen the same day, and others a visit within a day or two. The list says which is which, line by line, with the timing on each one. Go through it once before your first session, and again a week in, because these are not the signs most people think to watch for.
For physiotherapists
Treat deconditioning as a label of exclusion and say so in the notes. A patient who arrives with the word already attached has usually had it applied by someone who was describing her, not investigating her, and NG188's recommendation to see that symptoms which could affect safe rehabilitation have been investigated first is the citable way to reopen that. An orthostatic blood pressure and heart rate, and asking whether a blood count and thyroid function have been looked at when fatigue is building rather than easing, are quicker than three wasted weeks of exercise therapy.
Screen for post-exertional symptom exacerbation before you prescribe any progression, and screen by timing rather than by severity. The question that does the work is what the rest of that day, the next day and the day after look like, not how hard the session felt. NG206's box 2 puts it as a worsening often delayed by hours or days, disproportionate to the activity, with a prolonged recovery that may last hours, days, weeks or longer, and its glossary adds that symptoms typically worsen 12 to 48 hours afterwards, so screen the wider window rather than the typical one, and a positive answer changes the model rather than the dose.
Keep the attribution straight, because it is easy to get wrong in a letter. The post-exertional caution is NG206's and Decary and colleagues' (2021). NG188's own list of common symptoms does not include post-exertional malaise, and no recommendation in it gives an exercise caution for it, so NG188 supports the investigate-first sequence and not the exercise caution.
The uncomfortable point for a page like this one is worth stating plainly. Among the things NG206 says not to offer are programs built on deconditioning and exercise avoidance theories as the thing perpetuating ME/CFS, which is a direct judgement on the model a page titled deconditioning uses. The resolution is not to soften the model but to gate it: the model is sound for a patient whose capacity is limited by disuse and unsound for a patient whose capacity is limited by post-exertional symptom exacerbation, and the clinical skill is telling them apart before prescribing. Decary and colleagues reported that physical therapists working in the community, private practice included, did not know about the safety problem, which is the gap this gate exists to close.
For a repeatable baseline in the disuse group, the 30-second chair stand test is the cheapest measure that reflects what this population actually complains about, and the comparison that matters is what the patient could do before the illness, not a published norm.
Warning signs
Get emergency help now
- Emergency: any sign of a stroke, even if it goes away. That means a face that droops on one side, an arm you cannot lift or keep up, slurred or muddled speech, weakness or numbness on one side of your body or face, sudden blurred vision, double vision or loss of sight, trouble swallowing, sudden dizziness with unsteadiness or falling over, a sudden severe headache, or a sudden fall where your legs give way but you do not black out (a drop attack). Call emergency services straight away.
- Emergency: if chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
- Emergency: you are short of breath and you have pain that spreads to your arm, neck, jaw, back or stomach, even if your chest itself does not hurt. Call emergency services straight away. A heart attack does not always begin with chest pain, and the NHS names pain spreading to your arms, back, neck and jaw among the reasons to get emergency help when you are short of breath.
- Emergency: you suddenly become short of breath, you get chest pain or pain in your upper back that may be worse when you breathe in, you cough up blood, your heart is beating very fast, or you faint. Call emergency services straight away, even if your legs look normal. These can be signs of a blood clot in the lungs (pulmonary embolism).
- Emergency: severe difficulty breathing, meaning you are gasping, choking or cannot get your words out, or your lips or skin turn very pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands). Call emergency services straight away. This counts whether or not you have a cough or a temperature, and whether the breathlessness came on within the hour or built up over days. The NHS names both of these among the reasons to get emergency help for shortness of breath.
- Emergency: a racing, pounding, fluttering or irregular heartbeat that does not settle when you rest, or that comes with dizziness, feeling faint or fainting, chest pain or shortness of breath. Call emergency services straight away. If it has already stopped, get medical advice the same day.
- Emergency: sudden confusion, for example you, or the person you care for, suddenly become muddled, much drowsier than usual, unable to follow what is said, unsure where you are, or you see or hear things that are not there. Call emergency services or go to an emergency department straight away, without driving yourself, and take your medicines or a list of them with you. Sudden confusion can come from an infection, a stroke, a head injury, a low blood sugar level in someone with diabetes or other causes that need treating quickly.
- Emergency: you have had cancer, now or in the past, and your back or neck pain feels like a tight band around your body, or you have new or worsening pain spreading down an arm or leg, weakness, numbness, pins and needles or a loss of feeling in your arms or legs, trouble walking, or trouble controlling your bladder or bowels. Those symptoms count on their own, with or without back or neck pain. Call your cancer team's emergency number straight away, or go to an emergency department if you do not have one or cannot get through, and do not drive yourself. This can be cancer pressing on the spinal cord (metastatic spinal cord compression), which needs treatment straight away.
- Emergency: you have had a hip replacement and have sudden severe pain in your hip or groin, sometimes with a clunk or pop, and you cannot move the leg or put weight on it, or the leg suddenly looks shorter or turned in or out. Do not try to walk on it or push it back into place. Keep still and call emergency services or go to an emergency department, and do not drive yourself. Your new hip may have come out of its socket (dislocated), and a medical team needs to put it back.
- Emergency: you have just fallen and cannot get up, or you think you may have hurt your head, neck, back or hip. Stay where you are, keep warm and call emergency services, or get someone to call for you. If you got up and walked without trouble and only notice pain later, without any of the emergency signs above, use the same-day lines in this list instead.
- Emergency: you fell and cannot remember the fall or how it happened. Go to an emergency department straight away, and do not drive yourself. You may have blacked out or hit your head without knowing it.
- Emergency: after a knock to the head, being very drowsy or finding it hard to keep your eyes open, confusion, a fit (seizure), new weakness or numbness anywhere in your body, new trouble understanding, speaking, walking or keeping your balance, new problems seeing or hearing, clear fluid coming from your ears or nose, bleeding from your ears or bruising behind them, a black eye when your eye was not hit, a dent in your head or a wound with something stuck in it, or a change in behavior. Call emergency services straight away. These can be signs of an injury to the brain.
- Emergency: a knock to the head in a high-energy accident, even if you feel completely well. That means a fall from a height of more than 1 meter (about 3 feet) or more than 5 stairs, a crash at high speed, a car that rolled over, being thrown from a vehicle, being hit by a vehicle while walking or cycling, a bike crash, an accident on a quad bike or similar motorized vehicle, a fall from a horse, a diving accident, or any other heavy, fast impact to the head. Call emergency services straight away, without waiting to see how you feel. A high-energy head injury is a reason for emergency assessment on its own, with no symptoms needed.
- Emergency: after a knock to the head, you were knocked out, even for a moment, you cannot remember what happened just before or after, you have had a headache ever since, or you are being sick (vomiting). The same applies, even if you feel fine, if you take medicine that thins your blood, other than aspirin on its own, have a bleeding or clotting condition, have had brain surgery in the past, or had been drinking alcohol or taking drugs when it happened. Go to an emergency department straight away, and do not drive yourself.
- Emergency: severe neck pain after a knock to the head, whatever the fall or the knock was like. Keep still and call emergency services, and do not let anyone move you until someone trained has checked your neck. If the neck pain only starts later and nobody has checked your neck since, go to an emergency department straight away, and do not drive yourself.
- Emergency: after a knock to the head, swelling, a deep cut or severe pain at the exact spot that was hit. Call emergency services or go to an emergency department straight away, and do not drive yourself. These can be signs of a broken skull.
Get help today
- Same day: you blacked out or fainted, even for a moment. Get medical advice the same day. Call emergency services instead if the person is not breathing, cannot be woken within 1 minute, has not fully recovered or has trouble speaking or moving, has chest pain or a pounding, fluttering or irregular heartbeat, fainted while exercising or lying down, is shaking or jerking, or was badly hurt.
- Same day: dizziness, lightheadedness, blurred vision or feeling faint when you stand up that is new for you, does not pass within a minute or two, keeps happening, or has made you fall. Sit or lie down, and get medical advice the same day. This can be a drop in blood pressure on standing (postural hypotension), a type of low blood pressure, which the NHS lists among the causes of falls, and your doctor can check it. Tell them about your medicines, because some can cause it. If it does not settle within a few minutes of sitting or lying still, call emergency services. If you faint, use the fainting line above.
- Same day: dizziness or feeling faint during or after exercise, other than the brief lightheadedness as you stand up covered in the line above, without any of the emergency signs above. Stop the exercises and get medical advice the same day. If you faint, it does not settle within a few minutes of sitting still, or you cannot stand or walk steadily, call emergency services.
- Same day: a calf or thigh that is newly swollen or getting more swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Same day: since an operation, the wound is red, hot, swollen, leaking fluid or opening up, you have a fever or feel hot and shivery, or the pain in that area is new or getting worse quickly. Contact your surgical team or the ward you went home from the same day rather than waiting for your physio appointment, and if you cannot reach them, go to an emergency department the same day. This can be an infection in the wound or deeper, around a repair or a new joint. Redness can be harder to see on brown or black skin. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: since heart or chest surgery through your breastbone, the breastbone clicks, cracks, grinds or feels as if it shifts or moves apart when you cough, laugh, turn over in bed or use your arms, or the middle of your chest becomes more painful or feels loose. Stop the arm, pushing, pulling and lifting exercises, hold a folded towel or a cushion against your chest when you cough, and contact your surgical team the same day, or get urgent medical advice if you cannot reach them. A breastbone that has not knitted back together is a surgical problem rather than something exercise settles, and your physio cannot clear it. If the chest wound gapes open, bleeds heavily or you can see bone, go to an emergency department straight away.
- A soft lump at or near a scar from an operation on your tummy or groin, or at or near your belly button, that gets bigger when you cough or strain, or that gets smaller or disappears when you lie down. This can be a hernia, so see your doctor. If the lump becomes painful or tender, if it used to flatten when you lay down and now stays up, or if you have a bloated tummy, you feel or are being sick, you are constipated, or you have a high temperature or feel hot, cold or shivery, get medical help straight away, the same day, for example at urgent care or an emergency department, and do not try to push the lump back in yourself. If the pain is severe or came on suddenly, you cannot poo or pass wind at all, you are vomiting blood or your vomit looks like coffee grounds, or you have suddenly become confused, call emergency services or go to an emergency department straight away.
- Same day: at any time after a joint replacement, even years later, new pain or new stiffness in the replaced joint, with or without a high temperature or feeling hot, cold or shivery, or a replaced joint that becomes hot, red or swollen, which counts on its own. Contact your surgical team or get medical advice the same day. A new joint can become infected long after the operation, and that needs treating quickly. A normal temperature is not an all clear: OrthoInfo says fever is no longer considered a sign of an infection after a joint replacement, that the symptoms can range from mild redness and swelling up to life-threatening septic shock and sometimes there are none at all, and it lists increased pain or stiffness in a previously well-functioning joint among them. So do not wait for a temperature, and do not put new pain or stiffness in a replaced joint down to being out of condition until your surgical team has heard about it.
- Same day: in the weeks since the illness you are getting more and more tired, breathless doing everyday things such as walking to the toilet or getting dressed, dizzy or lightheaded, your heart is racing, or your skin looks paler than usual. Contact the team who looked after you, or get medical advice the same day. Tiredness and breathlessness that build up like this are not part of the usual recovery. Blood loss from an illness, an injury or an operation can leave you short of red blood cells (anemia), which is treatable, and a slow bleed or an infection can show up the same way. If breathlessness comes on suddenly, or you get chest pain, call emergency services, as the emergency line above explains.
- Same day: a new or worsening cough, phlegm, a high temperature, chest pain when you breathe or cough, or feeling more short of breath than you were a week ago. Get medical advice the same day. A chest infection can show up as a cough, breathlessness, a high temperature, chest pain, wheezing, an aching body, loss of appetite and tiredness, and the NHS notes that feeling confused is common in older people who have pneumonia, so the first sign is not always a cough. If you are struggling to breathe, your lips, skin or tongue turn pale, blue or blotchy, you cough up blood, your heart is beating very fast or you suddenly feel confused, call emergency services. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: you cough or choke when you eat or drink, food sticks in your throat or chest, your voice sounds wet or gurgly after you swallow, food or drink comes back up, or you are short of breath after eating or drinking. Get medical advice the same day, and ask whether you need your swallowing assessed by a speech and language therapist. The NHS names coughing or choking while eating or drinking, food that feels stuck, a wet, gurgly voice and being short of breath after eating as reasons to get urgent advice, and lists repeated chest infections, weight loss and dehydration among what a swallowing problem leads to over time. An unsafe swallow is one of the ways the chest infection in the line above starts, so this is worth raising even if nobody has asked you about your swallowing. If trouble swallowing came on suddenly, use the stroke line above and call emergency services. If you or someone with you is choking and cannot cough, speak or breathe, call emergency services straight away.
- Same day: you have become short of breath when you lie down flat, or you wake in the night needing to sit up to breathe, your ankles, legs or tummy are more swollen than they were, you have gained weight quickly over a few days, or you are coughing up frothy pink phlegm. Get medical advice the same day. The NHS lists breathlessness when you lie down, suddenly gaining weight and coughing up frothy pink phlegm as reasons to get urgent advice, because the heart may not be keeping up with the fluid in your body, which is treatable and is a common reason for going back into hospital in the first weeks at home. If you are struggling to breathe, your lips or skin turn pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands, the soles of the feet or the gums), or you have chest pain, call emergency services.
- Same day: you are short of breath while you are sitting still, or something small such as getting dressed or walking to the bathroom leaves you breathless when it did not a week or two ago. Get medical advice the same day rather than reading it as being out of condition. Call emergency services if the breathlessness came on suddenly, you are struggling to breathe, you are gasping, choking or cannot get your words out, your lips or skin turn pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands, the soles of the feet or the gums), or you also have chest pain.
- Same day: in the past few hours or days you, or the person you care for, have become quieter and more withdrawn, slower to answer, harder to hold a conversation with, less interested in food, or are moving about less than usual, and this is a change from how you were. Get medical advice the same day and say when the change started. NICE names withdrawal, slow responses, reduced movement, worse concentration and a smaller appetite as the signs of the quiet kind of delirium, which is the kind most often missed, and asks for changes like these to be assessed rather than watched. Delirium is common and usually passes, but the cause of it needs finding. If the confusion came on suddenly, or they are much drowsier than usual, muddled or cannot follow what is said, use the emergency line above instead. If they also have a temperature, are not drinking, or you cannot keep them awake, call emergency services.
- Same day: after a fall, you are in pain, have hurt yourself or feel unwell, or you were on the floor for an hour or more, without any of the emergency signs above. Get medical advice the same day, even if you managed to get up.
- Same day: a leg or foot that is getting weaker, for example your foot drags, catches on the ground or slaps down when you walk (foot drop). Get medical advice the same day. If the weakness is getting worse by the hour, go to an emergency department.
- Same day: new hip or groin pain after a fall, even a small one, if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time, even if you can still walk. Get medical advice the same day. A broken hip is not always obvious at first.
- Same day: back pain after a minor fall or strain if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time. Get medical advice the same day. Until it has been checked, stop the exercises and keep away from lifting, bending forward and twisting, because those load a bone in the spine that may be broken.
- Losing weight without trying. If you are being treated for cancer now, contact your cancer team the same day.
- Losing weight without trying. If you also have new back or neck pain, get medical advice the same day.
Book an appointment
- Losing weight without trying. See your doctor within a day or two and mention it.
- Within a few days: you have had a fall, even if you were not hurt, or you keep tripping, stumbling or feeling that your legs might give way. Book an appointment with your doctor within a few days and ask about a falls assessment. Tell them about every fall, even the ones where you were not hurt.
- Routine: your strength or your walking has stopped improving over a week or two, or you cannot manage the exercises on this page, and you have none of the signs above. This is not an emergency, but ask your physio or your doctor for a review in the next week or two.
Common questions
Can you reverse deconditioning?
Usually a good deal of it, and the honest answer has two halves. Welch and colleagues, writing in 2024 about the deconditioning that follows a hospital stay, say it may be reversible with early intervention and that the long-term effects can also be devastating, so neither a promise nor a shrug is the truthful answer. What you can act on is the order of things: have the treatable causes of weakness looked for, then build activity back in planned steps judged by the next two mornings. The exception is the reader whose symptoms reliably worsen hours or days after activity, for whom adding a fixed amount each week is the wrong treatment, and the section above the program on this page explains why and what to ask for instead.
How long does it take to reverse deconditioning?
Weeks to months, and we could not find a dependable figure to give you. It depends on how long the inactivity ran, on your age, and on how fit and well you were before the illness, and a page cannot weigh those for you. Anyone who offers you a neat ratio is passing on a rule of thumb rather than a measurement. The one part that has been measured properly is how fast strength goes rather than how fast it returns, from a bed rest study set out on our page on regaining strength after a hospital stay. In practice the first thing that changes is not what you can do but how long it takes you and how long you need afterwards, so that is the thing worth writing down each week.
What are the symptoms of deconditioning?
Weakness that shows up in whole movements rather than in one muscle, breathlessness on effort that used to be easy, a heart that races at small loads, poor balance, and tiredness that arrives sooner in the day than it used to. Standing up from a low seat, stairs and carrying anything upstairs are usually the first three things people notice. Welch and colleagues also describe a cognitive side, which they define by delayed mental processing and place on a spectrum with full delirium at the far end, which is one reason thinking feels slower too. None of that list is a diagnosis, because every item on it has other causes, and that is the point of the section on this page about what has to be checked first.
Is deconditioning syndrome a real diagnosis?
Not in the way a reader searching for criteria is hoping. It is a descriptive term rather than a disease with a test, and nobody hands it to you after an examination the way they would hand you a diagnosis of anemia or an underactive thyroid. Welch and colleagues make the sharper version of that point: they call the term descriptive, say it plays down the organ dysfunction that goes alongside it, and say it implies a reversibility that may not be there. Used well, it is what is left after the treatable causes of weakness have been looked for and ruled out. Used badly, it is a label that stops the looking.
How do I get strength back after the flu?
The same way as after any long illness, and more slowly than you will want to. Start with sitting work at a level you could repeat tomorrow even after a bad night, hold that for a week or two, then make one planned increase and judge it by the next two mornings. Get yourself checked before you start standing and loaded work, because a stretch of feeling weak and tired after a viral illness has several treatable causes and they are looked for before a program, not after it has failed. If each attempt leaves you worse hours or days later rather than tired on the day, read the section above the program on this page before you try again.
Can deconditioning explain dizziness or a racing heart when I stand up?
It is one of the things people are told, and it is not something to settle at home. Dizziness, lightheadedness or a heart that races when you get to your feet is a symptom with its own routes on the warning list at the foot of this page, and the first step is a doctor checking your blood pressure and heart rate lying and then standing, which takes a few minutes in a clinic. Medicines are worth raising in the same appointment, because some cause it. Never stop or change a prescribed medicine on your own. Until it has been looked at, treat it as a reason to be checked rather than a reason to push through, and keep to the seated work in stage 1.
References
- National Institute for Health and Care Excellence. Myalgic encephalomyelitis (or encephalopathy)/chronic fatigue syndrome: diagnosis and management. NICE guideline NG206. Published 29 October 2021. https://www.nice.org.uk/guidance/ng206
- National Institute for Health and Care Excellence. COVID-19 rapid guideline: managing the long-term effects of COVID-19. NICE guideline NG188. Published 18 December 2020, last updated 25 January 2024. https://www.nice.org.uk/guidance/ng188
- Welch C, Chen Y, Hartley P, Naughton C, Martinez-Velilla N, Stein D, Romero-Ortuno R. New horizons in hospital-associated deconditioning: a global condition of body and mind. Age and Ageing. 2024;53(11):afae241. https://doi.org/10.1093/ageing/afae241
- Decary S, Gaboury I, Poirier S, et al. Humility and Acceptance: Working Within Our Limits With Long COVID and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome. Journal of Orthopaedic and Sports Physical Therapy. 2021;51(5):197-200. https://doi.org/10.2519/jospt.2021.0106
- National Institute for Health and Care Excellence. Delirium: prevention, diagnosis and management in hospital and long-term care. Clinical guideline CG103. Published 28 July 2010, last updated 18 January 2023. https://www.nice.org.uk/guidance/cg103
- National Institute for Health and Care Excellence. Head injury: assessment and early management. NICE guideline NG232. Published 18 May 2023. https://www.nice.org.uk/guidance/ng232
- NHS. Iron deficiency anaemia. Page last reviewed 26 January 2024. https://www.nhs.uk/conditions/iron-deficiency-anaemia/
- NHS. Low blood pressure (hypotension). Page last reviewed 11 July 2023. https://www.nhs.uk/conditions/low-blood-pressure-hypotension/
- NHS. Heart failure. Page last reviewed 26 June 2026. https://www.nhs.uk/conditions/heart-failure/
- NHS. Pneumonia. Page last reviewed 17 July 2026. https://www.nhs.uk/conditions/pneumonia/
- NHS. Sepsis. Page last reviewed 14 May 2026. https://www.nhs.uk/conditions/sepsis/
- NHS. DVT (deep vein thrombosis). Page last reviewed 30 April 2026. https://www.nhs.uk/conditions/deep-vein-thrombosis-dvt/
- NHS. Falls. Page last reviewed 6 March 2025. https://www.nhs.uk/conditions/falls/
- NHS. Fainting. Page last reviewed 17 August 2026. https://www.nhs.uk/symptoms/fainting/
- NHS. Sudden confusion (delirium). Page last reviewed 28 May 2024. https://www.nhs.uk/symptoms/confusion/
- NHS. Symptoms of a stroke. Page last reviewed 12 September 2024. https://www.nhs.uk/conditions/stroke/symptoms/
- NHS. Dysphagia (swallowing problems). Page last reviewed 26 October 2026. https://www.nhs.uk/symptoms/swallowing-problems-dysphagia/
- NHS. Shortness of breath. Page last reviewed 30 January 2024. https://www.nhs.uk/symptoms/shortness-of-breath/
- NHS. Head injury and concussion. Page last reviewed 29 May 2025. https://www.nhs.uk/conditions/head-injury-and-concussion/
- NHS. Heart palpitations. Page last reviewed 17 March 2026. https://www.nhs.uk/conditions/heart-palpitations/
- NHS. Hernia. Page last reviewed 19 May 2026. https://www.nhs.uk/conditions/hernia/
- NHS. Complications of a hip replacement. Page last reviewed 6 March 2024. https://www.nhs.uk/tests-and-treatments/hip-replacement/complications-of-a-hip-replacement/
- American Academy of Orthopaedic Surgeons. Infection after joint replacement. OrthoInfo. https://www.orthoinfo.org/en/diseases--conditions/joint-replacement-infection/
- National Institute for Health and Care Excellence. Spinal metastases and metastatic spinal cord compression. NICE guideline NG234. Published 6 September 2023. https://www.nice.org.uk/guidance/ng234
- Loor MM, Dhanani NH, Trautner BW, Hughes TG, Schwartz J, Wei Q, Liang MK. Current surgeon practices for postoperative activity restrictions after abdominal surgery vary widely: A survey from the communities on the ACS website. Surgery. 2020;168(5):778-784. https://doi.org/10.1016/j.surg.2020.05.035
- Sport and Recreation Alliance and UK Government. UK concussion guidelines for non-elite (grassroots) sport. Published 2023, updated November 2024. https://sportandrecreation.org.uk/campaigns-and-policy/concussion/concussion-guidelines-for-grassroots-sport-html-version
Written and checked by the PocketPhysio editorial team. Last updated 2026-11-03.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.