
Hip fracture rehab: exercises after a broken hip
What is a hip fracture?
A hip fracture is a break at the top of the thighbone (femur), just below or beside the ball of the hip joint. The two most common kinds are a break through the neck of the bone, just under the ball, and a break a little lower, between the two bony bumps at the top of the thighbone (intertrochanteric) (OrthoInfo). Most happen in people aged 65 or over after a simple fall, often because the bones have lost strength (OrthoInfo). The usual signs are pain in the hip, upper leg or groin and not being able to stand or put weight on the leg. Sometimes the leg also looks shorter or sits at an odd angle (NHS).
A broken hip needs surgery, usually on the day you arrive in hospital or the day after (NHS). A few breaks through the neck of the bone are treated without an operation, mostly in younger, healthy people whose bone has not moved out of place (OrthoInfo). This page is for adults after hip fracture surgery.
How your hip was repaired
That depends on where the bone broke and how far it moved. The NHS describes three main options: fixing the pieces in place with screws, nails, rods or plates, replacing the ball of the joint (a partial replacement, or hemiarthroplasty), or replacing the whole joint (a total hip replacement). NICE recommends a partial or total replacement for a displaced break inside the joint capsule, a sliding hip screw and plate for most breaks between the bony bumps, and a metal rod down the middle of the bone (an intramedullary nail) for breaks just below them (NICE CG124).
Ask your team which operation you had, and write it down. It decides how much weight you may put through the leg at first and whether any positions are off limits. It also matters if you ever end up back in hospital with hip pain.
How this differs from a planned hip replacement
The total hip replacement rehab program is for people who choose to have a hip replaced, usually for arthritis, and who often go into surgery fairly well. A broken hip comes without warning, usually after a fall, and many of the people it happens to are older and already have other health problems. So even if your break was treated with a partial or full replacement, recovery tends to be slower. Falls and bone strength need as much attention as the hip itself, and so does sudden confusion.
In practice, two things are different. After screws, a nail or a plate, your surgeon may want you to limit the weight on the leg for a while (OrthoInfo). And hip precautions, the positions some people are asked to avoid after a replacement, only apply if part or all of your joint was replaced and your surgeon asks for them.
Your surgeon's and physio's plan comes first
NICE asks surgeons to operate with the aim of letting you put your full weight on the leg, without limits, straight after the operation (NICE CG124). OrthoInfo says that after a replacement you can usually take full weight straight away unless there are complications. After screws, a nail or a plate, your doctor will tell you whether you can take full weight or have limits. Follow the weight-bearing plan your team gave you, and any positions they asked you to avoid. Where your hospital leaflet says something different from this page, go with the leaflet and ask your physio about it.
Getting moving after the operation
NICE advises that you are offered a physio assessment on the day after surgery and got up and moving that day, unless there is a medical or surgical reason not to. After that it should be at least once a day, with regular physio review (NICE CG124). The Australian and New Zealand hip fracture guideline says the same (ANZHFR 2014). OrthoInfo explains why it matters: getting out of bed early helps prevent chest infections (pneumonia), bed sores and the muddled thinking that long bed rest can bring on.
The NHS says you will have regular physio soon after surgery to get you standing and moving, plus exercises to carry on at home. Many people go straight home from hospital. Some spend a short time in a rehab unit first (OrthoInfo).
Typical recovery after a broken hip
Treat these as typical times, not targets. Most people spend around 1 to 4 weeks in hospital, and the break usually takes several weeks or months to heal, sometimes longer (NHS). Pain and bruising are a normal part of recovery. So is swelling, which can take a few months or longer to settle (Gateshead Health).
Recovery is often slower than after a planned hip replacement, and people vary a lot. The NHS is frank about it: you may never get back quite the strength and movement you had, you may need a walking stick or frame, and some people need help at home from carers or other health professionals. Your physio can help you set goals that fit how you were before the fall.
Does exercise help after a hip fracture?
Yes, though the gains are often modest. A Cochrane review of 40 trials with 4,059 people, most of them women with an average age of 80, found that programs aimed at mobility may give a moderate improvement in mobility while people are still in hospital (Fairhall 2022). After leaving hospital, mobility programs gave a small but meaningful improvement in mobility and walking speed, and that evidence is high certainty. Training in walking, balance and everyday tasks helped mobility, and programs with several parts probably helped more. Most of the trials left out people with memory problems, so less is known about how much exercise helps them.
Single trials are more mixed. In a US trial, a home program of everyday exercises such as standing up from a chair and stepping up onto a step, taught by a physical therapist (physiotherapist) and done alone at home for 6 months, gave a modest improvement in physical function (Latham 2014). A later US trial of 16 weeks of home physical therapy with aerobic, strength, balance and functional training did not significantly increase the number of people who could walk 300 meters in 6 minutes, a marker of walking in the community, compared with a gentler control program (Magaziner 2019). An Australian trial of a home balance and strength program after a leg or pelvic fracture found no significant change in disability or falls over 12 months, though some other measures, such as balance and mobility, were better (Sherrington 2020). So the stages on this page follow common hospital programs, such as Gateshead Health's hip fracture leaflet, and your own team's plan still comes first.
How to use this program
Do only the exercises your team has cleared. Move up a stage when the current one feels easy and your team agrees. Hospital leaflets often ask for the early exercises several times a day, for example 10 to 15 repetitions, 3 to 4 times a day (Gateshead Health). Each exercise page gives a typical starting dose. Your physio will adjust this.
Some pain and aching is expected after a broken hip, especially in the first weeks. Mild discomfort during the exercises is fine if it settles soon after you stop and your hip is no worse the next morning. Sharp pain, pain that climbs with each repetition, or a hip that is clearly sorer or more swollen the next day tells you the load was too much. Next time, do fewer repetitions or smaller movements, and tell your physio. If you have high blood pressure, breathe steadily through every repetition and never hold your breath.
Two things mean you stop the exercises and get help. Your calf or thigh is getting more swollen, or becomes warm, tender, red or darker than usual, or has a new throbbing or cramping pain. This can be a blood clot, especially after an operation, an injury, time in a cast, boot or brace, or a spell of being much less mobile than usual, and after an operation it can also be an infection. Stop and contact your medical team or get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
Your wound becomes more red, hot, swollen or painful, or starts to leak. Contact your medical team the same day. Everything else, and how fast to act on it, is in the warning signs at the end of this page.
The exercise program
Stage 1: In bed and in the chair, from the day after surgery
Your physio usually starts these on the ward, often the day after the operation, and you keep them going at home. Ankle pumps get the blood in your legs moving, and quad sets switch the thigh muscle back on. Do both often while you are still sitting or lying for much of the day. In heel slides, bend the hip and knee only as far as your team allows, which after a partial or full replacement is often no further than a right angle, and keep the knee pointing at the ceiling. Short arc quads in bed and knee straightening in a chair build the front of the thigh, the muscle that gets you out of a chair and walking. If your team also gave you buttock squeezes or a lying leg slide out to the side, do them exactly as you were shown.
 Ankle pumps
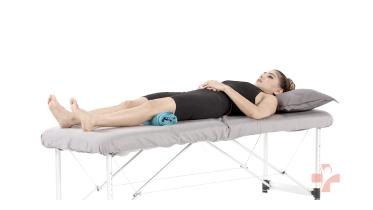 Quad sets (towel under knee)
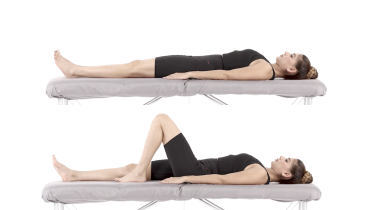 Heel slides
 Short arc quads
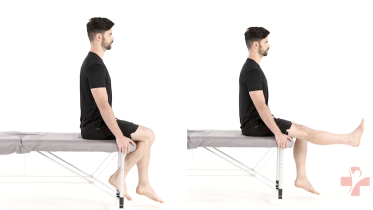 Seated knee extension
Stage 2: Standing at a support and walking with your aid
These usually start once you are up with your frame or crutches and your physio says standing exercises are fine, often before you leave hospital. Put only as much weight through the operated leg as your team has allowed, when you walk and in every standing exercise. Hold a kitchen counter or a heavy chair, stand tall and move the operated leg forward, out to the side and a short way back. Keep each movement small and slow. If part or all of your hip was replaced, check with your surgeon or physio before you try the side leg lift, as some surgeons ask you not to work the side of the hip for the first months after a replacement done from the side. If it was replaced from the front, ask how far back the leg may go. Calf raises on both feet strengthen the push-off you use when you walk. Stay on your frame or crutches until your physio moves you on, and start the cane walking pattern only when they say you are ready for a stick.
 Standing hip flexion
 Standing hip abduction
 Standing hip extension
 Calf raises
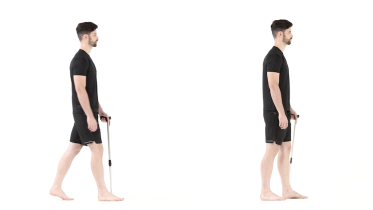 Walking with a cane
Stage 3: Standing up from a chair and balance
Start once you walk steadily indoors with your aid and your physio agrees. Begin sit to stand from a firm, high chair with arms, pushing up through the armrests, and ask your physio how high the seat should be. The weight shifts teach you to move your weight over the operated leg with control. The feet together and semi-tandem holds then narrow your base a little at a time. Do the weight shifts and standing holds with a kitchen counter in front of you and a chair behind you, and keep a hand on the counter for as long as you need it. The forward reach is set up differently: stand side on to the counter as the exercise shows, so your nearer hand can grab it, and reach only as far as you can while staying steady. It trains the leaning you do at cupboards and counters.
 Sit to stand using armrests
 Side to side weight shift
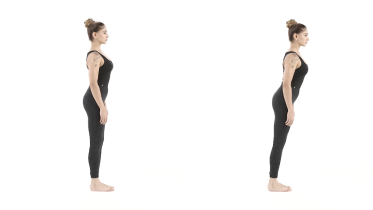 Forward and backward weight shift
 Standing with feet together
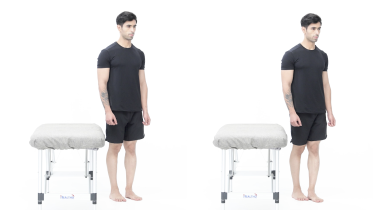 Semi-tandem stance
 Standing forward reach
Stage 4: Strength and falls prevention
Move on when stage 3 feels easy and your physio is happy, often once you are home and walking with a stick or without an aid. Standing up from a chair and stepping up onto a step are the kind of everyday exercises used in a home exercise trial after hip fracture (Latham 2014). Start sit to stand without your hands from a high seat, keep the mini squat shallow and use a low step. On the stairs, keep hold of the rail. Go up with your good leg first and down with the operated leg first until your physio says you are ready to go foot over foot, as the video shows. Tandem stance and regular walks build steadiness and stamina. Get a physio to teach you how to get up from the floor before you practice it at home. If part or all of your hip was replaced, check with your surgeon or physio before you try mini squats, step ups, tandem stance or getting up from the floor.
 Sit to stand
 Mini squat
 Step up
 Stair climbing
 Tandem stance
 Brisk walking
 Getting up from the floor
What to avoid or change
If you have had a hip replacement or other hip surgery, get the go-ahead from your surgeon or physio before you try knee to chest stretches, figure 4 stretches or deep squats. Pulling the knee toward your chest and squatting deep bend the hip well past a right angle, and many surgeons ask you to avoid that for the first months after some operations. Some hospitals also ask you not to cross your legs or to twist and swivel on the operated leg for a few months after a partial or full replacement (University Hospitals Plymouth). That is why this program leaves all of these out and uses a high seat and small bends instead.
Sit on a firm, high chair with arms rather than a low sofa, and use the raised toilet seat or other equipment your occupational therapist gave you, if they did. Avoid jumping and running while your hip heals, along with anything else where you could easily fall. Ask your team before you lift or carry anything heavy. If you have had a hip or knee replacement, get the go-ahead from your surgeon before you try jumping or hopping. Many surgeons advise against jumping and hopping after a joint replacement for good, not just for the first months, because each landing sends high impact through the new joint.
Walking, stairs and your walking aid
You will usually go home with a walking frame or crutches, and your physio will move you on to a different aid when you are ready (Gateshead Health). Do not swap to a lighter aid, or stop using one, until your physio says so. If you still limp without it, carry on with it and tell your physio about the limp.
On stairs, Gateshead Health's leaflet teaches one step at a time. Going up, step up with your good leg, then the operated leg, then bring your crutch or crutches up. Going down, put the crutches down first, then step down with the operated leg, then your good leg. Physios sum it up as "up with the good, down with the bad". Use a handrail wherever there is one.
Falls and bone health: lowering the chance of another break
A broken hip after a simple fall is often a sign that your bones have lost strength (Royal Osteoporosis Society). If a bone broke that easily, the Royal Osteoporosis Society suggests asking your doctor how likely it is that you have osteoporosis and will break more bones. A fracture liaison service can help you prevent further breaks and keep your bones healthy (NHS). NICE asks hip fracture teams to link up with falls prevention and bone health services (NICE CG124). If nobody has mentioned either, raise it with your doctor.
It is also worth finding out why you fell. A blackout before the fall, or no memory of it, needs medical advice the same day if nobody has looked into it, and UK guidance suggests a heart check within 24 hours for some people, including those over 65 whose blackout came without warning (NICE CG109).
At home, take up loose rugs and clear cables and clutter off the floor. A light left on at night for the trip to the toilet helps too. Wear flat shoes that fit well and grip the floor, not socks, tights or bare feet. Once you finish this program, the balance and falls prevention program and the osteoporosis program carry the work on.
Sudden confusion (delirium) after a broken hip
Some people become suddenly confused, drowsy or agitated in the days after a broken hip. This is called delirium. NICE asks hospital teams to check for memory and thinking problems when you arrive and to keep looking for delirium during your stay (NICE CG124). Long spells in bed can add to muddled thinking, which is one more reason to get up early (OrthoInfo).
Family members often notice it first. If you are caring for someone who seems more muddled, sleepy or restless than usual, tell the ward staff straight away. At home, the NHS says to call emergency services or go to an emergency department if someone suddenly becomes confused. Urine infections are a common cause in older people (NHS).
Blood clots after a broken hip
A broken hip and the operation to fix it raise the chance of a blood clot in a deep vein of the leg (deep vein thrombosis), and a clot can travel to the lung (pulmonary embolism), which needs treatment straight away (NHS). NICE advises offering blood-thinning medicine for a month after surgery for a broken hip when your risk of a clot outweighs your risk of bleeding (NICE NG89). If you went home with injections, tablets or stockings, keep using them exactly as prescribed, for the full time your team gave you. While you take blood-thinning injections or tablets, other than aspirin on its own, a knock to the head needs checking at an emergency department straight away, even if you feel fine, as the warning signs below explain.
The ankle pumps from stage 1 and regular walking help as well. Get a calf or thigh that is newly swollen, warm or painful checked the same day. Sudden breathlessness or chest pain is an emergency.
When to see a physio or doctor
In hospital, NICE expects regular physio review (NICE CG124). Once you are home, ask for a physio review if your walking is not improving, you still limp badly, you cannot manage the stairs or the toilet at home, you are frightened of falling, or you are unsure how far to push the exercises. Ask your doctor about a falls assessment and a bone health check if nobody has offered them.
Some problems cannot wait for a review. The warning signs below show which are emergencies and which need a call to your surgical team the same day. For the first months after surgery, keep the hospital's phone number where you can find it quickly.
For physiotherapists
This page gives patients a general framework after surgery for hip fracture in adults and defers to the treating team on fixation type, weight-bearing status and any approach-specific precautions after hemiarthroplasty or total hip arthroplasty. NICE CG124 recommends surgery aimed at unrestricted full weight bearing in the immediate postoperative period (1.6.1), arthroplasty for displaced intracapsular fractures (1.6.2), consideration of an anterolateral rather than a posterior approach for hemiarthroplasty (1.6.8), extramedullary implants such as a sliding hip screw in preference to an intramedullary nail for trochanteric fractures above and including the lesser trochanter, except reverse oblique (1.6.9) and a nail for subtrochanteric fractures (1.6.10). It recommends physiotherapy assessment and mobilization on the day after surgery unless contraindicated (1.7.1), mobilization at least once a day with regular physiotherapy review (1.7.2), hip fracture programs linked with falls prevention and bone health services (1.8.1), and screening for cognitive impairment on presentation with reassessment for delirium during admission (1.8.3). The ANZ guideline (2014) matches the mobilization recommendations.
Fairhall 2022 (Cochrane, 40 trials, 4,059 participants, mean age 80, 80% women; 70% of trials excluded people with cognitive impairment) reported low-certainty evidence of a moderate improvement in mobility with in-hospital strategies (SMD 0.53) and moderate-certainty evidence of a small improvement in walking speed whose confidence interval crossed zero. After discharge, mobility strategies overall gave small, clinically meaningful improvements in mobility (SMD 0.32) and walking speed (SMD 0.16), both high certainty. By training type, gait, balance and functional training gave a small, clinically meaningful improvement in mobility (SMD 0.20, high certainty), resistance training may improve 6-minute walk distance (low certainty), multicomponent programs probably give a substantial improvement (moderate certainty), and the effect of aerobic training is uncertain. Mobility strategies probably make little or no difference to short-term mortality.
Latham 2014 (n = 232, after completion of standard rehabilitation) found a 6-month home functional exercise program improved SPPB by 0.8 points (P < .001) compared with nutrition education. The CAP trial (Magaziner 2019, n = 210, mean age 80.8) found no significant difference in community ambulation after 16 weeks of home aerobic, strength, balance and functional training versus TENS plus active range of motion (22.9% vs 17.8%). RESTORE (Sherrington 2020, n = 336, lower limb or pelvic fracture, age 60 or over) found no significant effect on mobility-related disability or falls at 12 months (IRR 0.96), with benefits on secondary measures of balance, mobility, fall risk, physical activity and mood that the authors ask readers to interpret with caution (multiple analyses).
With the cues given (heel slide range, a high seat, a shallow squat, standing hip extension only a short way back), the exercise selection avoids deep flexion, adduction across the midline and rotation, so it stays within conventional posterior-approach precautions after arthroplasty, and patients with an arthroplasty are asked to check before mini squats, step ups, tandem stance (midline foot placement) and floor transfers (deep flexion); check extension and external rotation limits after an anterior approach, and active or resisted abduction after an anterolateral or lateral approach (the approach NICE 1.6.8 favors for hemiarthroplasty), against the surgeon's protocol. Screen at each visit for dislocation, loss of fixation (for example screw cut-out) or periprosthetic fracture, particularly after a new fall, head injury after a fall (especially on anticoagulant prophylaxis), stroke signs, deep vein thrombosis and pulmonary embolism, wound infection and sepsis, delirium, pressure injury, nerve symptoms including foot drop, and new leg length or rotation changes. Check that VTE prophylaxis under NICE NG89 (1.11.2: a month for fragility fractures of the pelvis, hip or proximal femur) is being taken as prescribed, and that falls and fracture liaison referrals have been made.
See a doctor promptly if
- Emergency: sudden severe pain in your hip or groin, sometimes with a clunk or pop, and you cannot move the leg or put weight on it, or the leg suddenly looks shorter or turned in or out. Do not try to walk on it or push it back into place. Keep still and call emergency services or go to an emergency department, and do not drive yourself. If part or all of your hip was replaced, it may have come out of its socket (dislocated), or the bone around it may have broken. If the break was fixed with screws, a nail or a plate, the fixing or the bone may have given way, and both need a medical team straight away.
- Emergency: your operated leg looks shorter than it did, or its foot turns in or out more than before, or the hip moves in an unusual way, even if the pain is not severe. Keep your weight off it and go to an emergency department straight away, and do not drive yourself. If you are in severe pain or cannot move the leg, call emergency services.
- Emergency: you have had a fall or an injury and now have severe hip pain, or you cannot walk or put weight on the leg. Call emergency services or go to an emergency department. This can be a sign of a broken hip (hip fracture).
- Emergency: you have just fallen and cannot get up, or you think you may have hurt your head, neck, back or hip. Stay where you are, keep warm and call emergency services, or get someone to call for you. If you got up and walked without trouble and only notice pain later, use the lines below.
- Emergency: you fell and cannot remember the fall or how it happened. Go to an emergency department straight away, and do not drive yourself. You may have blacked out or hit your head without knowing it.
- Emergency: after a knock to the head, being very drowsy or finding it hard to keep your eyes open, confusion, a fit (seizure), new weakness or numbness anywhere in your body, new trouble understanding, speaking, walking or keeping your balance, new problems seeing or hearing, clear fluid coming from your ears or nose, bleeding from your ears or bruising behind them, a black eye when your eye was not hit, a dent in your head or a wound with something stuck in it, or a change in behavior. Call emergency services straight away. These can be signs of an injury to the brain.
- Emergency: after a knock to the head, you were knocked out, even for a moment, you cannot remember what happened just before or after, you have had a headache ever since, or you are being sick (vomiting). The same applies, even if you feel fine, if you take medicine that thins your blood, other than aspirin on its own, have a bleeding or clotting condition, have had brain surgery in the past, or had been drinking alcohol or taking drugs when it happened. Go to an emergency department straight away, and do not drive yourself.
- Emergency: since your operation, you suddenly become short of breath, you get chest pain or pain in your upper back that may be worse when you breathe in, you cough up blood, your heart is beating very fast, or you faint. Call emergency services straight away, even if your leg looks normal. These can be signs of a blood clot in the lungs (pulmonary embolism).
- If chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
- Emergency: sudden confusion, for example you, or the person you care for, suddenly become muddled, much drowsier than usual or unable to follow what is said. Call emergency services or go to an emergency department straight away, without driving yourself. Sudden confusion can come from an infection, a stroke, a head injury or other causes that need treating quickly.
- Emergency: any sign of a stroke, even if it goes away. That means a face that droops on one side, an arm you cannot lift or keep up, slurred or muddled speech, weakness or numbness on one side of your body or face, sudden blurred vision, double vision or loss of sight, trouble swallowing, sudden dizziness with unsteadiness or falling over, a sudden severe headache, or a sudden fall where your legs give way but you do not black out (a drop attack). Call emergency services straight away.
- Same day: a calf or thigh that is newly swollen, warm, tender, red or darker than usual, has swollen veins that are sore to touch, or has a throbbing or cramping pain that does not fit your injury or condition, or that feels different from normal muscle soreness after exercise. This can be a sign of a blood clot (deep vein thrombosis), especially after surgery, an injury, time in a cast or boot, a long trip or a spell of being much less mobile than usual. Get medical advice the same day. If you are also short of breath or have chest pain, call emergency services.
- Same day: your wound becomes more red, hot, swollen or painful, starts to leak or ooze, has pus coming out of it or its edges start to come apart, or you have a high temperature or feel hot, cold or shivery. Contact your surgical team or get medical advice the same day. Redness can be harder to see on brown or black skin. If you feel very unwell, go to an emergency department. If you have a very high or very low temperature, shivering you cannot control, you are breathing very fast or finding it hard to breathe, you are confused or your speech is slurred, your skin, lips or tongue look blue, gray, pale or blotchy (on brown or black skin this can be easier to see on the palms of the hands or soles of the feet), or you have a rash that does not fade when you press it, call emergency services, as this can be sepsis.
- Same day: since your operation, the pain, redness, warmth, tenderness or swelling in your hip or leg is not getting better or is getting worse, for example the hip pain keeps building both when you move and when you rest, or you have a new throbbing or cramping pain in your hip or leg. Contact your surgical team or get medical advice the same day, as this can be a sign of infection, a blood clot or a problem with the repair.
- Same day: after a partial or full hip replacement, your hip clunks and feels as if it partly slipped out of place and went back, even if it settles straight away and your leg looks normal. Stop the exercises, avoid the movement that brought it on, and contact your surgical team or get medical advice the same day. If the leg then looks shorter or turned, or you cannot move it or put weight on it, call emergency services.
- Same day: sudden new dizziness, or feeling faint or unsteady, without any of the stroke signs above. Stop, sit down and get medical advice the same day. If you faint, it does not settle within a few minutes of sitting still, or you cannot stand or walk steadily, call emergency services.
- Same day: after a fall, you are in pain, have hurt yourself or feel unwell, or you were on the floor for an hour or more, without any of the emergency signs above. Get medical advice the same day, even if you managed to get up.
- Same day: new hip or groin pain after a fall, even a small one, if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time, even if you can still walk. Get medical advice the same day. A broken hip is not always obvious at first.
- Same day: a leg or foot that is getting weaker, for example your foot drags, catches on the ground or slaps down when you walk (foot drop). Get medical advice the same day. If the weakness is getting worse by the hour, go to an emergency department.
- Same day: new numbness, tingling or burning in your operated leg or foot, beyond the numb patch of skin around your scar. Contact your surgical team or get medical advice the same day. If it started after a fall or an injury, or your foot or toes turn cold, pale, blue or gray, call emergency services or go to an emergency department straight away, and do not drive yourself.
- Same day: you blacked out before the fall that broke your hip, or you cannot remember that fall, and nobody has checked why. Get medical advice the same day. A blackout needs its own check, especially if you are over 65 or it came without warning.
- Within a few days: a patch of skin on your heel, bottom, tailbone or hip that stays red when you press it (on brown or black skin it may look purple or blue), feels warm, spongy or hard, or turns into a blister or open sore. This can be a pressure sore (pressure ulcer), which is more likely while you move less than usual. Tell your doctor or nurse within a few days, and change position often. If the skin around it is hot, swollen or red, pus comes out of it, you have a high temperature or the pain is severe or getting worse, get medical advice the same day.
- Within a few days: you have fallen two or more times in the past year, or you keep tripping, stumbling or feeling that your legs might give way. Book an appointment with your doctor within a few days and ask about a falls assessment. Tell them about every fall, even the ones where you were not hurt.
- Routine: your walking or movement has stopped improving over a week or two, you still limp badly, or you cannot manage the exercises your team gave you, but your pain, redness and swelling are not getting worse. This is not an emergency, but ask your physio or surgical team for a review in the next week or two.
Common questions
How long does it take to recover from a broken hip?
The NHS says a broken hip usually takes several weeks or months to heal, sometimes longer, and that most people spend around 1 to 4 weeks in hospital. Swelling can last a few months or more, but it does get better with time (Gateshead Health). You may need a walking stick or frame when you get home, and some people need help from carers or other health professionals (NHS). How far and how fast you recover depends on how active you were before the fall, your other health problems and the operation you had.
When can you walk after hip fracture surgery?
Usually the day after. NICE advises a physio assessment and getting you moving on the day after surgery unless there is a medical reason not to, then at least once a day. OrthoInfo says most people get out of bed and start physical therapy the day after surgery. Surgeons aim for an operation that lets you put your full weight on the leg straight away (NICE). After screws, a nail or a plate, your doctor will tell you whether you can take full weight or need to limit it for a while (OrthoInfo).
Can you fully recover from a broken hip?
Many people get back to walking and looking after themselves, but not everyone gets back to how they were. The NHS says you may never get back the same strength and movement you had before the break, and OrthoInfo notes that older people often need more help with daily life afterward. Exercise does help. A Cochrane review of 40 trials found that programs aimed at walking and mobility after hip fracture surgery can improve mobility and walking speed compared with usual care. The gains after leaving hospital were small but meaningful (Fairhall 2022).
Is a broken hip the same as a hip replacement?
No. A broken hip is an injury, usually from a fall, and a hip replacement is one of the operations used to treat it. Depending on where the bone broke, the surgeon may fix it with screws, a nail or a plate, or replace the ball of the joint (a partial replacement, or hemiarthroplasty) or the whole joint (a total hip replacement) (NHS; NICE). A planned hip replacement for arthritis is a different situation, with its own program.
Why is my parent confused after hip fracture surgery?
Sudden confusion, called delirium, can follow a broken hip and an operation, and NICE asks hospital teams to look for it throughout the stay. The NHS says sudden confusion has many possible causes, such as an infection, and that urine infections are a common cause in older people. You know what is normal for your parent, so tell the ward staff straight away if they seem more muddled, drowsy or agitated than usual. At home, sudden confusion is an emergency.
When can I drive after a broken hip?
Gateshead Health's hip fracture leaflet says you will not be able to drive for at least 6 weeks after the operation. After that, once you can walk without any walking aid, you can drive when you feel safe to do an emergency stop and control the car. The same leaflet says you must tell your insurance company that you have had hip surgery. Check with your surgeon or doctor that you are fit to drive before you start again.
References
- National Institute for Health and Care Excellence. Hip fracture: management. NICE clinical guideline CG124. Published 22 June 2011, last reviewed 6 January 2023. https://www.nice.org.uk/guidance/cg124
- Australian and New Zealand Hip Fracture Registry (ANZHFR) Steering Group. Australian and New Zealand Guideline for Hip Fracture Care: Improving Outcomes in Hip Fracture Management of Adults. 2014. https://anzhfr.org/wp-content/uploads/2021/12/ANZ-Guideline-for-Hip-Fracture-Care.pdf
- National Institute for Health and Care Excellence. Venous thromboembolism in over 16s: reducing the risk of hospital-acquired deep vein thrombosis or pulmonary embolism. NICE guideline NG89. Published 21 March 2018, last updated 13 August 2019. https://www.nice.org.uk/guidance/ng89
- National Institute for Health and Care Excellence. Transient loss of consciousness ('blackouts') in over 16s. NICE clinical guideline CG109. Published 25 August 2010, last updated 21 November 2023. https://www.nice.org.uk/guidance/cg109
- Fairhall NJ, Dyer SM, Mak JC, Diong J, Kwok WS, Sherrington C. Interventions for improving mobility after hip fracture surgery in adults. Cochrane Database of Systematic Reviews. 2022;(9):CD001704. https://doi.org/10.1002/14651858.CD001704.pub5
- Latham NK, Harris BA, Bean JF, et al. Effect of a home-based exercise program on functional recovery following rehabilitation after hip fracture: a randomized clinical trial. JAMA. 2014;311(7):700-708. https://doi.org/10.1001/jama.2014.469
- Magaziner J, Mangione KK, Orwig D, et al. Effect of a multicomponent home-based physical therapy intervention on ambulation after hip fracture in older adults: the CAP randomized clinical trial. JAMA. 2019;322(10):946-956. https://doi.org/10.1001/jama.2019.12964
- Sherrington C, Fairhall N, Kirkham C, et al. Exercise to reduce mobility disability and prevent falls after fall-related leg or pelvic fracture: RESTORE randomized controlled trial. Journal of General Internal Medicine. 2020;35(10):2907-2916. https://doi.org/10.1007/s11606-020-05666-9
- NHS. Broken hip. Page last reviewed 29 July 2026. https://www.nhs.uk/conditions/hip-fracture/
- NHS. Complications of a hip replacement. https://www.nhs.uk/tests-and-treatments/hip-replacement/complications-of-a-hip-replacement/
- NHS. DVT (deep vein thrombosis). Page last reviewed 30 April 2026. https://www.nhs.uk/conditions/deep-vein-thrombosis-dvt/
- NHS. Pulmonary embolism. Page last reviewed 25 May 2023. https://www.nhs.uk/conditions/pulmonary-embolism/
- NHS. Sepsis. Page last reviewed 14 May 2026. https://www.nhs.uk/conditions/sepsis/
- NHS. Sudden confusion (delirium). Page last reviewed 28 May 2024. https://www.nhs.uk/symptoms/confusion/
- NHS. Pressure ulcers (pressure sores). Page last reviewed 6 July 2023. https://www.nhs.uk/conditions/pressure-sores/
- NHS. Head injury and concussion. Page last reviewed 29 May 2025. https://www.nhs.uk/conditions/head-injury-and-concussion/
- National Institute for Health and Care Excellence. Head injury: assessment and early management. NICE guideline NG232. 2023. https://www.nice.org.uk/guidance/ng232
- NHS. Symptoms of a stroke. Page last reviewed 12 September 2024. https://www.nhs.uk/conditions/stroke/symptoms/
- American Academy of Orthopaedic Surgeons. Hip fractures. OrthoInfo. https://www.orthoinfo.org/en/diseases--conditions/hip-fractures/
- Gateshead Health NHS Foundation Trust. Physiotherapy following hip fracture surgery. Patient information, last updated 15 July 2025. https://www.gatesheadhealth.nhs.uk/resources/physiotherapy-following-hip-fracture-surger/
- University Hospitals Plymouth NHS Trust. Hip dislocation. Patient information leaflet. https://www.plymouthhospitals.nhs.uk/display-pil/pil-hip-dislocations-4038/
- Royal Osteoporosis Society. Osteoporosis symptoms. https://theros.org.uk/information-and-support/about-osteoporosis-and-osteopenia/osteoporosis-symptoms/
Written and checked by the PocketPhysio editorial team. Last updated 2026-09-29.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.