
Pain under the shoulder blade: why one side hurts and what helps
Warning signs, and when to get help
Which pain this page is about
Start here, because two different pains get typed into the same search box.
This page is for pain you can put a hand on at one shoulder blade: on it, under its lower tip, along its inner edge, at the top corner where it meets your neck, or in the soft patch between the blade and the spine on one side only. If instead your pain sits in the middle, in the gutter of the spine with a blade either side of it, go to pain between the shoulder blades, which is written for that patch and its own cause list. People who feel it under both blades at once usually belong on that page too.
The distinction is not pedantry. A one-sided pain brings a different set of questions with it, starting with which side, and a midline pain brings a different one.
There are other routes off this page, so check these before you settle into the explanations. If the sore part is the shoulder joint itself, at the front or the outside, and it is lifting the arm that hurts rather than the patch behind it, shoulder pain when lifting your arm is written for that. If your neck is stiff or sore as well, or the ache at the blade changes when you turn or tip your head, the neck is the likeliest source and referred pain from the neck below is the part to read first.
The patterns that need urgent help
Read this before anything else, then get on with the rest of the page.
Call emergency services for chest pain, pressure or tightness that does not settle or that spreads to your arm, neck, jaw, stomach or back, and for pain in this area arriving with sweating, feeling sick, feeling light-headed or being short of breath. Those are the triggers on the NHS 999 list for chest pain, and the list carries no requirement that you were exerting yourself or that the pain be severe. Do the same for a sudden, severe pain in your chest or between your shoulder blades that feels sharp, stabbing, tearing or ripping. MedlinePlus describes that pain as beginning below the breast bone and then moving under the shoulder blades or to the back, which is how a tear in the main blood vessel from the heart usually announces itself, and it says the symptoms generally begin suddenly.
Breathing comes next. Sudden breathlessness, chest or upper back pain that is worse when you breathe in, coughing up blood, a very fast heartbeat or fainting all go to emergency services, even if your legs look completely normal. A sudden sharp or stabbing pain in one side of the chest or shoulder that came out of the blue and worsens on breathing in belongs there too: Asthma and Lung UK lists exactly that among the symptoms of a collapsed lung, and it puts sudden chest pain or discomfort on its own 999 list. A collapsed lung happens more readily in people who are tall and thin, who smoke, who are between 15 and 34, or who already have a lung condition.
Then the upper abdomen. Severe pain under the ribs on the right or in the middle of the tummy that spreads through to the back, with sickness, a high temperature or yellowing of the skin or eyes, needs emergency assessment for gallstones. The NHS puts tummy pain lasting more than 30 minutes at the urgent level even without those extras. Pregnancy changes this paragraph completely: if you are pregnant or had a baby in the last few weeks, pain just below your ribs, or pain high in your tummy that comes through to your back, your shoulder or your shoulder blade, goes to your maternity unit straight away and not into any explanation further down this page. The pregnancy section below says why, and the warning list carries the full version.
That is the chest, tummy and pregnancy group, and it is worth the two minutes. Spine, nerve and shoulder emergencies have their own lines further down, and a few are worth knowing the shape of now. New trouble walking, legs that feel stiff, heavy or weak, new trouble controlling your bladder or bowels, or new numbness in a band around your chest or tummy can mean pressure on the spinal cord, which is emergency services rather than an appointment. A shoulder that has changed shape or has locked so you cannot move the arm goes to an emergency department, and so does an arm or hand that turns cold, pale, blue or gray compared with the other side. Do not drive yourself to either.
Nothing on the list turns an ordinary sore blade into something dangerous. One group should not read it that way, though: if you have had cancer, now or in the past, or you have lost weight without trying, new pain here is checked rather than explained, and the warning list says how soon. The full warning set sits at the bottom of this page with a time frame on every line, and everything in between assumes none of it applies to you. If you have read this far and none of it is you, that is the common case, and the rest of the page is the ordinary explanation, starting with why only one blade hurts.
Why does only one shoulder blade hurt?
The shoulder blade has no bony anchor to your rib cage. Its only bony link to the rest of you runs through the collarbone, so it floats on the back of the chest wall held by muscles that run to the neck, the spine and the ribs, and it travels several inches up, down and around that wall as your arm moves. That arrangement gives it freedom and gives it no bony protection against a week of being held still in one position.
One-sidedness follows from how people live rather than from anything being wrong. You sleep on one side, carry on one shoulder, reach for the mouse with one arm, hold a child on one hip, and paint a ceiling with whichever arm is dominant. The joints, rib joints, muscles and nerve roots supplying the region are paired and work independently, so irritating one of them gives pain on one side only.
So one blade hurting is the common presentation, not the suspicious one. What makes one-sidedness worth a second look is the company it keeps, and the warning list at the foot of this page gives each of those combinations its own line.
What causes pain under the shoulder blade?
None of these is a diagnosis and more than one often applies to the same person. Pointing at the spot tells you less here than it would at the knee, because the same patch of skin reports trouble from the joints beneath it, the neck above it and the chest in front of it.
The joints and rib joints of the upper back
This is the usual answer. The part of the spine behind your chest, the thoracic spine, has 12 bones and each one meets a pair of ribs at small joints that move with every breath. The blade lies over the top of them. An irritated joint there is felt as a deep, dull ache a couple of finger widths out from the spine, worse after sitting, better once you have been moving for ten minutes, and sometimes sharp on a deep breath or a twist.
No test confirms it, so it stays a working explanation. The research underneath it is thin. Johansson and colleagues (2017) reviewed mid-back pain in the general population and found adult incidence lower than for the neck and lower back, and identified no studies at all of how adults recover or what predicts recovery. They were looking at incidence and prognosis rather than treatment, so the review does not say what helps a sore mid-back. What it says is that nobody has yet followed adults with this pain to see how it behaves. The upper back pain program and the facet joint pain page take this further.
Referred pain from the neck
This is the cause most often missed, and it is the reason a physio will examine your neck even when your neck feels fine. Tanaka and colleagues (2006) followed 50 patients with neck or scapular pain plus arm or finger symptoms, all treated by decompressing a single nerve root, and reported that the pain came before the arm symptoms in 70 percent of them and was relieved early after surgery in 92 percent. Where the pain sat tracked which root was involved: suprascapular pain went with C5 or C6, interscapular pain with C7 or C8, and pain at the blade itself with C8. Their conclusion is the useful part for this page, which is that pain in the scapular region can originate directly in a compressed root in the neck.
Be careful applying that to yourself. Every one of those 50 had arm or finger symptoms and went on to an operation, so the study says nothing about how common a nerve root is among everyone with a sore blade. The neck joints refer here as well, and Cooper and colleagues (2007) mapped referred pain in patients whose source had been confirmed by controlled injections, arguing that maps built that way guide clinicians better than maps drawn from pain-free volunteers.
What that means in practice is simple enough. An ache at the blade that changes when you turn or tip your head, with a stiff neck, usually belongs with the neck pain program or with neck pain on one side. Pain that also runs down the arm with pins and needles, numbness or weakness points at cervical radiculopathy.
Muscles that join the neck and spine to the blade
Two of them account for most of the sore spots people reach for with a thumb. One runs from the side of the upper neck down to the top inner corner of the blade, and the other pair runs from the spine to the inner edge. They are not usually damaged. They are sore because they have held one position for far longer than they are used to, or worked overhead for a day, and sore is not the same as torn.
The clinical story is nearly always a busy fortnight rather than an incident. More screen hours, a laptop on a sofa, a heavy bag on one shoulder, a long drive, a weekend of decorating, or a new pressing exercise in the gym. The working from home desk page covers the setup side, and the exercises below are aimed at the rest.
A shoulder that is working hard
The blade and the shoulder work as one unit, so a painful shoulder commonly produces a sore blade on the same side. An arm that catches partway up a lift gets hauled the rest of the way by the muscles around the blade and the neck, which then ache by the evening. Shoulder impingement and rotator cuff tendinopathy both do this, and shoulder impingement and neck pain covers the combination.
Sometimes the blade on the sore side also sits or travels differently from the other one. Plenty of pain-free people have the same thing, so it is not an explanation by itself, and the scapular dyskinesis page is straight about what is and is not known. Two versions need a doctor rather than a program: an inner edge that lifts markedly clear of the ribs, and a blade that started standing out at the same time as the arm went weak. The second of those is on the same-day list at the foot of this page, because a blade that stands out as the arm weakens points at a nerve to one of the muscles holding the blade on the rib cage rather than at the muscle itself.
Something else here is not a program either: a new lump, swelling or hard area you can feel over the blade or the shoulder, whether or not it hurts. UK shoulder surgeons treat a mass or swelling at the shoulder as a reason for urgent specialist referral, so it has its own line at the foot of this page.
The chest wall, the nerves at the base of the neck, and the shape of the upper back
A few smaller causes are worth naming. Pain where the ribs meet the breastbone at the front can be felt round at the back as well, which is costochondritis. The nerves and vessels for the arm pass from the neck under the collarbone, and squeezing anywhere along that route gives arm symptoms with a blade ache on the same side, which is thoracic outlet syndrome. And a back that sits rounded, whether that is simply your build or a change in the bones over the years, gives these muscles a longer working day, which is the kyphosis page.
Shoulder blade pain on the left side and the right side
Side changes the odds and decides nothing. Both sides have identical joints, ribs, muscles and nerve roots, so the mechanical causes are equally likely either way, and most pain on either side is mechanical.
Left shoulder blade pain is the phrase people search when they are worried about the heart, and that worry is reasonable enough to answer plainly. Cardiac pain is normally felt in the chest as well, and the NHS 999 triggers are built around that: chest pain or discomfort that does not go away, pain spreading to the arm, neck, jaw, stomach or back, or chest pain with sweating, sickness, light-headedness or breathlessness. Pain at the left blade alone, with a clear chest, that changes when you move your arm or turn, and that a thumb can find, is behaving mechanically. Treat that as a guide and not a test, because the NHS list has no movement rule and no exertion rule in it, and anything matching the list is urgent regardless of what you were doing.
Right-sided pain has its own short list. Severe pain under the right ribs or in the middle of the tummy that comes through to the back raises the gallbladder, especially with sickness, and the NHS gives it the urgent and emergency routes in the warning list at the foot of this page. The same part of the body matters in pregnancy for a different reason, which the pregnancy section below covers. Pain high on the right over the blade, with none of that, is as ordinary as the same pain on the left.
One pattern is not side-specific and catches people out. A burning, tingling or painful band of skin on one side of the back or chest, with nothing to see, can be shingles several days before any rash appears, because the NHS lists a tingling or painful feeling in an area of skin among the first signs and says a rash usually follows a few days later. The treatment window is short, which is why that line is on the same-day list.
Pain under the shoulder blade when you breathe in, cough or sneeze
Pain that sharpens on a deep breath usually has a mechanical explanation, and the reason is anatomical rather than reassuring guesswork. Your ribs move with every breath and the joints at the back of them lie directly under the blade, so a sore joint or muscle there gets loaded and unloaded all day whether you rest or not. The mechanical version is reproducible: the same depth of breath gives the same pain, one spot is tender to press, and coughing or twisting repeats it.
What it is not is a green light on its own. Three things that are not mechanical also hurt on breathing in, and each has a different urgency. The NHS describes pleurisy as sharp chest pain when you breathe in, worse on coughing, sneezing or moving, that may spread to the shoulders and back, and that is a same-day call. A sudden sharp or stabbing pain in one side of the chest or shoulder out of the blue, worse on breathing in, is an emergency, for the collapsed lung and clot reasons above. And a cough that has outstayed three weeks, breathlessness that is getting worse, repeated chest infections or a hoarse voice puts this pain in a different conversation, because the NHS lists chest or shoulder pain among the main symptoms of lung cancer alongside those.
The cough and the sneeze in that heading need an answer of their own, because for some readers they are the cause rather than the aggravation. The NHS says it plainly on its osteoporosis page: a cough or a sneeze is sometimes enough on its own to break a rib, or to make one of the bones of the spine partly collapse. So if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time, and this pain arrived in one spot on a rib, the blade or the breastbone during a coughing fit, a sneeze, a lift or a bend, treat it as a possible break rather than a strain. Get medical advice the same day, and leave the open book stretch, the rhomboid stretch and the shoulder blade exercises alone until someone has checked it, because those load a rib or a spine bone that may be broken. A thin rib breaks under very little force and the sore spot sits right where an ordinary strain would be, which is why this one is not safe to work out for yourself.
So the sorting question is not whether breathing hurts. It is whether breathing is the only thing that changes it, whether it came on suddenly, and whether your chest is otherwise behaving normally.
Shoulder blade pain that radiates down the arm
Pain that leaves the blade and travels into the arm changes the assessment, because it moves the likely source up to the neck or out to the nerves and vessels under the collarbone. The useful detail is what travels with it. Pain alone is less specific than pain with pins and needles, numbness, or an arm that tires or feels heavy, and those point toward an irritated nerve root or a squeeze along the route to the arm. Our pages on cervical radiculopathy and on numbness, tingling and pain down the arm go through it properly.
The combinations below do not wait for a routine appointment, and all of them are in the warning list at the foot of this page. An arm or hand that is getting weaker, or hand muscles that look thinner than on the other side, needs advice the same day. Hands that have slowly become clumsy need the same, and that is the one people explain away: buttons, coins, keys and zips have got harder, or you have started dropping things, and numbness in both hands belongs with it. Pins and needles or numbness in both arms at once, rather than one, counts too, because all of these can mean pressure on the spinal cord in the neck.
Speed changes the route. If the clumsiness or the numbness is getting worse quickly, call emergency services rather than waiting for the day. And an arm that turns cold, pale, blue or gray compared with the other, or swells and goes dusky with veins standing out, is an emergency department problem rather than an exercise problem. Get medical advice the same day if anything travels into the arm, or the arm feels weak or numb, and nobody has looked at it yet.
Why does my shoulder blade hurt after sleeping?
Hours in one position with no variety is the ordinary answer, and the upper back is stiffest first thing for the same reason the lower back is. Sleeping on your front with your head turned keeps the neck rotated and one set of blade muscles lengthened all night. A pillow that is too high or too flat shifts the angle of the neck, and the muscles running from the neck to the top corner of the blade take up the difference. Curling tightly on one side holds the blade forward around the ribs for hours.
Stiffness and a one-sided ache that ease within 15 to 30 minutes of getting up and moving is the pattern to expect, and the stretches below are reasonable for it. Try a night on your side with a pillow that keeps your head level rather than tipped, and a second pillow to stop you rolling onto your front. There is no good evidence naming one mattress or pillow for this region, so judge a change by how you feel after a fortnight rather than by the box it came in. If you keep waking with a stiff neck as well, stiff neck after sleeping is the page for that.
Stiffness that runs well past half an hour most mornings is a different pattern, and it is worth saying so rather than filing it with ordinary morning creak. Ask your doctor whether it could be inflammatory back pain, particularly if you also get pain in your low back or buttocks, it began before you were 45 and has gone on for more than three months, it wakes you in the second half of the night, or movement eases it and rest brings it back. Those are the features NICE uses to decide who needs a rheumatology assessment for axial spondyloarthritis (NG65), and the ankylosing spondylitis program goes through them.
Pain that wakes you, that is worse at night than in the day, or that does not ease at all when you rest is a different matter, and the warning list gives it a time frame. Two things move that time frame from the next few days to the same day: having had cancer, now or in the past, and losing weight without trying. The section on a cancer history below sets out what that means.
If you are pregnant
Back and rib pain in pregnancy is assessed and managed differently, so this page gives no exercise advice for it. Use the pregnancy back and pelvic pain program and let your midwife, doctor or maternity physio lead what you do.
One thing is worth knowing now rather than looking up later. The NHS lists a severe headache that simple painkillers do not shift, vision problems such as blurring or flashing lights, pain just below the ribs, vomiting, heartburn that heartburn medicines do not settle, sudden swelling of the face, hands or feet, and feeling very unwell as symptoms of pre-eclampsia. Contact your maternity unit straight away if you get any of them, or get urgent medical help if you cannot reach them, and the same applies in the days and weeks after the birth. Pain just below the ribs is the one that reaches a physio dressed as an upper back or rib complaint, which is why the full line has its own place in the warning list, under the heading "Get help now, day or night", rather than sitting among the rest.
Pain under the ribs on the right that comes through to your back, your shoulder or your shoulder blade takes the same route. Where pre-eclampsia or HELLP syndrome causes bleeding in or around the liver, pain high in the tummy is the commonest symptom and shoulder pain is reported as well (Augustin and colleagues, 2022). That combination goes to your maternity unit rather than into a program for a stiff upper back.
If you have had cancer, now or in the past
A cancer diagnosis, current or finished with, changes how new pain in this area is handled, and that is worth knowing before you read the rest of the page. New upper back or shoulder blade pain gets checked rather than explained. Get medical advice the same day and say that you have had cancer, or contact your cancer team the same day if you are being treated now. The same goes for pain that is worse at night or does not ease at all when you rest, and for losing weight without trying.
One combination does not wait. If your back or neck pain feels like a tight band around your body, or you have new or worsening pain spreading down an arm or leg, weakness, numbness, pins and needles or a loss of feeling in your arms or legs, trouble walking, or trouble controlling your bladder or bowels, call your cancer team's emergency number straight away, or go to an emergency department if you do not have one or cannot get through. Those symptoms count on their own, with or without back or neck pain. That can be cancer pressing on the spinal cord. NICE lists bladder or bowel problems, difficulty walking, limb weakness, numbness or altered sensation and nerve root pain as the signs to act on, and tells clinicians to treat them as an oncological emergency and make contact immediately (NG234).
None of that means a sore blade in someone who has had cancer is usually the cancer. It means the checking happens first and the explanations come afterward, which is the opposite of the order the rest of this page uses.
What helps at home
Keep moving. Staying active and carrying on with daily activities, and not taking to bed for long periods, is what the NHS advises for back pain, and nothing about the upper back makes a case for anything else. Rest as a strategy tends to make the first movements of the next day harder.
Break up the static spells rather than chasing the perfect setup. A screen you have to twist to see, a laptop low on your knees, or a chair that leaves you perching is worth fixing, because each forces one position on you. Beyond that, standing up every half hour buys more than another accessory. Swap the shoulder bag for a backpack for a few weeks, and split a big carry into two trips.
Heat suits most people here, wrapped in a towel and not slept on. The NHS names a heat pack or hot water bottle for joint stiffness and muscle spasm and an ice pack for pain and swelling, so on its own account the two do different jobs. Either is reasonable for a sore blade.
Breathe into it rather than away from it. People with pain on a deep breath start taking shallow ones, the rib joints stop moving through their range, and the next deep breath hurts more. A few slow, fuller breaths every hour, going only as deep as is tolerable, keeps those joints moving.
If your fingers or the skin around your mouth start to tingle, or you feel light-headed or spaced out, that can mean you are breathing too fast or too deeply, so stop and let your breathing go back to normal. If it has not settled within a few minutes, get medical advice the same day. If you faint, or the numbness or tingling is on one side of your face or body, call emergency services, even if it goes away.
Painkillers are a question for a pharmacist or doctor rather than a physio. If pain is stopping you sleeping night after night, say so at your appointment instead of working around it.
Exercises and stretches for pain under the shoulder blade
Six below, in the order to use them. The first three restore movement, in the muscle joining your neck to the top corner of the blade, in the muscles along its inner edge, and in the turn of the upper back itself. The last three build the muscles that hold the blade on the rib cage and draw it down and in, which is the half people skip and the part that keeps the gain. Give the first three a week on their own, then add the last three.
Go through these checks before you begin. Find yourself in them if you can, and do the asking before the exercise rather than after it.
If this pain started after a car accident, a fall, a blow to the back or any other injury, get it looked at by a doctor or physio first and read the warning signs below. The same goes if it arrived in one spot on a rib, the blade or the breastbone during a cough, a sneeze, a lift or a bend, and you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time. Get that checked the same day, and leave out the open book stretch, the rhomboid stretch and the shoulder blade exercises until it has been, because those load a rib or a spine bone that may be broken.
If your shoulder has dislocated before or feels loose, check with your physio before you start and ask how far to reach. After shoulder surgery, including a rotator cuff repair, or after a shoulder fracture or dislocation, follow your surgeon's or physio's plan, and do only the movements and range they have cleared. Many plans allow only passive movement at first, where the arm is moved for you and its muscles stay relaxed.
After neck surgery or a broken bone in the neck, check with your surgeon or physio before you start. If you have had surgery on your spine in recent months, get the go-ahead from your surgical team or physio first. After recent heart or chest surgery, get your surgeon's or surgical team's okay first, because pushing both arms forward pulls across the healing breastbone and the chest wound. If the breastbone clicks, grinds, shifts or feels as if it is moving while you do it, stop, and contact your surgical team the same day.
Rounding the upper back forward is a movement physios often limit with low bone density (osteoporosis) or after a fracture in the spine, so ask yours before you start. With osteoporosis or a past fracture in your spine or ribs, talk to your physio before letting the arm open all the way, since a full twist is often limited. The UK consensus statement on exercise for osteoporosis recommends spinal extension exercise and says to avoid postures involving a high degree of spinal flexion, in exercise and in daily life (Brooke-Wavell 2022), which is why nothing here asks you to fold a long way forward under load.
If you have had a hip replacement, get the go-ahead from your surgeon or physio before you try the open book stretch. Resting the top knee forward on its support bends that hip to about a right angle and lets the knee drop across the middle of your body, and many surgeons ask you to avoid that for the first months after some operations.
If you have rheumatoid arthritis or Down syndrome, or have been told the top of your neck is unstable or there is pressure on the spinal cord in your neck, ask your physio before you start. They may want you to leave out the hand that guides your head at first. If you have neck pain that spreads into your arm, ask your physio before you start.
One of the six asks you to lie face down, and that is the position some people cannot use. If lying flat leaves you breathless, ask your physio for a version done sitting or standing instead, and get the breathlessness itself looked at rather than working around it. The NHS puts feeling breathless when you lie down at its urgent level, through an urgent doctor's appointment or NHS 111, not at the routine one.
If you are pregnant, ask your physio for a version that does not need you to lie on your stomach, and use the pregnancy back and pelvic pain program with your midwife, doctor or maternity physio leading. If you have high blood pressure, breathe steadily through every hold and never hold your breath.
Exercises that can help
Before any of these, go through the checks just above this list. They cover a recent injury, low bone density, your shoulder, your neck, surgery to the spine, chest or hip, lying face down, pregnancy and blood pressure, and if one of them is you, the check comes before the exercise. These six take a different route from the between-the-blades program, because the muscles that matter at one blade are the ones joining it to the neck and to the rib cage. You need a chair, some floor and a bed or table you can lie face down on. As a rough guide, the levator scapulae stretch is a 15 to 30 second hold, 2 to 3 times on each side, once or twice a day; the rhomboid stretch is 2 to 4 holds of 15 to 30 seconds, once or a few times a day; the open book is 5 to 10 slow repetitions on each side, pausing a few seconds at the open position, once or twice a day; the serratus punch often starts at 2 to 3 sets of 10 reaches with a short hold and no weight in the hand, once a day; prone scapular retraction at 2 to 3 sets of 10 to 15, holding each squeeze for 3 to 5 seconds, once or twice a day; and shoulder blade depression at 10 to 15 slow repetitions on each side, 1 to 2 sets, once or twice a day. Those are daily doses, not targets to beat, and nothing here gets better faster for being done more often. The dose on each exercise page is the one to follow, and your physio will adjust this. Do both sides unless your physio has told you otherwise, and judge the sore side against the other one rather than against how it used to feel.
 Levator scapulae stretch
 Rhomboid stretch
 Open book stretch
 Serratus punch
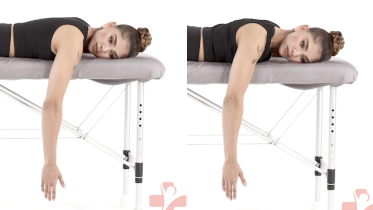 Prone scapular retraction
 Shoulder blade depression
Expect tired muscles around the blade and across the side of the ribs, and judge the dose by the next morning rather than by how it feels during the set. No worse means it was about right. Clearly worse means it was too much for this week, so halve it and build again. When the strength work starts to feel easy rather than effortful, each exercise page has its own way of making it harder, and that is the next step rather than piling on repetitions or doing the lot three times a day. Give it a few weeks before you judge the whole thing, and if nothing has shifted by then, book the appointment rather than running the same week again.
Stop the session and go to the warning signs if a sharp pain appears around the ribs, if anything travels into your arm as pain, numbness or tingling, if your hand goes numb or stays tingling after you stop, or if your legs feel weak or unsteady afterward. If you feel dizzy or lightheaded as you round forward or come back up, stop, sit down and let it pass. If it keeps happening, get medical advice the same day before you try again, and call emergency services if it does not settle within a few minutes of sitting still. If you faint while exercising, call emergency services, even if you feel fine again quickly. Pain that gets sharper as you reach rather than easing is a reason to stop that exercise, not to push on.
If chest pain, pressure or tightness does not ease quickly when you rest, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, feeling sick, feeling light-headed or being short of breath, call emergency services straight away, as this can be a heart attack. If it eases quickly and none of these happen, get medical advice the same day, and do not exercise again until you have been checked.
When to see a physio (physical therapist)
Book an appointment if the pain has not improved after a few weeks of staying active and changing the obvious things, if it comes back every busy week, or if it is getting in the way of work or sleep. The NHS puts three of its own on that list for back pain: no improvement after treating it at home for a few weeks, pain that is stopping your day-to-day activities, and being worried about it or struggling to cope. It adds one that applies directly here, which is that pain coming from the top of your back rather than your lower back is worth taking to a doctor, so do that first if nobody has looked at this yet. Arm symptoms move everything forward: tingling, numbness, an arm that tires quickly or one that feels heavy deserves an earlier look, and an arm that is getting weaker needs advice the same day.
A first appointment goes wider than the sore spot. Your physio will ask how your breathing feels, how your health is in general, what you were up to when the pain started, and whether anything apart from movement makes any difference to it. The hands-on part then covers your neck, your upper back, your ribs, your shoulder, and how the blade travels as you lift your arm. healthdirect's upper back pain page names unexplained weight loss, pain on breathing deeply, a fever, limited movement and feeling unsteady among the reasons to see a doctor rather than treat it yourself, and screening for the rarer serious causes is a normal part of a first appointment rather than a sign anyone is worried.
Some signs should not wait: read the warning signs section on this page and act on the timing given for each line, because they are not all at the same level of urgency.
Related exercise programs
Warning signs
Get emergency help now
- Emergency: chest pain, pressure or tightness, which may spread to your arm, neck, jaw, stomach or back, or upper back pain that comes with shortness of breath, sweating, feeling sick or feeling light-headed. Call emergency services straight away, as this can be a heart attack. The same applies to sudden, severe pain in your chest or between your shoulder blades that feels sharp, tearing or ripping, as this can be a tear in the main blood vessel from the heart (aortic dissection).
- Emergency: you suddenly become short of breath, you get chest pain or pain in your upper back that may be worse when you breathe in, you cough up blood, your heart is beating very fast, or you faint. Call emergency services straight away, even if your leg looks normal. These can be signs of a blood clot in the lungs (pulmonary embolism).
- Emergency: a sudden sharp or stabbing pain in one side of your chest or shoulder that is worse when you breathe in. Stop and call emergency services, and say what you were doing. This can be a collapsed lung (pneumothorax) or a blood clot in the lungs, and both need treating quickly.
- Emergency: a racing, pounding, fluttering or irregular heartbeat that does not settle when you rest, or that comes with dizziness, feeling faint or fainting, chest pain or shortness of breath. Call emergency services straight away. If it has already stopped, get medical advice the same day.
- Emergency: you are struggling to breathe, for example you are gasping, choking or cannot get your words out, or your lips or skin turn very pale, blue or gray (on brown or black skin this can be easier to see on the palms of the hands). Call emergency services straight away.
- Emergency: sudden, severe pain in your tummy, pain that spreads from your tummy to your back while you are being sick, a very high temperature or feeling hot, cold or shivery with tummy pain, or skin or whites of the eyes that turn yellow. Call emergency services or go to an emergency department straight away. These can be signs of a problem with gallstones. Pain in the middle of your tummy or under your ribs on the right that lasts longer than 30 minutes, without these signs, needs medical advice the same day.
- Emergency: new problems walking, for example your legs feel stiff, heavy or weak or you have become unsteady on your feet, new trouble controlling your bladder or bowels, or new numbness or pins and needles in a band around your chest or tummy, or below it. Call emergency services or go to an emergency department straight away. These can be signs of pressure on the spinal cord in the upper back.
- Emergency: new problems walking, for example your legs feel stiff, heavy or weak or you have become unsteady on your feet, new trouble controlling your bladder or bowels, or hands that suddenly become clumsy, for example you can no longer do up buttons. Call emergency services straight away. These can be signs of pressure on the spinal cord in the neck.
- Emergency: numbness, tingling or altered feeling around or under your genitals, between your inner thighs, or around your bottom (anus), for example it feels different when you wipe after using the toilet. Call emergency services or go to an emergency department straight away. This can be a sign of pressure on the bundle of nerves at the base of the spine (cauda equina syndrome), which needs emergency treatment.
- Emergency: you find it hard to start peeing, cannot pee, cannot feel yourself peeing or cannot control when you pee, or you do not notice when you need to poo or cannot control when you poo, and this is not normal for you. The same applies to a new change in how your genitals feel during sex, or new trouble getting an erection or ejaculating. Call emergency services or go to an emergency department straight away. These can also be signs of cauda equina syndrome.
- Emergency: sciatica in both legs, or pain, tingling, numbness or weakness in both legs. The same applies if you lose feeling in one leg. Call emergency services or go to an emergency department straight away.
- Emergency: you have had cancer, now or in the past, and your back or neck pain feels like a tight band around your body, or you have new or worsening pain spreading down an arm or leg, weakness, numbness, pins and needles or a loss of feeling in your arms or legs, trouble walking, or trouble controlling your bladder or bowels. Those symptoms count on their own, with or without back or neck pain. Call your cancer team's emergency number straight away, or go to an emergency department if you do not have one or cannot get through. This can be cancer pressing on the spinal cord (metastatic spinal cord compression), which needs treatment straight away.
- Emergency: back or leg pain that started after a serious accident, such as a car crash or a fall from a height, or back pain with chest pain. Call emergency services. If the pain started straight after the accident, keep still while you wait.
- Emergency: new neck or back pain after a fall, a knock or a jolt, even a minor one such as a trip or a sudden stop in a car, if you have a condition that stiffens the spine, such as ankylosing spondylitis. Call emergency services or go to an emergency department straight away, do not drive yourself, and tell the staff about your spine condition, so they keep your neck and back in their usual position. A stiff spine can break after a small injury, and the break is easy to miss at first. If the pain started straight after the injury, or you also have numbness, tingling or weakness in your arms or legs, keep still and call emergency services.
- Emergency: back pain with a fever, or you feel hot, shivery or very unwell, and you also have new weakness, numbness or tingling in one or both legs, or new trouble with your bladder or bowels. Call emergency services or go to an emergency department straight away. This can be an infection pressing on the nerves in the spine (spinal epidural abscess), which needs emergency treatment.
- Emergency: the shoulder feels as if it has slipped out of place, looks a different shape or suddenly locks so you cannot move the arm, or the pain is severe after a fall or an injury. Go to an emergency department straight away, without driving yourself, and do not try to put the shoulder back in yourself.
- Emergency: your arm, hand or fingers turn cold, pale, blue or gray compared with the other side. Call emergency services or go to an emergency department straight away, and do not drive yourself. The blood supply to the arm may be blocked.
Get help now, day or night
- You are pregnant or had a baby in the last few weeks and have a severe headache that does not go away with simple painkillers, problems with your vision such as blurring or flashing lights, pain just below your ribs, vomiting, heartburn that does not go away with heartburn medicines, sudden swelling of your face, hands or feet, or you feel very unwell. Contact your maternity unit straight away, or get urgent medical help if you cannot reach them. These can be signs of pre-eclampsia, which can develop in the days or weeks after the birth and needs checking immediately. The same applies to a headache after an epidural or spinal anesthetic that gets worse when you sit or stand up and eases when you lie down. Call emergency services if you have a fit (seizure) or a headache that came on suddenly and is very severe. Call emergency services too if you have a headache with a stiff neck and either a high temperature or bright light hurting your eyes, as this can be meningitis.
- You are pregnant or had a baby in the last few weeks and have pain under your ribs on the right, or pain high in your tummy, that spreads through to your back, your shoulder or your shoulder blade. Contact your maternity unit straight away, or get urgent medical help if you cannot reach them. Call emergency services if the pain is severe, if it came on suddenly, or if you feel faint. Upper tummy pain is the commonest symptom when pre-eclampsia or HELLP syndrome causes bleeding in or around the liver, and shoulder pain is reported as well (Augustin and colleagues, 2022). Do not treat pain in this pattern as a muscle or rib problem until a maternity team has seen you.
Get help today
- Same day: a burning, tingling or painful patch of skin on one side of your back, chest or tummy, with or without a rash of blisters on the same side. Get medical advice the same day, from your doctor or NHS 111, if you are pregnant, you are breastfeeding and the rash is on your breasts, you have a severely weakened immune system, you are 17 or younger, the rash is on your eye or your nose, or your vision has changed, because shingles around the eye can affect your sight. Otherwise see a pharmacist or doctor within a day or two, as treatment for shingles works best when it starts within 3 days of the rash appearing.
- Same day: sharp pain in your upper back or around your ribs that has been coming and going when you breathe in or cough, or back pain with a cough, a high temperature or yellow or green mucus. Get medical advice the same day. These can be signs of inflammation of the lining of the lungs (pleurisy) or a chest infection. If the pain came on suddenly, or you find it hard to breathe, call emergency services straight away.
- Same day: sharp pain in your chest, ribs or upper back that has not got better after a few days, or you are feeling short of breath regularly. Get medical advice the same day. The NHS puts both of these at the urgent level for pleurisy.
- Same day: pain under your shoulder blade, in your ribs or in your breastbone that started with a fall, a blow to the chest or back, a crush, or a seatbelt in a car accident, rather than coming on by itself. Get medical advice the same day, and do not start these exercises until your chest and back have been checked, because the same knock can crack a rib or the breastbone and the sore spot sits right where an ordinary strain would be. Call emergency services or go to an emergency department straight away if the injury was a serious accident such as a car accident, your breathlessness is getting worse, your chest pain is getting worse, you have pain in your tummy or your shoulder, or you cough up blood, as a broken rib can damage something else such as a lung, the liver or the spleen. Do not drive yourself to hospital: ask someone else to drive you, or call an ambulance (NHS).
- Same day: new pain in one spot on your ribs, your shoulder blade or your breastbone after a minor fall, a knock, a cough, a sneeze, a lift or a bend, or pain in one spot that keeps getting worse with no injury at all, if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time. Get medical advice the same day. A thin rib can break under very little force, and the NHS says a cough or a sneeze can be enough to break a rib or to partly collapse one of the bones of the spine. Until it has been checked, leave out the open book stretch, the rhomboid stretch and the shoulder blade exercises, because those load a rib or a spine bone that may be broken.
- Same day: your arm or hand swells, turns blue, dusky, red or darker than usual, or feels heavy, tight, warm or tender, or has a throbbing or cramping pain that feels different from normal muscle ache. The veins over your shoulder, chest or arm may stand out or be sore to touch, and it often starts after hard or repeated use of the arm. Stop the exercises and go to an emergency department the same day, and do not wait to see if it settles. This can be a blood clot in the main vein under the collarbone (venous thoracic outlet syndrome) or elsewhere in the arm, which needs treatment quickly. If you are also short of breath or have chest pain, call emergency services.
- Same day: an arm or hand that is getting weaker, or muscles in your hand that look thinner or flatter than on the other side. Get medical advice the same day.
- Same day: hands that have slowly become clumsy, for example trouble doing up buttons or dropping things, or numbness in both hands. Get medical advice the same day. These can be signs of pressure on the spinal cord in the neck (cervical myelopathy). If the clumsiness or numbness gets worse quickly, call emergency services straight away.
- Same day: pain or tingling in both arms at the same time, rather than in one. Get medical advice the same day. This can also be a sign of pressure on the spinal cord in the neck.
- Same day: an electric shock feeling runs down your back or into your arms or legs as your head bends forward. Stop and get medical advice the same day.
- Same day: pins and needles in your arm or hand that do not go away after you stop, or part of your arm or hand goes numb. Get medical advice the same day.
- Same day: pins and needles in an arm together with your back, neck or arm pain, or an arm that feels heavy or weak, and nobody has checked it yet. Get medical advice the same day.
- Same day: sudden, very bad shoulder pain, or you suddenly cannot lift or move your arm at all. Get medical help the same day.
- Same day: the shoulder is hot, red and swollen, or you have a fever or feel unwell. This can be a joint infection, which needs treatment quickly. Go to an emergency department the same day, and call emergency services if you feel very unwell.
- Same day: the pain started after a fall, a pull or another injury, especially if the arm has been weak since, for example you cannot lift it out to the side or hold it up. This can be a broken bone or a torn tendon. Get medical advice the same day, and say how it happened and that the arm has been weak since, because UK shoulder surgeons advise urgent referral for a rotator cuff tear caused by an injury.
- Same day: severe pain in both shoulders that has come on recently. Get medical advice the same day.
- Same day: back pain after a minor fall or strain if you are older, have low bone density (osteoporosis) or have taken steroid tablets for a long time. Get medical advice the same day.
- Same day: back pain that comes on suddenly after lifting, bending, a cough or a sneeze, even without a fall, if you have low bone density (osteoporosis). Get medical advice the same day. This can be a sign of a broken bone in the spine (vertebral fracture). Stop the exercises until you have been checked.
- Same day: severe pain that comes on suddenly or is getting worse quickly. Get medical advice the same day.
- Same day: back or leg pain with a fever, or you feel hot, cold, shivery or generally unwell. Get medical advice the same day, and go to an emergency department if you feel very unwell.
- Same day: new upper back or shoulder blade pain and you have had cancer, now or in the past, or you have lost weight without trying. Get medical advice the same day and mention it. If you are being treated for cancer now, contact your cancer team the same day.
- Same day: you have back pain and have lost weight without trying. Get medical advice the same day and mention the weight loss.
- Same day: pain that is worse at night, or does not ease at all when you rest. If you have had cancer, now or in the past, or you have lost weight without trying, get medical advice the same day.
Book an appointment
- Within a few days: upper back or shoulder pain together with a cough that has lasted more than 3 weeks, breathlessness that is getting worse, chest infections that keep coming back, or a hoarse voice, especially if you smoke or used to smoke. See your doctor within a few days and mention it. If you cough up a few spots or streaks of blood, get medical advice the same day. If it is more than that, or you also find it hard to breathe, have a very fast heartbeat or have pain in your chest or upper back, call emergency services.
- Within a few days: pain that is worse at night, or does not ease at all when you rest. See your doctor within a few days.
- Within a few days: a new lump, swelling or hard area you can feel over your shoulder blade, your shoulder or the muscles around them, whether or not it hurts, and particularly if it is getting bigger. See your doctor within a few days and ask for it to be examined rather than watched. UK shoulder surgeons list a mass or swelling at the shoulder as a reason for urgent referral to a specialist within 2 weeks, and NICE asks for an urgent ultrasound scan for any unexplained lump that is getting bigger. For a child or teenager with a swelling over the bone, or with pain here that has no clear cause and is not settling, get medical advice the same day instead, because NICE asks for an X-ray within 48 hours at that age.
- Routine: back pain that comes from the top of your back, between your shoulders, rather than your lower back, and has not been checked, or back pain that is worse when you sneeze, cough or poo, or comes with a lump or swelling, or a back that has changed shape. Book an appointment with your doctor, as the NHS advises, and have it checked before you start this program. If the pain came on suddenly, get medical advice the same day.
Common questions
What causes pain under the shoulder blade?
Four explanations cover most of it, and a physio works through them in roughly this order. The joints and rib joints of the upper back, which hurt in a patch beside or beneath the blade and change with position. A nerve root in the neck, which Tanaka and colleagues (2006) showed can produce pain felt in the scapular region before anything reaches the arm. The muscles joining the neck and spine to the blade, which get sore after a week of one posture or a new overhead job. And the shoulder itself, since an arm that hurts partway up a lift recruits the muscles around the blade to help it. Referred pain from the chest and upper abdomen is the group the warning signs on this page exist for, and it is the smallest of them, not the likeliest.
When is shoulder blade pain serious?
When it travels with company. Pain in this area that arrives with chest pressure or tightness, spreads to your arm, neck, jaw, stomach or back, or comes with sweating, sickness, light-headedness or breathlessness is an emergency, and so is a sudden severe pain described as sharp, tearing or ripping. Sudden breathlessness, coughing up blood, a very fast heartbeat or fainting is an emergency whatever your leg looks like. A sudden sharp or stabbing pain in one side of the chest or shoulder that worsens on breathing in is also one, because Asthma and Lung UK lists that among the symptoms of a collapsed lung and puts sudden chest pain on its 999 list. Below those, more than twenty separate things on this page earn a same-day call rather than an ambulance, so read the list rather than trusting a summary. Four of the commonest are a fever, a new weak or numb arm, a burning patch of skin on one side, and pain that began with a minor knock or strain. Injury does not always sit at that level, though. A serious accident, a shoulder that has changed shape or locked, or severe pain straight after a fall goes higher, to emergency services or an emergency department, and the list says so on each line. Some signs should not wait: read the warning signs section on this page and act on the timing given for each line, because they are not all at the same level of urgency.
Why does it hurt under my shoulder blade when I breathe in?
Usually because the ribs move with every breath. Each rib meets the spine at small joints just under the blade, and a joint or muscle that is already sore gets loaded again on every breath, whether you like it or not. That version is reproducible: the same depth of breath hurts the same amount, pressing on one spot finds it, and a twist or a cough does the same thing. Two other explanations are not mechanical and have their own urgency. The NHS describes pleurisy as sharp chest pain on breathing in, worse with coughing, sneezing or moving, that may spread to the shoulders and back, and that needs a same-day opinion. A sudden sharp or stabbing pain in one side of the chest or shoulder that came out of nowhere and is worse on breathing in needs emergency services, because that pattern can be a collapsed lung or a clot in the lungs.
Can left shoulder blade pain be your heart?
It can, which is why the left is worth treating with a little more suspicion than the right. Heart pain is normally felt in the chest as well, and the NHS 999 list is built around the chest: sudden pain or discomfort in the chest that does not go away, pain spreading to the left or right arm, the neck, jaw, stomach or back, or chest pain with sweating, sickness, light-headedness or breathlessness. Isolated pain at the left blade, with nothing in the chest, that changes when you move your arm or turn your trunk and can be found with a thumb, is behaving like a musculoskeletal problem. That is a guide, not a test, and the NHS list has no exertion rule and no movement rule in it, so a pattern that fits the list is urgent whatever brought it on. A tear in the main blood vessel from the heart is the other left-sided worry: MedlinePlus describes pain felt below the breast bone that then moves under the shoulder blades or to the back, calls it sharp, stabbing, tearing or ripping, and says it usually begins suddenly.
Why does only one shoulder blade hurt?
Because almost nothing you do is symmetrical. You carry the bag on one shoulder, sleep on one side, hold the phone with one hand, reach for the mouse with one arm, and feed a baby from one side more than the other. The joints, ribs, muscles and nerve roots that supply this area are also paired and independent, so one of them being irritated gives you a one-sided pain with no mystery attached. One blade hurting is therefore not a warning sign in itself, and it is the common presentation rather than the odd one. Where one-sidedness does matter is the company it keeps: a one-sided burning patch of skin, a one-sided swollen arm, a one-sided cough or breathlessness, and pain that is always on the right under the ribs each have their own line in the warning list on this page.
How do I get rid of pain under my shoulder blade?
Movement first, position second, and strength last, over a few weeks rather than a few days. Get the upper back turning and the blade moving, which is what the stretches and the open book here are for, and break up the long static spells rather than hunting for a chair that will fix it. The NHS advice for back pain is to stay active and keep going with daily activities, and not to stay in bed for long periods, and nothing about the upper back argues for anything different. Then add the strength work for the muscles that hold the blade on the rib cage, because that is the half most people skip and the part that holds the gain. Be honest about the evidence underneath all of this: Johansson and colleagues (2017) found no studies at all of how adults recover from mid-back pain, so this is reasoned practice rather than a proven protocol, and a physio's assessment is what tells you which of it applies to you.
References
- NHS. Shoulder pain. Read 29 October 2026. https://www.nhs.uk/symptoms/shoulder-pain/
- NHS. Back pain. Read 29 October 2026. https://www.nhs.uk/conditions/back-pain/
- NHS. Dislocated shoulder. Read 29 October 2026. https://www.nhs.uk/conditions/dislocated-shoulder/
- NHS. Chest pain. Read 29 October 2026. https://www.nhs.uk/symptoms/chest-pain/
- NHS. Heart attack. Read 29 October 2026. https://www.nhs.uk/conditions/heart-attack/
- MedlinePlus. Aortic dissection. US National Library of Medicine. Read 29 October 2026. https://medlineplus.gov/ency/article/000181.htm
- NHS. Pulmonary embolism. Read 29 October 2026. https://www.nhs.uk/conditions/pulmonary-embolism/
- NHS. Pleurisy. Read 29 October 2026. https://www.nhs.uk/conditions/pleurisy/
- Asthma + Lung UK. Pneumothorax (collapsed lung). Page last reviewed 27 November 2025. Read 29 October 2026. https://www.asthmaandlung.org.uk/conditions/pneumothorax-collapsed-lung
- NHS. Heart palpitations. Read 29 October 2026. https://www.nhs.uk/symptoms/heart-palpitations/
- NHS. Heart failure. Read 29 October 2026. https://www.nhs.uk/conditions/heart-failure/
- NHS. Gallstones: symptoms. Read 29 October 2026. https://www.nhs.uk/conditions/gallstones/symptoms/
- NHS. Symptoms of lung cancer. Read 29 October 2026. https://www.nhs.uk/conditions/lung-cancer/symptoms/
- NHS. Shingles. Read 29 October 2026. https://www.nhs.uk/conditions/shingles/
- NHS. Broken or bruised ribs. Read 29 October 2026. https://www.nhs.uk/conditions/broken-or-bruised-ribs/
- NHS. Pre-eclampsia. Read 29 October 2026. https://www.nhs.uk/conditions/pre-eclampsia/
- NHS. Cervical spondylosis. Read 29 October 2026. https://www.nhs.uk/conditions/cervical-spondylosis/
- NHS. Osteoporosis. Read 29 October 2026. https://www.nhs.uk/conditions/osteoporosis/
- NHS. Ankylosing spondylitis. Read 29 October 2026. https://www.nhs.uk/conditions/ankylosing-spondylitis/
- National Institute for Health and Care Excellence. Spinal metastases and metastatic spinal cord compression (NG234). Published September 2023. https://www.nice.org.uk/guidance/ng234
- National Institute for Health and Care Excellence. Spondyloarthritis in over 16s: diagnosis and management (NG65). Published February 2017. https://www.nice.org.uk/guidance/ng65
- Darouiche RO. Spinal epidural abscess. New England Journal of Medicine. 2006;355(19):2012-2020. https://doi.org/10.1056/NEJMra055111
- Finucane LM, Downie A, Mercer C, et al. International framework for red flags for potential serious spinal pathologies. Journal of Orthopaedic and Sports Physical Therapy. 2020;50(7):350-372. https://doi.org/10.2519/jospt.2020.9971
- healthdirect. Upper back (thoracic) pain. Australian Government. Read 29 October 2026. https://www.healthdirect.gov.au/symptoms/aches-and-pains/upper-back-thoracic-pain
- Augustin G, Hadzic M, Juras J, Oreskovic S. Hypertensive disorders in pregnancy complicated by liver rupture or hematoma: a systematic review of 391 reported cases. World Journal of Emergency Surgery. 2022;17(1):40. https://doi.org/10.1186/s13017-022-00444-w
- Kulkarni R, Gibson J, Brownson P, Thomas M, Rangan A, Carr AJ, Rees JL. Subacromial shoulder pain. BESS/BOA Patient Care Pathways. Shoulder and Elbow. 2015;7(2):135-143. https://doi.org/10.1177/1758573215576456
- British Elbow and Shoulder Society, British Orthopaedic Association and Royal College of Surgeons of England. Commissioning guide: subacromial shoulder pain. 2014. Read 29 October 2026. https://boa.ac.uk/asset/CAD0336B-9051-48A7-9E4DF7072C5C7E47
- National Institute for Health and Care Excellence. Suspected cancer: recognition and referral (NG12). Published 23 June 2015, last updated 15 April 2026. https://www.nice.org.uk/guidance/ng12
- Tanaka Y, Kokubun S, Sato T, Ozawa H. Cervical roots as origin of pain in the neck or scapular regions. Spine. 2006;31(17):E568-E573. https://doi.org/10.1097/01.brs.0000229261.02816.48
- Cooper G, Bailey B, Bogduk N. Cervical zygapophysial joint pain maps. Pain Medicine. 2007;8(4):344-353. https://doi.org/10.1111/j.1526-4637.2006.00201.x
- Johansson MS, Jensen Stochkendahl M, Hartvigsen J, Boyle E, Cassidy JD. Incidence and prognosis of mid-back pain in the general population: a systematic review. European Journal of Pain. 2017;21(1):20-28. https://doi.org/10.1002/ejp.884
- Brooke-Wavell K, Skelton DA, Barker KL, et al. Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022;56(15):837-846. https://doi.org/10.1136/bjsports-2021-104634
Written and checked by the PocketPhysio editorial team. Last updated 2026-10-29.
This page is general education, not a diagnosis or a personal treatment plan. See a physiotherapist or doctor for advice about your own situation.